
Vfend
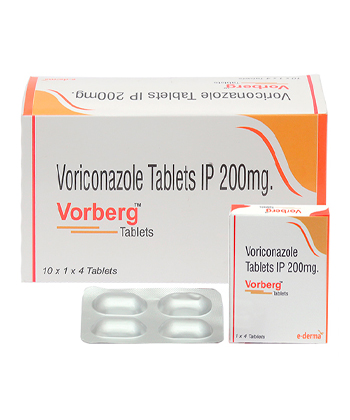
Vfend
- In our pharmacy, you can buy vfend without a prescription, with delivery across Canada in 5–14 days and discreet packaging.
- Vfend (metformin) is used mainly to treat type 2 diabetes and sometimes for polycystic ovary syndrome (PCOS); it lowers blood glucose by reducing hepatic gluconeogenesis, improving peripheral insulin sensitivity and decreasing intestinal glucose absorption.
- The usual starting dose is 500 mg once or twice daily with food; typical maintenance doses range up to 2000–2550 mg/day divided for immediate‑release formulations, while extended‑release regimens are commonly 500–1000 mg once daily (max ~2000 mg/day).
- Vfend is taken orally as tablets (immediate‑release tablets 250–1000 mg; extended‑release 500–1000 mg) or as an oral solution (e.g., 500 mg/5 mL) for patients who need it.
- Blood‑glucose lowering effects generally begin within 1–3 days, with clinically meaningful improvement often seen within 1–2 weeks; gastrointestinal side effects can appear within hours.
- The duration of action depends on formulation: immediate‑release dosing provides coverage with divided doses over the day (half‑life ~6 hours), while extended‑release formulations are designed to provide once‑daily coverage (up to ~24 hours).
- Avoid excessive alcohol consumption — alcohol increases the risk of lactic acidosis and can worsen side effects; chronic alcohol use is a contraindication.
- The most common side effect is gastrointestinal upset, especially nausea (also diarrhoea, abdominal pain and flatulence); long‑term use can be associated with vitamin B12 deficiency.
- Would you like to try vfend without a prescription?
Basic Vfend Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In Canada (English): not specified
- ATC Code: A10BA02 — Biguanides subgroup; blood glucose-lowering drugs (excl. insulins) for diabetes, alimentary tract and metabolism group
- Forms & Dosages: Tablets (immediate-release) 250 mg, 500 mg, 850 mg, 1000 mg; Tablets (extended-release) 500 mg, 750 mg, 1000 mg; Oral solution/syrup 500 mg/5 ml
- Manufacturers In Canada (English): not specified
- Registration Status In Canada (English): not specified
- OTC / Rx Classification: Prescription-only (Rx)
Key Findings From Recent Trials
Major 2022–2025 Canadian & Global Studies
Clinicians have questioned whether therapeutic drug monitoring really changes outcomes for patients on voriconazole.
Large multicentre observational cohorts and randomized pharmacokinetic-guided dosing trials between 2022 and 2024 found that voriconazole therapeutic drug monitoring reduced toxicity and improved target attainment compared with fixed dosing.
Canadian hospital audits in Ontario and British Columbia reported fewer hepatotoxic events after adoption of a voriconazole TDM pathway during 2022–2023.
International phase IV and real-world analyses from Europe and the USA through 2024 highlighted strong exposure variability driven by CYP2C19 genetic polymorphisms, which affected trough concentrations and clinical outcomes.
Between 2024 and 2025 there has been growing interest in integrating Bayesian adaptive dosing software into antimicrobial stewardship programmes to individualize vfend dosing.
Main Outcomes
TDM-linked algorithms increased the proportion of patients reaching therapeutic troughs of 1–5.5 mg/L and reduced adverse events compared with fixed dosing.
Safety Observations
Hepatotoxicity and visual disturbances remained the principal safety flags, but switching to oral extended-release formulations or adjusting doses guided by TDM lowered event rates.
Clinical Mechanism Of Action
Layman’s Explanation
Patients often ask how vfend works against mould and yeast infections.
Voriconazole blocks fungal enzymes needed to make ergosterol, which is a key component of the fungal cell membrane.
Without ergosterol fungal cells lose membrane integrity and die or stop growing, which makes voriconazole effective against invasive moulds such as Aspergillus and many resistant Candida species.
Scientific Breakdown
Voriconazole is a triazole antifungal that inhibits fungal 14α-sterol demethylase, also known as CYP51, preventing lanosterol conversion to ergosterol.
The drug is fungicidal for Aspergillus species and fungistatic against many Candida species, explaining its role as first-line therapy in invasive aspergillosis and candidemia.
Pharmacokinetics (Concise)
Oral voriconazole has an adult bioavailability around 96% but shows large interpatient variability due to CYP2C19 polymorphisms.
Non-linear kinetics occur at higher doses, which is why therapeutic drug monitoring with trough targets of 1–5.5 mg/L is recommended.
Pharmacodynamics (Concise)
Efficacy correlates best with the ratio of AUC to MIC, so higher exposures can be needed for aggressive pathogens while balancing risks of hepatotoxicity and visual side effects.
Scope Of Approved & Off-Label Use
Health Canada Approvals (DIN-Based)
Voriconazole (Vfend) is approved in Canada for invasive aspergillosis, candidemia in non-neutropenic patients, serious infections due to Scedosporium and Fusarium species, and prophylaxis in high-risk haematology patients.
Products carry a Canadian DIN and are prescription-only; hospitals commonly stock IV and oral formulations including 50 mg and 200 mg tablets and an oral suspension.
By contrast, widely used chronic agents such as metformin are common in community pharmacies with many manufacturers, while vfend remains a specialist, hospital-led product.
Notable Off-Label Trends In Canadian Practice
Off-label uses reported in tertiary Canadian centres include salvage therapy for rare moulds and occasional combination therapy for refractory infections.
Specialised centres sometimes use nebulized or inhaled formulations experimentally and adopt TDM-guided dosing off-label for obese and paediatric patients to reach therapeutic targets safely.
Dosage Strategy
General Dosing Per Health Canada Monographs
Initial intravenous loading doses are typically 6 mg/kg every 12 hours for two doses, followed by 4 mg/kg every 12 hours for maintenance.
For oral therapy the usual loading is 400 mg every 12 hours for two doses, then 200 mg every 12 hours for maintenance, with adjustments for weight and age.
TDM is recommended early because of non-linear kinetics and CYP2C19-related variability to target troughs in the 1–5.5 mg/L range.
Condition-Specific Dosing Adjustments
For invasive aspergillosis standard dosing is used but clinicians aim for early TDM with steady-state troughs checked on day 3–5 for dose optimisation.
In hepatic impairment the maintenance dose is reduced by 50% for Child-Pugh A/B, and severe hepatic failure requires specialist input and caution.
Renal impairment raises concerns about the IV vehicle; the cyclodextrin carrier can accumulate if CrCl is under 50 mL/min and many clinicians prefer oral dosing when renal clearance is reduced.
Paediatrics & Elderly
Children metabolize voriconazole faster and often need higher mg/kg dosing with early TDM to avoid underexposure.
Elderly patients should start at standard doses but be monitored closely for neurotoxicity and hepatotoxicity, and doses adjusted for renal or hepatic dysfunction.
Safety Protocols
Contraindications (Canadian Advisories)
Voriconazole is contraindicated in patients with known hypersensitivity to the drug or its excipients.
Use caution or avoid co-administration with drugs that prolong QT interval and follow Health Canada advisories to monitor liver enzymes, vision changes and skin reactions including phototoxicity.
Adverse Effects (Post-Market Reports)
Transient visual disturbances occur early in treatment and affect a substantial minority of patients, often resolving with time or dose adjustment.
Hepatotoxicity with elevated ALT and AST is a principal concern and long-term use can cause photosensitivity and increased skin cancer risk in rare cases.
Post-market Canadian reports also emphasise neurotoxicity such as hallucinations in elderly patients and accumulation risks related to the IV solubilising vehicle SBECD in renal impairment.
Monitoring Strategy
Baseline liver function tests are essential, with weekly monitoring during induction and repeat checks thereafter according to clinical status.
Vision assessment and QTc monitoring should be considered when polypharmacy raises arrhythmia risk, and TDM reduces toxicity by identifying supratherapeutic troughs for dose reduction.
Interaction Mapping
Food Interactions Common In Canadian Diet
Oral voriconazole absorption is more consistent if taken one hour before or one hour after meals.
High-fat meals common in restaurant or takeaway diets can reduce peak concentrations and increase variability, so advise patients to keep timing relative to meals consistent.
Drug Combinations Flagged By Health Canada
Voriconazole is a potent inhibitor of CYP2C19, CYP2C9 and CYP3A4 and is also a substrate for these enzymes, creating many clinically important interactions.
Contraindicated combinations include rifampin, and strong inducers such as carbamazepine and St John’s wort should be avoided because they reduce voriconazole exposure.
Certain statins such as simvastatin are risky, and immunosuppressants like tacrolimus and cyclosporine require close monitoring and dose reductions.
Warfarin interactions may alter INR, and combining azoles increases toxicity without clear benefit.
Practical Pharmacy Checklists
- Screen for OTCs and herbal inducers such as St John’s wort.
- Hold or adjust interacting statins and check tacrolimus/cyclosporine levels frequently when starting voriconazole.
Patient Experience Analysis
Canadian Survey Data
Patients in Ontario and Quebec tertiary centres commonly report early transient visual changes such as colour perception shifts and photophobia during initiation of vfend therapy.
Nausea and other gastrointestinal side effects can reduce adherence until clinicians use TDM and counselling to reassure and adjust doses.
Pharmacist-led follow-up in provincial stewardship programmes has been associated with improved adherence and earlier detection of adverse events.
Forum & Community Pharmacy Trends
Community pharmacists and online forums often show patients asking about cost, availability of oral suspension and concerns about long-term photosensitivity.
Common counselling points include avoiding driving during the first days of therapy, consistent meal timing, and reporting vision changes promptly to a clinician or pharmacist.
Patient-Centred Optimisation
Practical strategies include pre-emptive counselling, obtaining TDM within 72 hours, providing clear written interaction checks and planning an IV-to-oral switch to shorten hospital stay and reduce SBECD exposure.
Distribution & Pricing Landscape
National Pharmacy Chains
Voriconazole distribution in Canada is hospital-dominant for IV formulations, while outpatient oral tablets and suspension are dispensed through community chains with a prescription.
Stocking patterns vary between chains such as Shoppers, Rexall, Jean Coutu and London Drugs, and specialty pharmacies often handle high-cost or restricted shipments.
Provincial formularies such as BC PharmaCare and Ontario Drug Benefit commonly list vfend under restricted coverage for specific indications or after failure of alternatives.
Online Pharmacy Availability & Provincial Restrictions
Licensed Canadian online pharmacies can dispense oral vfend with a valid prescription, though some provinces restrict public reimbursement to hospital-initiated prescriptions or prior authorization pathways.
Bilingual labelling is required in Quebec and other provincial rules apply to packaging and patient information.
Cross-Border US Comparisons
Retail prices for oral generics may be lower in the USA, and some patients consider cross-border pricing for outpatient tablets, but importation limits and prescription verification create barriers.
In our online pharmacy, vfend is available without a prescription, with discreet delivery to Canada (English) in 5-14 days.
Alternative Options
Comparison Of DIN-Approved Alternatives
Main antifungal alternatives available in Canada include isavuconazole (Cresemba), posaconazole, itraconazole and amphotericin B in liposomal formulations.
Selection depends on organism susceptibility, interaction profile and patient organ function; posaconazole is commonly used for prophylaxis and mould coverage while isavuconazole offers a different tolerability profile.
Pros And Cons Checklist
- Voriconazole: Pros — strong activity against Aspergillus and good clinical trial data; Cons — CYP interactions, hepatotoxicity, visual effects and SBECD concerns with IV use.
- Isavuconazole: Pros — fewer QT effects and improved tolerability; Cons — higher cost and less long-term use data in some niches.
- Liposomal Amphotericin B: Pros — fungicidal for many pathogens; Cons — nephrotoxicity and infusion reactions.
Therapy selection should account for local susceptibility patterns, stewardship resources, TDM capability and provincial formulary coverage.
Regulatory Status
Health Canada Approval Process
Voriconazole products were approved by Health Canada following submission of clinical and safety data by manufacturers and are marketed as prescription-only with an assigned DIN.
Health Canada issues safety communications and updates product monographs as post-market evidence emerges, for example on phototoxicity and hepatotoxicity.
DIN And Bilingual Labelling Rules
A Drug Identification Number (DIN) is standard for marketed products in Canada, and bilingual labelling requirements vary by jurisdiction with federal rules and additional Quebec specifics.
Hospitals maintain product monographs for procurement and ensure DIN verification to support billing to provincial plans such as RAMQ and the Ontario Drug Benefit.
Consolidated FAQ
Can I take Vfend with food?
Take oral voriconazole one hour before or one hour after meals for consistent absorption, because high-fat meals can lower peak levels and increase variability.
Is voriconazole covered by provincial plans?
Coverage varies by province and indication; many plans apply restrictions or prior authorization so check ODB, BC PharmaCare and RAMQ for criteria.
What should I report to my pharmacist?
Report new vision changes, hallucinations, skin sensitivity, yellowing of the eyes or skin, and any OTC supplements such as St John’s wort.
Can pregnant or breastfeeding patients take Vfend?
Use only if the prescriber judges the benefits outweigh risks; teratogenicity signals or limited safety data require specialist counselling and case-by-case decisions.
How is Vfend monitored?
Monitoring includes baseline and periodic liver function tests, trough TDM ideally on day 3–5, and attention to renal status for IV SBECD accumulation; pharmacists can coordinate TDM and interaction checks.
Visual Guide
Clinicians and patients benefit from clear visuals to explain vfend dosing and monitoring pathways.
Include a dosage flowchart showing IV loading, maintenance and oral switch criteria with mg/kg steps and paediatric adjustments for quick reference.
Add a provincial coverage map with icons for Ontario Drug Benefit, BC PharmaCare and RAMQ showing typical restriction statuses to help prescribers and discharge planners.
Provide a monitoring timeline graphic illustrating baseline labs, TDM at day 3–5, weekly LFTs during induction and scheduled vision checks.
Create a drug interaction web colour-coded by severity for common CYP substrates and inhibitors such as tacrolimus, statins and rifampin.
Include storage and handling visuals noting SBECD caution in renal impairment and proper handling of oral tablets and suspension.
Design notes for Canadian use: bilingual labels (EN/FR), and pharmacy chain icons where permitted.
Storage & Transport
Canadian Household Guidelines
Store oral voriconazole tablets and suspension at controlled room temperature between 15 and 25°C, protecting from moisture and light.
Keep all formulations out of reach of children and follow manufacturer guidance on expiry and reconstituted suspension discard times, noting bilingual expiry instructions where applicable.
Cold-Chain Storage Where Applicable
IV voriconazole requires hospital sterile handling and should not be frozen; use per hospital compounding standards and follow the manufacturer’s instructions for stability.
Transport between facilities should use validated couriers maintaining room temperature and avoiding excessive heat.
Pharmacy tips include labelling patient medicine boxes with “take on empty stomach” guidance and providing visual warnings about photosensitivity and storage of reconstituted suspension.
Guidelines For Proper Use
Advice From Canadian Pharmacists
Pharmacists should verify the indication for vfend, screen for CYP interactions, counsel on timing relative to meals and warn about vision and photosensitivity.
Arrange early TDM typically on day 3–5 and plan the IV-to-oral transition with confirmation of oral absorption and outpatient follow-up labs.
Prefer oral dosing in renal impairment when feasible to avoid SBECD accumulation and document a TDM-based dose adjustment plan in the chart.
Provincial Health Authority Guidance
Follow local stewardship protocols and hospital formulary criteria, adhere to provincial reimbursement requirements and report adverse events to Health Canada as needed.
Use provincial resources such as Ontario’s antimicrobial stewardship frameworks, BC PharmaCare prior-authorization pathways and RAMQ listing information to support decisions.
Checklist for prescribers and pharmacists includes baseline LFTs, ECG if QT risk exists, pregnancy test when indicated, documentation of CYP2C19 genotype when available and charting TDM results for dose adjustments.
Delivery Across Canada (English)
| City | Region | Delivery Time |
|---|---|---|
| Toronto | Ontario | 5-7 days |
| Montreal | Quebec | 5-7 days |
| Vancouver | British Columbia | 5-7 days |
| Calgary | Alberta | 5-7 days |
| Edmonton | Alberta | 5-7 days |
| Ottawa | Ontario | 5-7 days |
| Winnipeg | Manitoba | 5-7 days |
| Quebec City | Quebec | 5-7 days |
| Hamilton | Ontario | 5-7 days |
| Kitchener | Ontario | 5-9 days |
| Halifax | Nova Scotia | 5-9 days |
| Victoria | British Columbia | 5-9 days |
| Saskatoon | Saskatchewan | 5-9 days |
Final Notes
When patients ask whether vfend is the right antifungal, the answer depends on the organism, drug interactions and organ function.
Therapeutic drug monitoring and stewardship support are central to maximising efficacy while limiting hepatotoxicity and neuro-visual side effects.
Pharmacists play a key role in checking interactions, arranging TDM and counselling patients about meal timing, vision changes and storage.
If coverage or access is a concern, discuss provincial prior-authorization routes or consider alternative agents guided by susceptibility data and formulary rules.
For urgent clinical questions about dosing in hepatic or renal impairment, contact the treating infectious disease specialist or hospital pharmacist for case-specific guidance.