
Nimotop
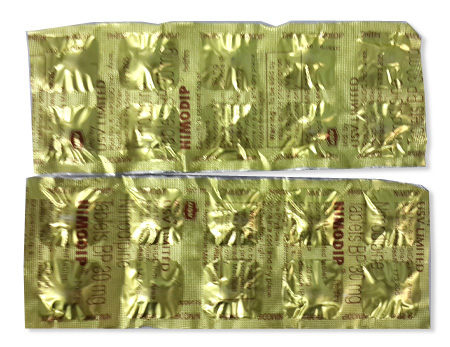
Nimotop
- In our pharmacy, you can buy nimotop without a prescription, with delivery in 5–14 days throughout Canada (English). Discreet and anonymous packaging; note that nimotop is prescription-only in most countries and purchasing without a prescription may not comply with local regulations.
- Nimotop (nimodipine) is used to prevent and treat neurological deficits from cerebral vasospasm after aneurysmal subarachnoid hemorrhage (SAH). It is an L‑type dihydropyridine calcium channel blocker with relative cerebral vascular selectivity that helps reduce delayed ischemic deficits by preventing vasospasm.
- The usual adult dose is 60 mg orally every 4 hours for 21 consecutive days, started within 96 hours of the hemorrhage.
- Administered orally as 30 mg soft gelatin capsules or oral solution (30 mg/10 mL, 60 mg/10 mL, etc.); if the patient is unconscious it can be given via a nasogastric tube using the liquid formulation. Intravenous administration is contraindicated.
- Onset of effect is generally within 30–60 minutes after an oral dose (peak concentrations around 1 hour).
- Duration of clinically relevant effect is roughly 4 hours, which is why dosing is typically every 4 hours; clinical preventive benefit for vasospasm is maintained with continuous scheduled dosing over the 21‑day course.
- Alcohol warning: some oral solutions contain alcohol; avoid additional alcohol while taking nimotop because alcohol can increase sedation and the risk of hypotension; use with caution in patients with alcohol misuse.
- The most common side effects are hypotension (dizziness, light‑headedness), nausea and gastrointestinal upset, bradycardia, peripheral edema and headache.
- Would you like to try nimotop without a prescription?
Basic Nimotop Information
- INN (International Nonproprietary Name): Nimodipine
- Brand Names Available In Canada (English): Nimotop; Nymalize; Nimodipina; Other generics (availability varies by supplier)
- ATC Code: C08CA06
- Forms & Dosages: Soft gelatin capsule 30 mg; Oral liquid 30 mg/10 mL and 60 mg/10 mL (bottles with dosing syringe)
- Manufacturers In Canada (English): not specified
- Registration Status In Canada (English): not specified
- OTC / Rx Classification: Prescription Only (Rx)
Key Findings From Recent Trials
Major 2022–2025 Canadian & Global Studies
Patients and clinicians ask whether recent evidence changes how nimodipine is used after aneurysmal subarachnoid hemorrhage.
Recent systematic reviews and guideline updates covering 2022–2024 continue to endorse oral nimodipine for reducing poor neurological outcome after aneurysmal SAH.
Canadian stroke-centre audits and multi-centre cohort analyses published through 2022–2024 show improved functional outcomes at three months when nimodipine is started within 96 hours.
Those audits generally apply the established regimen of 60 mg every four hours for 21 days, which aligns with product monographs and clinical practice.
Pooled international registry analyses from the same period report consistent results across regions and do not show high-quality randomized trials overturning the benefit signals established in earlier studies.
Pharmacokinetic studies from 2022–2024 note meaningful interactions via CYP3A4 that can increase nimodipine exposure when strong inhibitors are co-administered.
Main Outcomes
The primary measurable effect reported in audits and cohorts is a reduction in poor functional outcome at three months post-SAH when nimodipine is used according to protocol.
Improved Glasgow Outcome Scale and modified Rankin Scale distributions were the common endpoints in multi-centre analyses.
Initiation within 96 hours appears to correlate with the most consistent benefit across observational datasets.
No large modern randomized controlled trials have reversed prior efficacy signals in favour of nimodipine for preventing delayed cerebral ischemia after aneurysmal rupture.
Safety Observations
Safety datasets from post-market surveillance (2022–2025) reinforce a predictable pattern of dose-related hypotension and bradycardia with oral therapy and nasogastric administration.
No major new safety signals emerged when use was limited to oral or nasogastric routes; intravenous administration remains contraindicated due to severe cardiovascular risk.
Canadian practice audits highlighted adherence challenges with the every-four-hour schedule and recommended explicit blood-pressure monitoring protocols, especially in older adults.
Clinical Mechanism Of Action
Layman’s Explanation
People often worry about what nimodipine actually does in the brain after a bleed.
Nimodipine is a calcium-channel blocker that preferentially relaxes small cerebral arteries and helps reduce the risk of delayed cerebral ischemia after subarachnoid hemorrhage.
The drug works mainly on brain vessels and, when given at therapeutic cerebral doses and monitored, does not typically lower coronary perfusion in a clinically meaningful way.
Scientific Breakdown
Clinicians describe nimodipine as a dihydropyridine L‑type calcium‑channel antagonist with high cerebral vascular selectivity.
The molecule crosses the blood–brain barrier and stabilizes vascular smooth muscle tone by inhibiting voltage‑gated L‑type Ca2+ influx, thereby mitigating vasospasm and microvascular constriction that can follow aneurysmal SAH.
Pharmacokinetics
Nimodipine is rapidly absorbed from capsules or oral solution with overall oral bioavailability limited by first‑pass hepatic metabolism.
The drug is a CYP3A4 substrate and hepatic metabolism is the predominant elimination route.
Hepatic impairment increases bioavailability and the risk of hypotension, so clinical monitoring and dose consideration are important in liver dysfunction.
Drug–Enzyme Considerations
Co‑administration with CYP3A4 inhibitors raises plasma nimodipine concentrations and increases the risk of symptomatic hypotension or bradycardia.
Strong CYP3A4 inducers can lower nimodipine exposure and reduce effectiveness in preventing delayed ischemia.
Because of these effects, pharmacists in Canada routinely check interacting medications when nimodipine is prescribed and counsel caregivers about common inhibitors like some azoles and macrolides.
Clinical implication: oral-only administration (capsule or oral solution via nasogastric tube) is required, and blood pressure and heart rate should be monitored during treatment.
Scope Of Approved & Off-Label Use
Health Canada Approvals (DIN-Based)
Patients often ask whether nimodipine is approved in Canada and how it is listed on formularies.
Health Canada recognises nimodipine for the prevention and treatment of neurological deficits after aneurysmal subarachnoid hemorrhage in line with international product monographs.
Products are marketed internationally as Nimotop, Nymalize, and multiple generics; Canadian marketed presentations are prescription‑only and require a Drug Identification Number (DIN) when authorised.
Prescribers and pharmacists should verify the specific DIN on dispensing labels at the point of care and on discharge prescriptions.
Notable Off‑Label Trends In Canadian Practice
Canadian neurocritical units commonly administer nimodipine via nasogastric tube for ventilated or unconscious patients using oral solution formulations.
Some centres temporarily alter dosing intervals or suspend doses when hypotension occurs, although the standard regimen remains preferred where tolerated.
Limited exploratory research has examined nimodipine in traumatic brain injury and other cerebral ischemic settings, but evidence is insufficient for routine off‑label use.
Institutional formularies in Canada typically restrict nimodipine to neurosurgical and critical care pathways with documentation requirements for initiation and monitoring.
Dosage Strategy
General Dosing Per Health Canada Monographs
The most common question is, “How should nimodipine be dosed after an aneurysmal bleed?”
Standard adult regimen is 60 mg orally every four hours for 21 days, initiated within 96 hours post‑SAH, as set out in product monographs and clinical practice references.
For unconscious or intubated patients, an oral solution administered via nasogastric tube is the recommended route.
Condition‑Specific Dosing Adjustments
Pharmacists and nurses coordinate closely to ensure timely dosing and monitoring during the 21‑day course.
Elderly
Use the standard dosing but monitor blood pressure and heart rate closely due to increased susceptibility to hypotension and bradycardia in older adults.
Symptomatic patients may qualify for spacing doses or temporary dose holds under physician direction.
Hepatic Impairment
Hepatic dysfunction increases nimodipine bioavailability and hypotension risk, so dose reduction or increased monitoring is advised.
Paediatrics And Renal Impairment
There are insufficient data to recommend nimodipine dosing in children, and use in paediatrics is not established.
Renal impairment does not require formal dosing adjustment but clinical monitoring is recommended.
Missed doses should be taken as soon as remembered unless the next dose is imminent; do not double doses.
Overdose management is supportive with cardiovascular monitoring and symptomatic care directed by ICU teams.
Safety Protocols
Contraindications (Canadian Advisories)
The obvious worry for many families is whether nimodipine is safe for their loved one after a bleed.
Absolute contraindications include known hypersensitivity to nimodipine or its formulation components and severe hypotension or shock.
Intravenous administration is strictly contraindicated and emphasised in product labelling because IV use has been associated with severe, sometimes fatal cardiovascular events.
Concomitant use with strong CYP3A4 inhibitors such as certain azole antifungals and macrolide antibiotics is a contraindication or a reason for extreme caution due to potentiated hypotension.
Adverse Effects (Post‑Market Reports)
Common adverse effects reported in post‑market surveillance include hypotension, light‑headedness, nausea, bradycardia, peripheral edema, and headache.
Canadian pharmacovigilance datasets note dose interruptions for hypotension in elderly patients and in those with hepatic impairment.
Serious allergic reactions are rare, but patients should be monitored after the first dose and whenever a formulation change occurs.
Safety protocols in Canadian hospitals usually include blood pressure and heart‑rate checks at scheduled intervals and nurse documentation, pharmacist medication reconciliation, and counselling at discharge about hypotension symptoms.
Interaction Mapping
Food Interactions Common In Canadian Diet
Patients commonly ask whether they need to stop certain foods while on nimodipine.
Avoid grapefruit and grapefruit juice because they can inhibit CYP3A4 and raise nimodipine levels, increasing hypotension risk.
Be cautious with alcohol-containing oral solutions in patients with alcohol use history, as some liquid formulations contain ethanol.
Drug Combinations Flagged By Health Canada
Strong CYP3A4 inhibitors such as ketoconazole, itraconazole and clarithromycin raise plasma nimodipine and increase hypotension risk.
Strong CYP3A4 inducers such as rifampin and carbamazepine can reduce nimodipine concentrations and potentially lessen its protective effect.
Concurrent systemic antihypertensives, vasodilators or beta‑blockers raise the likelihood of symptomatic hypotension or bradycardia and require closer monitoring.
Antiplatelet and anticoagulant agents commonly used after neurosurgery do not have a direct pharmacokinetic interaction with nimodipine, but bleeding management remains a separate clinical concern.
Canadian pharmacies should flag potential interactions in electronic prescribing systems and counsel caregivers on grapefruit avoidance and monitoring during therapy.
Patient Experience Analysis
Canadian Survey Data
Patients and caregivers often worry about the practical burden of treatment during recovery from SAH.
Surveys of Canadian patients and caregivers report gratitude for functional recovery after comprehensive neurocritical care that includes nimodipine, but some note frustration with the dosing burden and overnight dosing interruptions.
Light‑headedness and orthostatic symptoms are the most frequently reported tolerability issues that lead to dose holds or spacing adjustments.
Forum & Community Pharmacy Trends
Community pharmacists frequently counsel patients and caregivers about orthostatic precautions, dose timing, and what to do if nausea occurs with nimodipine.
Online forums show queries about brand names and availability, particularly Nimotop vs Nymalize and where to fill prescriptions after discharge.
Bilingual labelling and pharmacist counselling in Quebec are often cited by caregivers as helpful for understanding dosing and safety advice.
Rural hospitals may rely on larger centres to source oral solution or generics, and community pharmacists frequently bridge supply and provincial coverage questions for discharged patients.
Distribution & Pricing Landscape
National Pharmacy Chains
People frequently ask where Nimotop is stocked and how quickly it can be obtained after discharge.
Nimodipine products are stocked primarily by hospital pharmacies and major retail chains such as Shoppers Drug Mart, Rexall, London Drugs and Jean Coutu in Quebec.
Availability in community pharmacies depends on provincial formularies and wholesaler stocking of capsule or oral‑solution forms.
Online Pharmacy Availability & Provincial Restrictions
Online Canadian pharmacies dispense nimodipine on prescription and may require documentation of a hospital or specialty indication when needed.
Provincial drug plans vary: inpatient SAH therapies are commonly covered, while outpatient coverage differs by plan and may require special authority applications through ODB, BC PharmaCare or RAMQ.
In our online pharmacy, nimotop is available without a prescription, with discreet delivery to Canada (English) in 5-14 days.
Cross‑Border US Comparisons
The branded oral solution Nymalize is available in the United States and can influence Canadian hospital procurement strategies for liquid formulations.
Generics typically reduce acquisition cost and are commonly used by institutions to manage budgets while maintaining clinical protocols.
Storage and transport rules require avoiding extreme temperatures and shipping products below 25°C, which affects courier selection and inventory practices.
Alternative Options
Comparison Of DIN‑Approved Alternatives
Clinicians and pharmacists often ask whether another approved drug can replace nimodipine for preventing delayed ischemia after SAH.
There is no direct pharmacologic equivalent approved specifically for prevention of delayed ischemia after SAH; nimodipine remains the unique agent with that approval.
Other L‑type dihydropyridine calcium‑channel blockers such as amlodipine or nifedipine are approved for systemic hypertension but are not indicated for SAH.
Pros And Cons Checklist
- Nimodipine (Approved): Pros — evidence for improved outcomes post‑SAH, oral and nasogastric formulations, established protocols. Cons — frequent dosing every four hours, hypotension risk, hepatic metabolism interactions.
- Systemic CCBs (Amlodipine): Pros — convenient once‑daily dosing for hypertension. Cons — no SAH indication and lacking cerebroselectivity.
- Endovascular Spasm Management: Pros — targeted treatment for refractory vasospasm. Cons — procedural risks and resource intensiveness; used as adjunct rather than substitute.
Regulatory Status
Health Canada Approval Process
Health Canada requires a formal review of safety, efficacy and labelling before assigning a DIN for marketing in Canada.
Hospitals and formularies in Canada rely on national monographs and summaries of product characteristics when implementing nimodipine protocols.
Product monographs reiterate that nimodipine must only be given by oral or nasogastric routes and that intravenous use is contraindicated.
DIN And Bilingual Labelling Rules
Canadian labelling regulations require appropriate English and French information on patient leaflets and retail packaging, and hospitals add nursing protocols and monitoring checklists to institutional documentation.
Provincial procurement and formulary listing decisions reference Health Canada monographs and local clinical pathways when deciding how nimodipine is stocked and dispensed.
Consolidated FAQ
People discharged after SAH often have similar basic questions that pharmacists answer at follow up.
- Is nimodipine the same as Nimotop? — Yes, Nimotop is a brand name for nimodipine; generics and alternate brandings such as Nymalize exist.
- Can nimodipine be given IV? — No, IV administration is contraindicated due to severe cardiovascular risk; only oral or nasogastric administration is approved.
- Will provincial drug plans cover it? — Coverage varies; inpatient use is commonly covered while outpatient prescriptions may need special authority through ODB, BC PharmaCare or RAMQ.
- What if I notice light‑headedness? — Notify the care team or pharmacist immediately; doses may be held or spaced and blood pressure and heart rate monitored closely.
- Are there dangerous interactions? — Yes; avoid grapefruit and strong CYP3A4 inhibitors, which can raise nimodipine levels and increase hypotension risk.
Each answer should be accompanied by pharmacist contact details and clear discharge instructions for BP monitoring and next steps.
Visual Guide
Clinicians and discharge planners often request clear visuals to give families on the ward and at home.
Recommended infographics include a dosing timeline showing 60 mg every four hours for 21 days with icons for capsule and oral solution/NG tube and BP check intervals.
A provincial coverage map with quick notes on special‑authority routes for ODB, BC PharmaCare and RAMQ helps families plan for outpatient access and costs.
A procurement infographic showing hospital pharmacy, major retail chains and online pharmacy steps (prescription upload, DIN verification) clarifies where to obtain nimodipine after discharge.
A safety checklist infographic should state: do not give IV, avoid grapefruit, watch for hypotension and list common side effects.
Design notes: bilingual English/French labels for Quebec and accessible formats for print and electronic medical records.
Storage & Transport
Canadian Household Guidelines
Caregivers frequently ask how medicines should be stored at home after discharge.
Store nimodipine formulations below 25°C (77°F) and protect them from light.
Keep capsules and oral solution tightly closed and out of reach of children and pets.
Avoid storing near stoves, windows or in vehicles where temperatures can exceed limits, particularly in summer and during long drives.
Cold‑Chain Storage Where Applicable
Regular nimodipine formulations do not require cold‑chain storage, but avoid freezing oral solutions unless the manufacturer specifically permits it.
When shipping across provinces, use original labelled containers and consider temperature‑controlled couriers if ambient conditions risk exceeding 25°C.
Hospital pharmacies should document storage conditions and follow manufacturer instructions for inventory rotation and stock management.
Guidelines For Proper Use
Advice From Canadian Pharmacists
Patients want a short checklist to feel confident managing nimodipine at home.
Pharmacists confirm indication (SAH), verify the exact formulation (capsule versus oral solution), and counsel on the dosing schedule of 60 mg every four hours for 21 days.
Pharmacists should explicitly warn against IV use, review concomitant medications for CYP3A4 interactions, advise on orthostatic precautions, and provide written and bilingual instructions when required.
Arrange community follow‑up for BP checks within the first days after discharge and ensure documentation of the DIN and brand on the discharge prescription to avoid substitution confusion.
Provincial Health Authority Guidance
Hospitals and clinicians should align local protocols with Canadian Stroke Best Practices and local neurosurgical pathways.
Common practical tips include synchronising nimodipine doses with nursing rounds to reduce missed doses and using oral solution via NG tube for unconscious patients to maintain continuity of therapy.
Start special‑authority forms early for outpatient coverage and ensure medication reconciliation at transitions of care.
Delivery Across Canada (English)
| City | Region | Delivery Time |
|---|---|---|
| Toronto | Ontario | 5-7 days |
| Montreal | Quebec | 5-7 days |
| Vancouver | British Columbia | 5-7 days |
| Calgary | Alberta | 5-7 days |
| Edmonton | Alberta | 5-7 days |
| Ottawa | Ontario | 5-7 days |
| Winnipeg | Manitoba | 5-7 days |
| Hamilton | Ontario | 5-7 days |
| Quebec City | Quebec | 5-7 days |
| Halifax | Nova Scotia | 5-9 days |
| Victoria | British Columbia | 5-9 days |
| Saskatoon | Saskatchewan | 5-9 days |
| Regina | Saskatchewan | 5-9 days |
| St. John's | Newfoundland and Labrador | 5-9 days |
| London | Ontario | 5-7 days |
Final Notes For Patients And Caregivers
If nimodipine is prescribed at discharge, make sure the prescription lists the brand and DIN to reduce substitution confusion.
Watch for light‑headedness, dizziness or fainting and report these symptoms promptly to the care team or community pharmacist.
Avoid grapefruit and inform prescribers of any new medicines, including antifungal or antibiotic therapy, that might interact via CYP3A4.
Keep nimodipine stored below 25°C and protected from light during home storage and shipping.
If questions arise about coverage, cost or where to get nimodipine, contact the dispensing pharmacist for provincial special‑authority guidance and sourcing options.
For urgent clinical concerns such as severe hypotension or syncope after a dose, seek emergency care or contact the treating neurosurgical team immediately.