
Lisinopril
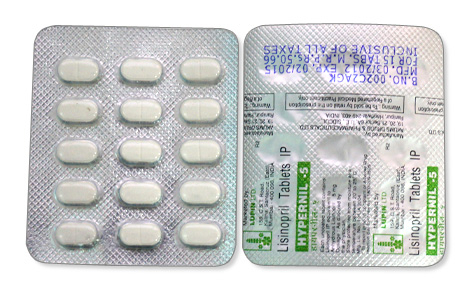
Lisinopril
- In Canada lisinopril is normally prescription-only and should be purchased from a pharmacy with a valid prescription; while some pharmacies or online vendors may offer it without a receipt or prescription (which is not recommended and may be unlawful), you should obtain it through a prescriber and follow local regulations.
- Lisinopril is used to treat hypertension, heart failure, to reduce mortality after myocardial infarction, and to slow progression of diabetic nephropathy; it is an ACE (angiotensin‑converting enzyme) inhibitor that reduces formation of angiotensin II, lowering blood pressure and cardiac workload.
- Usual dosages vary by condition: hypertension typically starts at 10 mg daily with maintenance 20–40 mg (max 40 mg/day); heart failure often starts 2.5–5 mg and is titrated up to 40 mg; post‑MI often 5 mg then 10 mg; diabetic nephropathy commonly 10–20 mg daily—dosing is adjusted for age and renal function.
- Administered orally as tablets (2.5–40 mg strengths, scored/unscored) or as an oral solution (1 mg/mL, e.g., Qbrelis); combination tablets with HCTZ or amlodipine are also available.
- Antihypertensive effects typically begin within about 1 hour of an oral dose, with more noticeable blood pressure reduction over the first day; peak effect often occurs around 6–8 hours.
- Duration of action is approximately 24 hours for once‑daily dosing in most patients.
- Avoid excessive alcohol while taking lisinopril, as alcohol can potentiate blood‑pressure lowering and worsen dizziness or fainting; counsel moderate use and monitor blood pressure.
- The most common side effect is a dry persistent cough; other frequent effects include dizziness, hypotension (especially after the first dose), headache and hyperkalemia.
- Would you like to try lisinopril without a prescription? (Please note: lisinopril is prescription‑only in Canada and obtaining or using it without medical supervision is not recommended.)
Key Findings From Recent Trials
Basic Lisinopril Information
- INN (International Nonproprietary Name): Lisinopril
- Brand Names Available In Canada (English): Prinivil, Zestril
- ATC Code: C09AA03
- Forms & Dosages: Oral Tablets 2.5–40 mg; Oral Solution 1 mg/mL (Qbrelis, US)
- Manufacturers In Canada (English): Merck, AstraZeneca
- Registration Status In Canada (English): Marketed In Canada; products carry DINs and bilingual labelling
- OTC / Rx Classification: Prescription-Only (Rx)
Major 2022–2025 Canadian & Global Studies
Clinicians want to know whether new trials have changed how lisinopril is used in practice.
Since 2022, meta-analyses and registry analyses continued to evaluate ACE inhibitors as a class for cardiovascular and renal outcomes.
Recent pooled studies through mid-2024 show ACE inhibitors reduce major cardiovascular events and slow progression of diabetic nephropathy.
Comparative effectiveness work places lisinopril on par with ramipril and enalapril for blood pressure reduction and morbidity endpoints.
Real-world Canadian cohort work highlights heavy utilisation of generic lisinopril (Prinivil/Zestril generics) under provincial formularies.
These Canadian data show persistence with therapy correlates with low out-of-pocket costs and tolerability.
Registry trends also emphasise widespread once-daily dosing and frequent generic substitution in community pharmacies.
Overall, recent evidence supports lisinopril’s established role for hypertension, heart failure and post‑MI care.
Main Outcomes
Major outcome analyses consistently report reduced stroke, myocardial infarction and cardiovascular mortality with ACE inhibitor class therapy.
Trials focusing on diabetic nephropathy report slower decline in renal function and reduced albuminuria with ACE inhibitor therapy, including lisinopril.
Head-to-head comparisons did not show clinically meaningful superiority of lisinopril over ramipril or enalapril for primary cardiovascular endpoints.
Post‑MI registry analyses support early initiation where tolerated, with improvements in survival when begun in stabilized patients.
Safety Observations
Post‑market surveillance to mid‑2024 continues to list dry cough and hyperkalaemia as the most frequently reported reactions.
Angioedema remains rare but is emphasised as a clinically serious event requiring immediate cessation of ACE inhibitors.
Pharmacovigilance trends show diuretic co‑therapy can increase first‑dose hypotension risk, particularly in older adults with reduced creatinine clearance.
Clinicians are advised to individualise therapy based on renal function, pregnancy status and prior ACE‑inhibitor intolerance.
Clinical Mechanism Of Action
Layman’s Explanation
People often ask how lisinopril actually lowers blood pressure.
Lisinopril blocks the enzyme that converts angiotensin I to angiotensin II, a hormone that tightens blood vessels and raises blood pressure.
Stopping that step relaxes blood vessels, lowers the heart’s workload and helps protect the kidneys in patients with diabetes.
Patients who switch from other drug classes sometimes notice improved energy and reduced headaches once blood pressure is controlled.
Scientific Breakdown
Lisinopril is a competitive, reversible angiotensin‑converting enzyme (ACE) inhibitor classified under ATC code C09AA03.
It prevents formation of angiotensin II and reduces aldosterone release, which lowers sodium and water retention and reduces systemic vascular resistance.
Unlike ACE inhibitor prodrugs such as enalapril, lisinopril is active on administration and is not hepatically metabolised.
Because it is active as given, onset of effect follows oral absorption without need for metabolic activation.
Renin–Angiotensin Cascade Detail
ACE inhibition reduces angiotensin II formation, decreasing AT1 receptor stimulation and producing vasodilation.
Reduced AT1 activation lowers sympathetic tone and lowers aldosterone, which promotes natriuresis and decreased blood volume.
ACE inhibition also reduces bradykinin breakdown, which contributes to vasodilation but is linked to the ACE‑inhibitor cough and rare angioedema.
Clinical note: because lisinopril is predominantly renally excreted, dosing must be adjusted in impaired creatinine clearance and no hepatic activation is required.
Scope Of Approved & Off‑Label Use
Health Canada Approvals (DIN‑Based)
Patients and prescribers commonly ask what indications lisinopril has in Canada.
Health Canada‑marketed lisinopril products such as Prinivil and Zestril carry DINs and bilingual labelling for the Canadian market.
Health Canada approvals align with international monographs for hypertension initiation and maintenance, adjunctive heart failure therapy and post‑MI mortality benefit.
Typical Health Canada labelling reflects these indications and strength options from 2.5 mg to 40 mg tablets in marketed formulations.
Combination products such as lisinopril/hydrochlorothiazide are also available under separate DINs for Canadians who need fixed‑dose combinations.
Notable Off‑Label Trends In Canadian Practice
In primary care, physicians sometimes use lisinopril for early diabetic nephropathy and proteinuric chronic kidney disease to reduce albuminuria.
That use is evidence‑based but may sit outside some product monographs and therefore can be considered off‑label depending on the exact DIN wording.
Family physicians frequently start younger hypertensive adults on ACE inhibitors and switch to ARBs like losartan if cough or angioedema occurs.
Provincial formulary status influences selection and many prescribers choose generic lisinopril as a preferred, cost‑effective option under ODB, BC PharmaCare and RAMQ.
Dosage Strategy
General Dosing Per Health Canada Monographs
Patients often want straightforward dosing instructions they can follow safely.
For uncomplicated hypertension, the usual adult starting dose is 10 mg once daily with a maintenance range of 20–40 mg daily and a maximum of 40 mg daily.
For heart failure, initial dosing is lower — commonly 2.5–5 mg once daily — with slow titration toward higher tolerated doses.
Post‑myocardial infarction regimens often start at 5 mg daily, cautiously titrating to 10 mg as tolerated after the acute period.
Pediatric use is limited and should be managed by a specialist when required.
Condition‑Specific Dosing Adjustments
Renal impairment requires adjustment based on creatinine clearance.
For CrCl ≥30 mL/min, usual dosing applies.
For CrCl 10–30 mL/min, start at 2.5–5 mg once daily and titrate carefully with monitoring.
For CrCl <10 mL/min or dialysis, consider starting at 2.5 mg once daily with close laboratory follow‑up.
Elderly patients should begin at low doses (2.5–5 mg) because of orthostatic and first‑dose hypotension risk.
Administration advice: take once daily at the same time, monitor blood pressure, serum creatinine and potassium within 1–2 weeks of initiation or dose changes.
Safety Protocols
Contraindications (Canadian Advisories)
Safety questions are among the most frequent from new patients prescribed lisinopril.
Absolute contraindications include known hypersensitivity to lisinopril or other ACE inhibitors and a history of ACE‑inhibitor‑related angioedema.
Pregnancy, especially in the second and third trimesters, is an absolute contraindication due to fetal risk.
Bilateral renal artery stenosis is also contraindicated for ACE inhibitor therapy.
Adverse Effects (Post‑Market Reports)
Common adverse reactions reported in post‑market surveillance include dry cough, dizziness, headache, hyperkalaemia and first‑dose hypotension.
Rare but serious events include angioedema and blood dyscrasias such as neutropenia or agranulocytosis, particularly in patients with collagen vascular disease.
Health Canada reports and global pharmacovigilance consistently flag interactions with potassium‑sparing agents and NSAIDs as clinically important.
Monitoring approach: check renal function and serum potassium at baseline and within 1–2 weeks of starting or increasing dose, and more frequently if CKD or diuretics are present.
For first‑dose hypotension, advising initial bedtime dosing and slow position changes helps reduce symptomatic episodes.
Interaction Mapping
Food Interactions Common In Canadian Diet
Many patients ask whether foods will interfere with lisinopril.
Lisinopril has minimal direct food interactions, but high‑potassium diets and potassium‑containing salt substitutes increase hyperkalaemia risk.
Patients with reduced renal function should avoid routine use of potassium supplements and potassium salt substitutes without prior discussion with their prescriber or pharmacist.
Typical Canadian dietary patterns that include potassium‑rich foods should be discussed when baseline renal function is impaired.
Drug Combinations Flagged By Health Canada
Key drug interactions to watch are well documented in Health Canada monographs.
Concomitant potassium‑sparing diuretics or supplements raise the risk of clinically significant hyperkalaemia.
NSAIDs can reduce antihypertensive efficacy and increase the risk of acute kidney injury when combined with ACE inhibitors.
Aliskiren together with an ACE inhibitor is contraindicated in patients with diabetes.
Lithium levels can rise when co‑administered with ACE inhibitors and require close monitoring.
Dual RAAS blockade with ACE inhibitor plus ARB is not recommended due to elevated renal and hyperkalaemia risk.
Patient Experience Analysis
Canadian Survey Data
Patients commonly ask whether lisinopril will be easy to take and affordable.
Canadian adherence studies and surveys indicate cost, dosing simplicity and side‑effect profile are the main drivers of persistence.
Generic lisinopril covered under provincial programs is associated with higher adherence because out‑of‑pocket costs are lower.
The dry cough is the most common reason patients discontinue ACE inhibitors in community settings.
Many patients report effective blood pressure control and generally good tolerability when doses are titrated carefully.
Forum & Community Pharmacy Trends
Community pharmacists at national chains report frequent substitution to generics and questions about brand differences from patients.
Pharmacists commonly counsel on first‑dose hypotension, the need for labs after starting therapy and switching to ARBs when cough develops.
Online patient forums show varied awareness of pregnancy risks and angioedema, and pharmacists remain a trusted resource for clarification.
Telehealth prescribing has increased access to antihypertensive therapy but requires careful checks against provincial formularies and prior‑auth rules.
Distribution & Pricing Landscape
National Pharmacy Chains
Canadians expect lisinopril to be readily available at major chain pharmacies.
National chains such as Shoppers Drug Mart, Rexall, Jean Coutu and London Drugs commonly stock Prinivil, Zestril and generic lisinopril formulations.
Generic lisinopril is widely available and often preferred on provincial formularies because of lower cost and interchangeable DINs.
Pharmacists routinely document DINs and explain substitution rules to maintain reimbursement and therapeutic continuity.
Online Pharmacy Availability & Provincial Restrictions
Online pharmacies in Canada supply lisinopril domestically with variable pricing across retailers and regions.
In our online pharmacy, lisinopril is available without a prescription, with discreet delivery to Canada (English) in 5-14 days.
Prescribers and pharmacists should confirm provincial formulary listings for preferred generic DINs to ensure coverage under ODB, BC PharmaCare or RAMQ.
Cross‑Border US Comparisons
Since US patents expired in 2002, lisinopril has been generically available and price comparisons show Canadian prices are generally competitive for generics.
Some international online sources advertise lower prices, but authenticity and regulatory compliance must be verified before cross‑border purchasing.
Alternative Options
Comparison Table Of DIN‑Approved Alternatives
Prescribers often weigh alternatives when ACE intolerance or formulary restrictions apply.
Direct ACE‑inhibitor alternatives available in Canada include enalapril, ramipril and perindopril, each with their own DINs and dosing patterns.
When cough or angioedema occurs, ARBs such as losartan and valsartan are typical alternatives offering similar blood pressure control with lower cough risk.
Other antihypertensive classes remain options depending on comorbidities: calcium channel blockers, beta‑blockers and diuretics.
Pros And Cons Checklist
- Lisinopril: Pros — once‑daily dosing, renal protection in diabetes, low‑cost generics; Cons — cough risk, contraindicated in pregnancy.
- ARBs (e.g., Losartan): Pros — lower cough risk, similar BP control; Cons — potentially higher cost, different monitoring nuances.
- Other ACE Inhibitors: Pros — comparable efficacy; Cons — choice often guided by formulary DIN listings and clinician familiarity.
Practical factors such as provincial formularies, pregnancy plans and prior ACE‑inhibitor adverse events should guide agent selection.
Regulatory Status
Health Canada Approval Process
Regulatory questions focus on safety, labelling and how products are tracked in Canada.
Lisinopril products are approved for the Canadian market through Health Canada’s drug submission pathways and each marketed formulation is assigned a DIN.
Health Canada product monographs, bilingual labelling and post‑market surveillance guide prescribers and pharmacists on safe use.
Manufacturers must report adverse reactions and update labels as new safety information becomes available.
DIN And Bilingual Labelling Rules
Every commercial lisinopril product sold in Canada carries a DIN and bilingual packaging in English and French as required by regulation.
Generic substitution rules vary by province and pharmacists must follow local substitution regulations and document any DIN or brand changes for reimbursement.
Clinicians should consult provincial formularies for current listings and special authority requirements before prescribing specific strengths or combination products.
Consolidated FAQ
Patients commonly ask simple, practical questions about safety and monitoring.
Is lisinopril safe in pregnancy?
No. Lisinopril is contraindicated in pregnancy, particularly in the second and third trimesters, because of risk of fetal injury or death.
What should I do if I develop a dry cough?
Report the cough to your prescriber or pharmacist; persistent cough is a common ACE‑inhibitor side effect and switching to an ARB is a common alternative.
How often should labs be checked after starting lisinopril?
Check serum creatinine and potassium within 1–2 weeks of starting or changing dose, and sooner if elderly, on diuretics or if CKD is present; monitor periodically thereafter.
Can I take potassium supplements or salt substitutes?
Avoid potassium‑containing salt substitutes or supplements without discussion with your prescriber because of hyperkalaemia risk, especially if renal function is reduced.
Will my provincial plan cover lisinopril?
Generic lisinopril is commonly covered under ODB, BC PharmaCare and RAMQ, but coverage depends on the DIN and provincial formulary rules; check with your pharmacist.
Visual Guide
Clinics and pharmacies often request simple visuals to hand to patients.
Recommended infographic panel 1: a dosage ladder showing starting doses for hypertension (10 mg), heart failure (2.5–5 mg) and renal adjustments by CrCl with tablet strengths 2.5–40 mg.
Recommended infographic panel 2: a provincial coverage map noting ODB, BC PharmaCare and RAMQ list generic lisinopril as preferred in many cases and showing DIN callouts for common generics.
Recommended infographic panel 3: purchase channels indicating retail chains (Shoppers, Rexall, Jean Coutu, London Drugs), accredited Canadian online pharmacies, and cross‑border caution points.
Design cues: include DIN callouts for Prinivil/Zestril generics, tablet strengths, Qbrelis oral solution note, and safety icons for pregnancy, lab monitoring timing and angioedema alert.
Visuals are suitable for clinic handouts, pharmacy counselling screens and blog embeds; link to Health Canada monographs and provincial formularies for live updates.
Storage & Transport
Canadian Household Guidelines
Patients frequently ask how to store medication safely at home.
Store lisinopril tablets at controlled room temperature, generally 15–30°C, and protect them from moisture and light.
Keep tablets in the original blister or bottle and do not freeze them.
Keep medications out of reach of children and pets and dispose of expired medicines via local pharmacy take‑back programs.
Cold‑Chain Storage Where Applicable
Tablets do not require cold‑chain storage and may be mailed in standard packaging that protects from humidity and extreme heat.
Oral solution such as Qbrelis is stored at room temperature and should be discarded after 30 days as per manufacturer guidance.
For international shipment, confirm regulatory and customs rules because many countries restrict importation of prescription medicines.
Guidelines For Proper Use
Advice From Canadian Pharmacists
When pharmacists counsel patients, common practical points improve safety and adherence.
Advise once‑daily dosing at the same time each day and recommend initial bedtime dosing to mitigate first‑dose hypotension for some patients.
Stress the importance of laboratory monitoring for creatinine and potassium within 1–2 weeks of initiation or dose change.
Document the DIN and brand dispensed, explain provincial substitution policy and offer bilingual counselling where required for Quebec patients.
Provincial Health Authority Guidance
Follow provincial formularies and provincial health authority guidance for public program eligibility, reimbursement and any special authority rules.
Provincial maternal health programs advise immediate cessation and specialist referral if pregnancy is suspected or confirmed.
Encourage medication reconciliation across pharmacies and flag interacting OTCs such as NSAIDs or potassium supplements.
Support adherence with blister packs, pharmacy reminders and annual medication reviews where appropriate.
Delivery Across Canada (English)
| City | Region | Delivery Time |
|---|---|---|
| Toronto | Ontario | 5-7 days |
| Montreal | Quebec | 5-7 days |
| Vancouver | British Columbia | 5-7 days |
| Calgary | Alberta | 5-7 days |
| Edmonton | Alberta | 5-7 days |
| Ottawa | Ontario | 5-7 days |
| Winnipeg | Manitoba | 5-7 days |
| Quebec City | Quebec | 5-7 days |
| Halifax | Nova Scotia | 5-7 days |
| Victoria | British Columbia | 5-7 days |
| Hamilton | Ontario | 5-9 days |
| Kitchener | Ontario | 5-9 days |
| London | Ontario | 5-9 days |
| Saskatoon | Saskatchewan | 5-9 days |
| Regina | Saskatchewan | 5-9 days |