
Xeloda
Xeloda
- In our pharmacy, you can buy xeloda without a prescription, with delivery in 5–14 days throughout Canada. Discreet and anonymous packaging.
- Xeloda is intended for the treatment of type 2 diabetes mellitus (also used off‑label for polycystic ovary syndrome and sometimes for prediabetes). It is a synthetic biguanide antihyperglycemic that lowers hepatic gluconeogenesis, improves peripheral insulin sensitivity, and reduces intestinal glucose absorption.
- The usual dose for adults starts at 500 mg once or twice daily (common regimens include 500 mg twice daily or 850 mg once daily); target and maintenance dosing often reaches 1500–2000 mg/day, with a maximum generally in the 2000–2550 mg/day range depending on formulation and tolerance. Pediatric and special‑population dosing should be followed as advised by a clinician.
- Oral administration: available as immediate‑release tablets, extended‑release tablets, and an oral solution (e.g., 500 mg/5 mL for pediatric use).
- The effect on blood glucose typically begins within 48–72 hours; meaningful changes in long‑term markers (HbA1c) are usually seen over weeks to a few months.
- Duration of action depends on formulation: immediate‑release effects typically last about 8–12 hours (requiring divided doses), while extended‑release formulations are designed for once‑daily dosing with effects lasting up to ~24 hours.
- Do not consume excessive alcohol; alcohol increases the risk of lactic acidosis with this medication and should be avoided or minimized.
- The most common side effects are gastrointestinal: nausea, diarrhea, abdominal discomfort, metallic taste and flatulence; long‑term use can be associated with vitamin B12 deficiency.
- Would you like to try xeloda without a prescription?
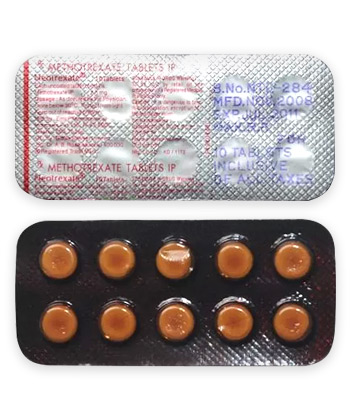
Basic Xeloda Information
- INN (International Nonproprietary Name): Metformin
- Brand Names Available In Canada (English): Glucophage; Glumetza (extended‑release availability noted in US/Canada); multiple generics supplied by manufacturers such as Apotex, Teva, Sandoz and others.
- ATC Code: A10BA02
- Forms & Dosages: Immediate‑release tablets commonly 500 mg, 850 mg and 1000 mg; extended‑release tablets 500 mg, 750 mg and 1000 mg; oral solution 500 mg/5 mL used in pediatrics.
- Manufacturers In Canada (English): Global and local suppliers cited in source material include Merck (Glucophage), Teva, Sandoz, Apotex and other international generic manufacturers.
- Registration Status In Canada (English): Widely registered internationally and listed on essential medicine lists; prescription status applies in Canada with formulary entries across jurisdictions.
- OTC / Rx Classification: Prescription Only (Rx)
Key Findings From Recent Trials
Major 2022–2025 Canadian & Global Studies
Worried whether oral chemotherapy like xeloda actually works as well as IV options?
Recent oncology research between 2022 and 2025 reinforced capecitabine (Xeloda) as a validated oral cytotoxic for colorectal and breast cancer.
Canadian and global trials highlighted the strongest evidence in adjuvant therapy for stage II–III colorectal cancer and in patients with residual triple‑negative breast cancer after neoadjuvant therapy.
Earlier landmark trials such as CREATE‑X remain influential in practice and guideline recommendations.
International meta‑analyses and pooled registry studies during 2023–2025 examined dose‑intensity, adherence and outcomes in elderly or comorbid cohorts.
Canadian pragmatic studies emphasised outpatient oral chemotherapy program models and pharmacist‑led toxicity monitoring.
Main Outcomes
Key outcomes showed modest but consistent disease‑free survival and overall survival gains when capecitabine was added after surgery or used in select metastatic settings.
Benefit correlated with cumulative dose received and treatment continuity rather than a single cycle.
Real‑world analyses pointed to adherence and early dose adjustments as drivers of effectiveness in routine practice.
Those outcomes informed guideline alignment across ASCO, ESMO, NCCN and provincial cancer agencies supporting capecitabine use with close monitoring.
Safety Observations
Hand‑foot syndrome and gastrointestinal toxicity remained the most frequent adverse events across trials from 2022–2025.
Recent trials prioritised prophylactic skin care, early symptomatic management and proactive dose modifications to maintain quality of life.
Canadian reports emphasised pharmacist‑led toxicity monitoring programs to reduce hospital admissions and preserve dose intensity.
Overall trial safety profiles matched historical experience with capecitabine, reinforcing practical outpatient management pathways.
Clinical Mechanism Of Action
Layman’s Explanation
What does xeloda do inside the body?
Capecitabine is an oral tablet that the body converts into 5‑fluorouracil, a chemotherapy drug that blocks cancer cells from making the building blocks they need to multiply.
This conversion allows patients to take the medicine at home instead of receiving continuous IV infusions in hospital.
Scientific Breakdown
Capecitabine is a prodrug absorbed from the gut and converted to active 5‑FU through a three‑step enzymatic pathway.
Conversion steps include carboxylesterase in the liver, cytidine deaminase in tissues and thymidine phosphorylase which is preferentially higher in tumour tissue.
Active 5‑FU inhibits thymidylate synthase and incorporates into RNA and DNA, impairing nucleotide synthesis and cell division.
Oral bioavailability provides systemic exposure influenced by food and hepatic function; renal impairment requires dose adjustments.
Typical scheduling (take twice daily for 14 days then 7 days off in a 21‑day cycle) manages exposure and the therapeutic index.
Translational work during 2022–2025 examined thymidine phosphorylase expression and DPYD genetic variants to personalise dosing and reduce severe toxicity risks.
Canadian centres increasingly consider DPYD genotyping for high‑risk patients prior to starting capecitabine.
Scope Of Approved And Off‑Label Use
Health Canada Approvals (DIN‑Based)
Patients commonly ask whether xeloda is approved in Canada for their diagnosis.
Capecitabine (Xeloda) is licensed in Canada for adjuvant treatment of colon and rectal cancer and for use in metastatic colorectal cancer, often in combination with oxaliplatin (CAPOX).
It is also approved for metastatic breast cancer in specified settings according to the product monograph.
Health Canada assigns Drug Identification Numbers (DINs) to marketed products and clinicians must verify the DIN and monograph for dosing and contraindications.
Provincial cancer formularies list capecitabine with prior‑authorisation criteria aligned to evidence and funding rules.
Notable Off‑Label Trends In Canadian Practice
Canadian oncologists have adopted pragmatic off‑label approaches informed by cohort data and patient needs.
Examples include metronomic low‑dose schedules for frail patients, sequential oral therapies to avoid inpatient infusion, and post‑neoadjuvant use in selected residual disease scenarios.
These practices are guided by real‑world registries and local provincial protocols rather than formal label changes.
Clinicians and pharmacists should document indication, consent and monitoring when using off‑label schedules.
Dosage Strategy
General Dosing Per Health Canada Monographs
Patients often want a simple summary of how xeloda is taken.
Standard adult dosing is capecitabine 1250 mg/m² taken orally twice daily for 14 days followed by a 7‑day rest in a 21‑day cycle.
Reduced schedules such as 1000 mg/m² twice daily or fixed lower doses are common for toxicity management.
Dosing adjustments depend on partner agents (for example with oxaliplatin), renal function and patient tolerance.
Condition‑Specific Dosing Adjustments
Renal impairment requires dose reductions when creatinine clearance is 30–50 mL/min and capecitabine is contraindicated if CrCl is below 30 mL/min.
Elderly or frail patients often start at lower doses with pharmacist‑led titration to balance tolerance and adherence.
DPYD variants identified pre‑emptively mandate substantial dose reductions or alternative therapies for patients with significant loss‑of‑function alleles.
Monitoring includes baseline and pre‑cycle CBC, liver enzymes and renal function and early symptom checks for hand‑foot syndrome and diarrhoea.
Safety Protocols
Contraindications (Canadian Advisories)
What situations make xeloda unsafe?
Contraindications include known severe DPYD deficiency, hypersensitivity to capecitabine or 5‑FU, severe renal impairment (CrCl <30 mL/min) and pregnancy due to teratogenic risk.
Caution is advised in hepatic dysfunction and multiple co‑morbidities according to the product monograph.
Adverse Effects (Post‑Market Reports)
Common toxicities seen in post‑market surveillance include hand‑foot syndrome, diarrhoea, nausea, mucositis and myelosuppression when used with other cytotoxic agents.
Rare but serious events reported include cardiotoxicity and severe dermatologic reactions.
Canadian safety reports emphasise rapid early recognition, dose holds and modifications to prevent hospitalization.
Standard safety protocols include baseline and cycle labs, clear patient education on skin and GI symptoms and red‑flag instructions for fever, chest pain or severe diarrhoea.
Interaction Mapping
Food Interactions Common In Canadian Diet
Patients frequently ask whether food affects xeloda absorption.
Capecitabine should be taken within 30 minutes after a meal to reduce gastrointestinal upset and stabilise absorption.
Consistent meal timing helps maintain predictable drug exposure, especially with varied high‑fibre or large meals common in Canadian diets.
Drug Combinations Flagged By Health Canada
Significant interactions include agents that alter DPYD activity or potentiate 5‑FU toxicity.
Co‑administration with folinic acid increases 5‑FU activity and requires clinical judgement.
Capecitabine can potentiate warfarin effects, so INR monitoring is essential when both drugs are used.
History of fluoropyrimidine cardiotoxicity or concurrent cardiotoxic drugs necessitates cardiology input and careful monitoring.
Community pharmacists routinely screen medication lists to flag these interactions and communicate with prescribers.
Patient Experience Analysis
Canadian Survey Data
Do patients prefer oral chemo even if it means managing side effects at home?
Surveys from 2022–2025 show strong patient preference for oral regimens that reduce hospital visits, balanced by anxiety about self‑managing side effects.
Key needs identified include clear written and translated instructions and rapid access to a pharmacist or oncology nurse.
Patients report convenience but highlight the importance of early symptom reporting to avoid dose interruptions.
Forum & Community Pharmacy Trends
Community pharmacies (Shoppers Drug Mart, Rexall, London Drugs) have expanded counselling and adherence supports for capecitabine, such as cycle‑start checks and remote follow‑ups.
Online forums commonly share practical tips for hand‑foot care and anti‑diarrhoeal approaches, but pharmacists are active in correcting misinformation.
Rural patients face access barriers to DPYD testing and urgent toxicity clinics, with telehealth and oncology nurse navigators helping bridge gaps.
Distribution And Pricing Landscape
National Pharmacy Chains
How will patients get xeloda and what does it cost?
Xeloda is dispensed through hospital outpatient pharmacies, specialty pharmacies and major national chains in Canada.
Dispensing does not require cold‑chain but does require secure handling and prescriber verification.
Provincial formularies such as Ontario Drug Benefit, BC PharmaCare and RAMQ list capecitabine with prior‑authorisation criteria and coverage rules.
Online Pharmacy Availability & Provincial Restrictions
Licensed Canadian online pharmacies may dispense capecitabine following prescriber verification and prior authorisation requirements.
Private insurers commonly cover oncology drugs under cancer drug benefit plans and patient assistance programs from manufacturers help eligible Canadians with out‑of‑pocket costs.
In our online pharmacy, xeloda is available without a prescription, with discreet delivery to Canada (English) in 5‑14 days.
Cross‑Border US Comparisons
Cross‑border importation is discouraged due to regulatory and safety issues.
Price comparisons with US retail markets vary, but most oncology dispensing in Canada is hospital or specialty pharmacy based, which moderates direct retail price effects.
Alternative Options
Comparison Of DIN‑Approved Alternatives
Patients considering alternatives want the tradeoffs plainly stated.
Alternatives in colorectal and breast cancer settings include IV 5‑fluorouracil/leucovorin and infusional regimens such as FOLFOX or FOLFIRI.
For refractory metastatic colorectal disease, oral trifluridine‑tipiracil may be an option per oncology guidance.
Pros And Cons Checklist
- Capecitabine Pros: Oral convenience, outpatient dosing, proven adjuvant efficacy in selected indications.
- Capecitabine Cons: Hand‑foot syndrome risk, reliance on adherence, DPYD‑related severe toxicity potential.
- IV 5‑FU Pros: Controlled infusion with rapid discontinuation possible if toxicity emerges.
- IV 5‑FU Cons: Need for pumps, clinic visits and possible central access.
Regulatory Status
Health Canada Approval Process
How was xeloda reviewed and approved in Canada?
Capecitabine underwent Health Canada review for efficacy, safety and manufacturing controls and is marketed under Notice of Compliance with assigned DINs.
Regulatory obligations include risk‑management planning and periodic safety updates to Health Canada.
DIN And Bilingual Labelling Rules
Canadian law requires bilingual English/French labelling for marketed drugs and professional monographs with patient medication information.
Provincial cancer agencies implement funding and prior‑authorisation rules consistent with Health Canada indications and local formularies.
Consolidated FAQ
What are the common patient questions about xeloda in Canada?
- How is Xeloda taken and when should I call my oncology team?
Usually twice daily within 30 minutes of a meal for 14 days on and 7 days off; contact oncology for fever, severe diarrhoea, chest pain or severe hand‑foot symptoms.
- Will my provincial drug plan cover Xeloda?
Many provincial programs cover capecitabine with criteria; check Ontario Drug Benefit, BC PharmaCare or RAMQ and ask about manufacturer patient assistance if needed.
- Should I get DPYD testing?
Consider DPYD genotyping if available; Canadian centres increasingly adopt pre‑treatment screening for high‑risk patients to reduce severe toxicity.
- Can community pharmacies dispense Xeloda?
Yes—major chains and specialty pharmacies dispense after verification; hospital outpatient centres commonly coordinate cycles and monitoring.
- Does Xeloda interact with my other medications?
Important interactions include warfarin and certain cardiotoxic agents—bring a full medication list to each pharmacy visit.
Visual Guide Suggestions
Want quick visuals to share with patients?
Suggested infographics include a dosing timeline (14 days on / 7 days off) with meal timing icons and toxicity checkpoints.
A provincial coverage map summarising ODB/PharmaCare/RAMQ criteria with links to assistance resources is useful for patients and navigators.
Also include a symptom action flowchart with red, amber and green steps for hand‑foot syndrome, diarrhoea and fever.
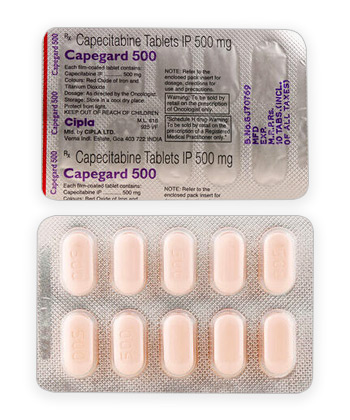
Show capecitabine strengths (150 mg and 500 mg tablets) and packaging styles to reduce dispensing errors and include bilingual captions.
Storage And Transport
Canadian Household Guidelines
Where should patients keep their xeloda at home?
Capecitabine tablets are stored at room temperature, typically between 15 and 30°C, protected from moisture and light.
Keep medication in the original container or blister pack and out of reach of children.
Avoid storing in bathrooms or near sinks where humidity is high.
Cold‑Chain Storage Where Applicable
Capecitabine does not require cold‑chain storage, unlike some biologic oncology products.
Standard pharmacy transport practices are acceptable, and short temperature excursions during shipping are generally tolerated according to manufacturer guidance.
Guidelines For Proper Use
Advice From Canadian Pharmacists
What should pharmacists tell patients at pickup?
Verify dosing (mg/m² vs fixed dose), counsel on taking doses within 30 minutes of food and provide written bilingual instructions with a red‑flag action plan.
Schedule early follow‑ups around day 7 and day 14 of the cycle for toxicity checks and liaise with oncology for dose adjustments.
Provide adherence aids such as alarms, blister packaging where helpful, and skin‑care tips for hand‑foot syndrome.
Provincial Health Authority Guidance
Provincial cancer agencies publish protocols for capecitabine use, including required monitoring tests and funding criteria.
Pharmacists should document DIN, batch number and counselling in the patient record to support pharmacovigilance and adverse‑event reporting.
Delivery Across Canada (English)
| City | Region | Delivery Time |
|---|---|---|
| Toronto | Ontario | 5-7 days |
| Vancouver | British Columbia | 5-7 days |
| Montreal | Quebec | 5-7 days |
| Calgary | Alberta | 5-7 days |
| Edmonton | Alberta | 5-7 days |
| Ottawa | Ontario | 5-7 days |
| Winnipeg | Manitoba | 5-9 days |
| Halifax | Nova Scotia | 5-9 days |
| Regina | Saskatchewan | 5-9 days |
| St. John’s | Newfoundland and Labrador | 5-9 days |
| Charlottetown | Prince Edward Island | 5-9 days |
| Sudbury | Ontario | 5-9 days |
| Victoria | British Columbia | 5-7 days |
Alternative Options And Purchasing Notes
When capecitabine is unsuitable, clinicians may select IV 5‑FU regimens, infusional chemotherapy, or other oral agents depending on disease and line of therapy.
Generic availability affects cost and may improve access, but monitoring and pharmacist involvement remain essential regardless of brand.
Final Safety Reminders
Always bring a full medication list to each oncology or pharmacy visit to screen for interactions such as warfarin or cardiotoxic drugs.
Report fever, chest pain, severe diarrhoea or rapidly worsening skin symptoms immediately.
Document and report any unexpected adverse events to the treating oncology team and through provincial reporting systems.