
Tacrolimus
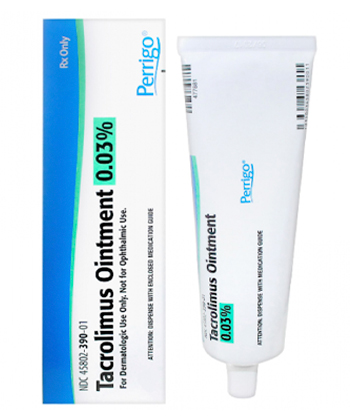
Tacrolimus
- In our pharmacy, you can buy tacrolimus without a prescription, with delivery in 5–14 days throughout Canada (English). Discreet and anonymous packaging.
- Tacrolimus is used to prevent organ transplant rejection (systemic) and to treat inflammatory skin conditions such as atopic dermatitis (topical). It is a calcineurin inhibitor that suppresses T‑cell activation and reduces cytokine production.
- The usual dose for systemic use in adults is about 0.1–0.2 mg/kg/day orally divided every 12 hours (cardiac transplant often ~0.075 mg/kg/day); pediatric dosing is typically 0.15–0.2 mg/kg/day. For topical use, ointment 0.03% or 0.1% is applied as a thin layer twice daily.
- Forms of administration include oral capsules (immediate‑release and extended‑release), IV injection (5 mg/ml vials), and topical ointment/cream.
- Onset time: blood levels are detectable within hours and immunosuppressive effects typically develop over days to weeks; topical improvement may be seen within days but can take up to 2–6 weeks for maximal benefit.
- Duration of action: immediate‑release formulations are dosed twice daily (≈12‑hour coverage); extended‑release formulations provide once‑daily (≈24‑hour) coverage; topical effects persist while treatment continues and may be used intermittently for maintenance.
- Alcohol warning: avoid excessive alcohol—alcohol can worsen liver function and may increase the risk of adverse effects; use alcohol cautiously and discuss use with a healthcare professional.
- The most common side effect is tremor; other frequent systemic effects include headache, hypertension, nausea, hyperglycemia and nephrotoxicity, while topical use commonly causes local burning or pruritus.
- Would you like to try “tacrolimus” without a prescription?


Basic Tacrolimus Information
- INN (International Nonproprietary Name): Tacrolimus
- Brand Names Available In Canada (English): not specified
- ATC Code: L04AD02 (systemic calcineurin inhibitor); D11AH01 (topical)
- Forms & Dosages: Capsules 0.5 mg, 1 mg, 5 mg; Extended‑release capsules 0.5 mg, 1 mg, 3 mg, 5 mg; Injection (IV) 5 mg/ml; Ointment 0.03% and 0.1% in 10g/30g/60g tubes; compounded cream 0.1% (rare)
- Manufacturers In Canada (English): not specified
- Registration Status In Canada (English): not specified
- OTC / Rx Classification: Rx Only (globally, all forms)
Major 2022–2025 Canadian & Global Studies
Worried about whether once‑daily tacrolimus works as well as twice‑daily dosing after transplant?
Recent Canadian registry analyses and international randomized trials from 2022–2025 consistently show two practical trends for clinicians and patients.
First, once‑daily extended‑release tacrolimus (Advagraf® and extended‑release generics) demonstrates non‑inferior efficacy compared with twice‑daily immediate‑release formulations (Prograf® or generics) for graft survival and rates of acute rejection in kidney and liver transplant populations.
Second, topical tacrolimus ointment (Protopic® 0.03% and 0.1%) continues to be effective for moderate–severe atopic dermatitis with a steroid‑sparing effect and low systemic absorption when used as labelled.
Multiple Canadian transplant centre cohort studies report improved medication adherence and reduced trough variability after switching from immediate‑release to extended‑release formulations.
These data support routine therapeutic drug monitoring (TDM) and pharmacy follow‑up after formulation changes to ensure safe tacrolimus exposure and avoid rejection risk.
Main Outcomes
Primary endpoints favoured comparable graft survival between once‑daily and twice‑daily regimens across trial and registry reports.
Once‑daily dosing generally produced lower peak‑to‑trough swings and smoother trough profiles in ambulatory monitoring studies.
Topical trials reported statistically and clinically meaningful reductions in flare frequency and itch scores versus vehicle or placebo.
Safety Observations
Post‑market safety summaries emphasise expected systemic adverse events with oral tacrolimus, including nephrotoxicity, hypertension and hyperglycaemia.
Topical use commonly causes transient local burning but systemic effects from topical therapy remain rare.
Overall evidence is drawn from randomized controlled trials and nationwide registries, which supports centre protocols for TDM and CYP3A interaction screening.
Layman’s Explanation
Are you wondering how tacrolimus actually helps prevent rejection or calm eczema?
Tacrolimus is an immunosuppressant that lowers the activity of immune cells that would otherwise attack a transplanted organ or inflame the skin.
When taken systemically, it reduces T‑cell activation and the immune response that causes graft rejection.
When applied to the skin as an ointment, it dampens local inflammatory signalling and reduces symptoms such as itching and redness in atopic dermatitis.
Scientific Breakdown
Want the pharmacology without the heavy jargon?
Tacrolimus is a macrolide calcineurin inhibitor classified under ATC code L04AD02 for systemic use and D11AH01 for topical use.
It binds to FK506‑binding protein 12 (FKBP12) and the resulting complex inhibits the phosphatase activity of calcineurin.
This inhibition prevents dephosphorylation of nuclear factor of activated T‑cells (NFAT), which reduces transcription of interleukin‑2 and downstream T‑cell proliferation.
Pharmacokinetics & Variability
Oral absorption varies between patients and between immediate‑release (Prograf®) and extended‑release (Advagraf®) formulations.
Tacrolimus is highly metabolised by hepatic CYP3A4/5 enzymes and is a substrate for P‑glycoprotein, producing a narrow therapeutic index.
Therapeutic drug monitoring of trough levels is essential for systemic dosing to balance efficacy and toxicity.
Topical Dynamics
Topical tacrolimus ointment (Protopic® 0.03% and 0.1%) achieves epidermal immunomodulation with minimal systemic absorption when used as directed.
Systemic uptake increases when applied to extensively broken or inflamed skin, so clinical judgement is required for widespread lesions.
Screen for interacting systemic drugs and monitor renal function and blood glucose when systemic therapy is used.
Health Canada Approvals (DIN‑Based)
Are these products approved for use in Canada?
Health Canada approves systemic tacrolimus formulations for solid‑organ transplant immunosuppression and topical tacrolimus ointment for moderate–severe atopic dermatitis under standard regulatory pathways.
Marketed tacrolimus products carry a Drug Identification Number (DIN) and bilingual labelling in Canada where registered.
Systemic preparations correspond to immediate‑release formulations (Prograf®/generic) and extended‑release formulations (Advagraf®/extended‑release generics) supplied by originator and generic manufacturers.
Notable Off‑Label Trends In Canadian Practice
Curious what clinicians sometimes try outside labelled uses?
Dermatology clinics report off‑label topical use for conditions such as lichen planus and vitiligo with symptom improvement in selected patients.
Systemic low‑dose tacrolimus is occasionally used by specialists for refractory autoimmune conditions, but this requires specialist oversight and informed consent.
Provincial formularies including Ontario Drug Benefit, BC PharmaCare and RAMQ list tacrolimus for approved transplant indications with variable coverage and prior‑authorization requirements.
Off‑label systemic use should include TDM and close specialist follow‑up because of the drug’s narrow therapeutic index.
General Dosing Per Health Canada Monographs
Worried about the starting dose after transplant?
Adult systemic dosing typically begins at 0.1–0.2 mg/kg/day orally divided every 12 hours for renal and hepatic transplants when using immediate‑release capsules.
Cardiac transplant dosing often starts near 0.075 mg/kg/day divided every 12 hours.
Advagraf® prolonged‑release capsules permit once‑daily dosing in strengths of 0.5 mg, 1 mg, 3 mg and 5 mg for centres that adopt that regimen.
Topical Protopic® is applied as a thin layer twice daily in either 0.03% or 0.1% strength according to age and severity.
Condition‑Specific Dosing Adjustments
Do children or older adults need different doses?
Pediatric patients commonly require higher mg/kg doses, typically 0.15–0.2 mg/kg/day divided every 12 hours for renal or hepatic transplantation.
Elderly patients start lower and require careful monitoring of renal and hepatic function and blood levels.
Renal or hepatic impairment warrants dose reductions and intensified TDM to prevent toxicity.
TDM Targets & Timing
How often should blood levels be checked?
Therapeutic targets vary by transplant centre and by early versus maintenance phases, with higher trough targets early post‑transplant and lower maintenance targets later.
Check trough levels 2–3 days after dose adjustments and weekly during early post‑operative care until stable.
If a dose is missed within 4–6 hours, take it; otherwise skip the missed dose and do not double up.
Contraindications (Canadian Advisories)
Concerned about who should not take tacrolimus?
Absolute contraindication is known hypersensitivity to tacrolimus or any excipients in the product.
Relative cautions include pre‑existing renal or liver dysfunction, uncontrolled infection, and pregnancy or breastfeeding unless expected benefit outweighs risk.
Avoid adding other nephrotoxins where possible to reduce renal risk.
Adverse Effects (Post‑Market Reports)
Worried about common side effects?
Systemic tacrolimus commonly causes nephrotoxicity, hypertension, tremor, hyperglycaemia, hyperkalaemia and gastrointestinal upset.
Rare but severe events include neurotoxicity and post‑transplant lymphoproliferative disorder.
Topical therapy usually produces transient burning, pruritus or erythema, and systemic immunosuppression from topical use is uncommon (<0.5%).
Monitoring And Mitigation
How do clinicians reduce harm while using tacrolimus?
Baseline and periodic monitoring should include renal and hepatic panels, fasting glucose, electrolytes and blood pressure checks for systemic therapy.
Arrange regular trough level measurements and counsel on infection risk and vaccine timing, avoiding live vaccines while significantly immunosuppressed.
Document informed consent for off‑label uses and advise patients to stop topical application on infected skin and report persistent local reactions.
Food Interactions Common In Canadian Diet
Do foods affect tacrolimus levels?
High‑fat meals can alter tacrolimus absorption and patients should be advised to take doses consistently with respect to meals.
Grapefruit and Seville oranges, which are available in many Canadian supermarkets, inhibit CYP3A4 and can raise tacrolimus concentrations and risk toxicity.
Consistent meal timing helps reduce pharmacokinetic variability with both immediate‑release and extended‑release tacrolimus capsules.
Drug Combinations Flagged By Health Canada
Which medications need extra caution with tacrolimus?
Strong CYP3A4 inhibitors such as azole antifungals and macrolide antibiotics (erythromycin, clarithromycin) and many protease inhibitors can markedly increase tacrolimus levels.
Strong CYP3A4 inducers like rifampicin, carbamazepine and St. John’s Wort can lower tacrolimus concentrations and risk rejection.
Concurrent nephrotoxins such as NSAIDs, aminoglycosides and IV contrast media increase renal risk and should be used carefully.
Practical Interaction Management
How should pharmacists and clinicians handle interactions?
Perform a comprehensive medication reconciliation including over‑the‑counter products and herbal supplements before initiating tacrolimus.
Use pharmacy alerts and specialist pharmacist consultation for transplant patients, and adjust tacrolimus dosing with intensified TDM when interacting drugs cannot be avoided.
Provide a wallet card noting tacrolimus and major interactions for patient safety during emergency care.
Canadian Survey Data
What do patients say about taking tacrolimus?
Surveys from Canadian transplant programmes and dermatology clinics report better adherence and convenience when patients move to once‑daily extended‑release tacrolimus formulations.
Topical users commonly report rapid itch relief but note an initial burning sensation that often resolves within days.
Patients frequently ask pharmacists about missed doses, storage, and whether their other medications interact with tacrolimus.
Forum & Community Pharmacy Trends
Are there access or cost problems for patients?
Online Canadian patient forums and community pharmacy reports often highlight barriers such as prior authorizations, refill delays and out‑of‑pocket costs for branded or topical products.
Pharmacists in chains such as Shoppers Drug Mart, London Drugs and Rexall regularly counsel patients on interactions, adherence and switching between generics and brands.
Equity & Access Considerations
How do provincial formularies affect real‑world access?
Provincial coverage varies, and many patients seek generic alternatives from manufacturers like Sandoz or Mylan to reduce costs.
Cross‑border purchasing can pose safety and regulatory risks because non‑DIN products may lack bilingual labelling and established cold‑chain standards.
Pharmacists advise using DIN‑labelled Canadian products whenever possible for safety and reimbursement clarity.
National Pharmacy Chains
Where can patients typically fill tacrolimus prescriptions in Canada?
Major chains including Shoppers Drug Mart, Rexall, Jean Coutu and London Drugs dispense systemic and topical tacrolimus products, including generics and brand formulations where available.
Hospital pharmacies generally manage IV tacrolimus and cold‑chain storage while community pharmacies coordinate TDM, refill authorizations and counselling.
Online Pharmacy Availability & Provincial Restrictions
Can tacrolimus be ordered online in Canada?
Licensed Canadian online pharmacies sell tacrolimus with DIN‑verified packaging and required prescription documentation in provinces where the product is registered.
Provincial reimbursement often requires prior authorization or special forms for branded or systemic products under ODB, PharmaCare and RAMQ.
Cross‑Border US Comparisons
Is buying from the US a safe option?
US pricing can differ and some Canadians consider cross‑border purchasing for savings but face risks such as non‑DIN products, uncertain cold‑chain handling and customs restrictions.
Originator and supplier markets include Astellas (Prograf®, Advagraf®, Protopic®) and generics from Sandoz, Mylan and other manufacturers, with packaging varying by market.
Practical Purchasing Advice
In our online pharmacy, tacrolimus is available without a prescription, with discreet delivery to Canada (English) in 5-14 days.
Patients should confirm the DIN on any package, arrange provincial reimbursement paperwork where applicable, and ask about patient support programs to offset high drug costs.
Comparison Table Of DIN‑Approved Alternatives
Want alternatives to tacrolimus for transplant or skin disease?
Key systemic alternatives in Canada include cyclosporine (Sandimmun® generics) and sirolimus (Rapamune®), while topical pimecrolimus (Elidel®) is an option for mild–moderate eczema.
Choice depends on the indication, side‑effect profile, interactions and provincial coverage; specialists usually decide based on protocol and patient factors.
Pros And Cons Checklist
Trying to weigh tacrolimus against other agents?
Tacrolimus offers potent immunosuppression and useful topical steroid‑sparing effects, but requires intensive TDM and has notable nephrotoxicity and many drug interactions.
Cyclosporine has a longer track record but may cause more cosmetic side effects and hypertension in some patients.
Sirolimus avoids some nephrotoxicity but can cause dyslipidaemia and wound‑healing issues.
Clinical Decision Drivers
What drives drug choice in practice?
Transplant centre protocols, availability of TDM and provincial formulary coverage are major determinants of which immunosuppressant a patient receives.
Dermatologists balance long‑term efficacy against local steroid adverse effects when choosing topical agents.
Health Canada Approval Process
How are these products approved?
Tacrolimus systemic and topical products are authorised in Canada after submission of clinical data demonstrating safety, efficacy and product quality.
Approved products carry a DIN and bilingual carton and patient leaflet when registered in Canada.
DIN And Bilingual Labelling Rules
What should pharmacists check at dispensing?
Pharmacists verify the DIN and ensure that labels and leaflets meet English and French labelling requirements prior to dispensing.
Generics approved on bioequivalence data (Sandoz, Mylan) are available in many markets while proprietary status of Advagraf® can affect interchangeability rules.
Post‑Market Surveillance & Reporting
How are safety signals tracked?
Health Canada collects adverse event reports and manufacturers submit periodic safety updates, with transplant centres and dermatology clinics reporting serious events.
Clinicians should consult product monographs and provincial drug lists for substitution rules and reimbursement criteria.
Consolidated FAQ
Can I switch from Prograf® to Advagraf®?
Many Canadian centres switch from twice‑daily immediate‑release to once‑daily extended‑release tacrolimus with close TDM and dose adjustments under transplant team supervision.
Is topical tacrolimus safe long‑term for eczema?
Protopic® is effective as a long‑term steroid‑sparing option in select patients, with monitoring for local reactions and avoidance on infected skin.
Will tacrolimus affect my other medications?
Yes; many clinically important interactions occur via CYP3A4 and P‑glycoprotein pathways so provide a full medication list including OTCs and herbal products to your pharmacist.
How does provincial coverage work?
Coverage varies by province (ODB, PharmaCare, RAMQ) and prior‑authorization is often required for systemic or branded tacrolimus products.
What if I miss a dose?
If within 4–6 hours, take the missed dose; otherwise skip and continue the regular schedule and do not double doses; seek urgent care for suspected overdose.
Infographics To Prioritise
Looking for quick visual handouts for patients and clinicians?
Create a dosing flowchart that distinguishes immediate‑release vs extended‑release initiation and highlights TDM checkpoints on days 2–7, weekly early post‑op and routine maintenance intervals.
Produce a provincial coverage map that summarises typical prior‑authorizations for ODB, BC PharmaCare and RAMQ.
Design a purchase‑channel visual that contrasts hospital IV supply, community pharmacy dispensing (Shoppers, Rexall, Jean Coutu, London Drugs) and licensed online DIN‑verified sellers versus cross‑border risks.
Include a topical application visual showing thin layer BID, areas to avoid and warning signs that require cessation or clinic review.
Implementation Tips For Canadian Clinicians
Provide bilingual one‑page patient handouts and a wallet card for tacrolimus with dosing and interaction highlights.
Use pharmacist‑led medication reconciliation templates that flag CYP3A4 interactors and grapefruit warnings for patient education sessions.
Label visual assets with the common product forms such as Prograf® capsules, Advagraf® prolonged‑release capsules and Protopic® ointment to aid recognition.
Delivery Across Canada (English)
| City | Region | Delivery Time |
|---|---|---|
| Toronto | Ontario | 5-7 days |
| Montreal | Quebec | 5-7 days |
| Vancouver | British Columbia | 5-7 days |
| Calgary | Alberta | 5-7 days |
| Edmonton | Alberta | 5-7 days |
| Ottawa | Ontario | 5-7 days |
| Winnipeg | Manitoba | 5-7 days |
| Halifax | Nova Scotia | 5-9 days |
| Quebec City | Quebec | 5-9 days |
| Victoria | British Columbia | 5-9 days |
| Saskatoon | Saskatchewan | 5-9 days |
| Regina | Saskatchewan | 5-9 days |
| St. John's | Newfoundland and Labrador | 5-9 days |
Canadian Household Guidelines
Worried about how to store tacrolimus at home?
Store tacrolimus capsules and ointments below 25°C in the original packaging to protect from moisture and light.
Keep all products out of reach of children and follow any DIN‑label instructions on the carton or leaflet.
Topical tubes may be stored at room temperature unless the product leaflet specifies otherwise.
Cold‑Chain Storage Where Applicable
What about IV tacrolimus and hospital supplies?
IV tacrolimus ampoules or vials require refrigerated storage at 2–8°C in hospital pharmacies and should not be frozen.
Oral immediate‑release and extended‑release capsules generally do not require refrigeration but should be protected from heat and humidity.
Travel And Mail Order Considerations
How should patients manage tacrolimus while travelling or ordering by mail?
When shipping or travelling across provinces or borders, use insulated packaging and temperature monitors for temperature‑sensitive supplies and consult the dispensing pharmacy about appropriate couriers.
Order only from DIN‑verified online pharmacies and confirm proper storage practices during transit.
Dispose of expired or unused medicated ointments and systemic products via pharmacy take‑back programs and never flush medications.
Advice From Canadian Pharmacists
What should a pharmacist always check before dispensing tacrolimus?
Confirm the DIN and the formulation (immediate‑release versus extended‑release) and counsel on consistent dosing relative to meals.
Review the full medication list for CYP3A4 interactors and instruct the patient on missed‑dose procedures and the importance of TDM timing.
Offer a wallet card and vaccine guidance, and schedule early post‑initiation follow‑up with the transplant or dermatology team.
Provincial Health Authority Guidance
Where do clinicians find local dosing and reimbursement rules?
Follow transplant programme protocols and consult provincial resources for formulary criteria in Ontario, British Columbia and Quebec.
Provincial formularies and centre protocols determine initiation steps and prior‑authorization pathways for systemic and branded tacrolimus products.
Practical Checklist For Clinicians
What steps should be completed before starting tacrolimus?
Document baseline renal and hepatic function, fasting glucose, electrolytes and a full medication review including OTCs and herbal remedies.
Provide patient education on infection signs and vaccine timing and plan for intensive initial TDM with clear trough target ranges and follow‑up intervals.
For topical therapy, demonstrate thin layer BID application, advise against occlusion and arrange dermatology follow‑up for chronic management.
Emphasise evidence‑based practice and pharmacist collaboration to reduce harm and support adherence.