Zyloprim
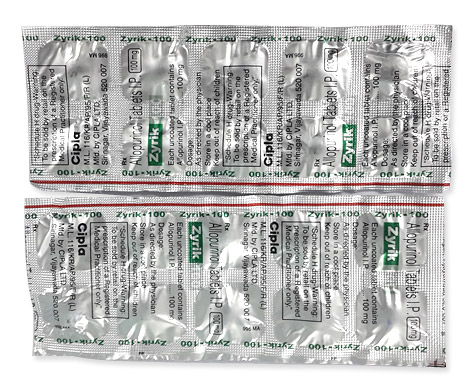
Zyloprim
- Zyloprim (allopurinol) is normally sold in pharmacies and is officially prescription-only in Canada and most countries; some pharmacies may dispense it without a receipt, but a prescription is legally required and medical supervision is recommended.
- Zyloprim is used to treat gout, hyperuricemia and prevent uric acid complications (including tumour lysis syndrome); it is a xanthine oxidase inhibitor that reduces uric acid production.
- The usual adult starting dose for gout is 100 mg once daily, increasing by about 100 mg each week to achieve target serum uric acid (typical maintenance 200–300 mg/day); the maximum is 800 mg/day (split doses recommended above 300 mg/day).
- Administration is usually oral tablets (100 mg and 300 mg scored tablets); an intravenous powder for injection (500 mg vial) is available in some markets for specific indications.
- Zyloprim begins to lower serum uric acid within days; clinically meaningful reductions are usually seen within 1–2 weeks—it does not relieve acute gout pain immediately and should not be started to treat a flare.
- The urate-lowering effect is sustained over about 24 hours because of the active metabolite (oxypurinol), so once-daily dosing is typical.
- Avoid excessive alcohol while taking zyloprim—alcohol can raise uric acid levels and trigger gout flares and may worsen side effects.
- The most common side effect is skin rash (other frequent effects include gastrointestinal upset such as nausea or diarrhea and dizziness); severe hypersensitivity reactions are rare but serious.
- Would you like to try zyloprim without a prescription?
Basic Zyloprim Information
- INN (International Nonproprietary Name): Allopurinol
- Brand Names Available In Canada (English): Zyloprim
- ATC Code: M04AA01
- Forms & Dosages: Oral tablets 100 mg (scored) and 300 mg (scored); Powder for injection 500 mg vial
- Manufacturers In Canada (English): Not specified
- Registration Status In Canada (English): Not specified
- OTC / Rx Classification: Prescription (Rx-only)
Key Findings From Recent Trials
Major 2022–2025 Canadian & Global Studies
Patients and prescribers want to know whether starting low and titrating really helps with persistence and safety.
Recent pragmatic cohort analyses in Canada and international registry reviews from 2022–2025 support allopurinol as first-line urate-lowering therapy using a treat-to-target approach.
These studies emphasised starting at lower doses and gradual titration to improve early persistence and reduce discontinuation.
Registry and meta-analytic work consistently used serum urate targets below 360 µmol/L (less than 6 mg/dL) as the goal of therapy.
Main Outcomes
Treat-to-target titration using low-start regimens achieved target urate levels more reliably than fixed low-dose strategies in real-world cohorts.
Maintaining serum uric acid under 360 µmol/L correlated with fewer gout flares over months to years of follow-up.
Typical titration strategies started at 100 mg daily and increased by approximately 100 mg increments until target urate or maximum tolerated dose.
Short-course high-dose regimens (600–800 mg/day) remained supported for tumour-lysis syndrome prophylaxis as specified in product guidance.
Safety Observations
Pharmacovigilance through 2025 continued to flag HLA-B*5801–associated severe cutaneous adverse reactions as the primary safety concern prompting pre‑treatment screening in higher‑risk groups.
Most reported adverse events were mild gastrointestinal or dermatologic complaints; severe hypersensitivity reactions were rare but clinically important.
Canadian clinician trends show improved awareness of renal-adjusted dosing and routine laboratory monitoring during initiation and titration.
Practical takeaways from the evidence: start low, titrate slowly, monitor urate and renal function, and screen for HLA-B*5801 when indicated.
Clinical Mechanism Of Action
Layman’s Explanation
People ask how Zyloprim actually lowers uric acid and reduces gout flares.
Zyloprim (allopurinol) blocks the enzyme that makes uric acid, so less uric acid forms and fewer painful crystal deposits occur in joints and tissues.
Scientific Breakdown
Allopurinol is a xanthine oxidase inhibitor that reduces the conversion of hypoxanthine to xanthine and xanthine to uric acid.
The parent drug is metabolised to oxypurinol (also known as alloxanthine), which maintains prolonged xanthine oxidase inhibition.
Pharmacokinetics (Brief)
Oral allopurinol tablets (commonly 100 mg and 300 mg) are well absorbed after administration.
Oxypurinol is renally excreted and has a longer half-life than the parent compound, so plasma accumulation can occur when glomerular filtration rate falls.
Because of renal excretion of the active metabolite, dose reduction or interval extension is standard in impaired kidney function.
Cellular Effects
By blocking xanthine oxidase, intracellular and plasma levels of hypoxanthine and xanthine rise while urate levels fall, decreasing the risk of monosodium urate crystal deposition.
The clinical benefit depends on sustained lowering of serum urate below target values to prevent new crystal formation and to allow gradual dissolution of existing crystals.
Slower titration during initiation helps reduce mobilisation flares as crystals begin to dissolve.
Routine monitoring includes serum urate, renal function, liver enzymes and complete blood counts to track efficacy and safety.
Scope Of Approved & Off-Label Use
Health Canada Approvals (DIN-Based)
Clinicians often ask what Zyloprim is officially approved for in Canada and how DINs affect coverage.
Zyloprim (allopurinol) is marketed in Canada in 100 mg and 300 mg tablets and is classified as prescription-only.
Health Canada requires a Drug Identification Number for marketed presentations, and provincial formularies list allopurinol for chronic gout, uric acid nephropathy and tumour-lysis syndrome prophylaxis under varying criteria.
Notable Off-Label Trends In Canadian Practice
Some prescribers use allopurinol for recurrent calcium oxalate stone prevention at low doses, commonly 200–300 mg daily, based on metabolic findings and stone recurrence.
Paediatric use for genetic hyperuricaemia is weight-based (approximately 10–20 mg/kg/day) under specialist supervision for rare metabolic disorders.
Oncology practice follows product monographs for short-term higher dosing (600–800 mg/day) to prevent tumour-lysis syndrome, with transition back to maintenance dosing after risk subsides.
Across provinces, documentation requirements and DIN-referenced criteria vary for public coverage on ODB, BC PharmaCare and RAMQ.
Dosage Strategy
General Dosing Per Health Canada Monographs
Patients ask what a sensible starting dose looks like and how quickly it should change.
Start allopurinol at 100 mg orally once daily for most adults and increase by roughly 100 mg weekly while monitoring response until the serum urate target is reached.
Typical maintenance doses fall in the 200–300 mg daily range, with split dosing recommended when total daily dose exceeds 300 mg.
Maximum daily dosing may reach up to 800 mg in specialist scenarios, using divided doses.
Condition-Specific Dosing Adjustments
For chronic gout, the preferred approach is treat-to-target titration rather than fixed dosing without labs.
Recurrent calcium oxalate stone prevention commonly uses 200–300 mg daily when indicated by metabolic evaluation.
For tumour-lysis syndrome or overt uric acid nephropathy, short-term dosing of 600–800 mg daily is used per product guidance to reduce rapid uric acid generation.
Renal Dosing Guidance
Impaired kidney function requires reduced starting doses or extended dosing intervals because oxypurinol is renally cleared.
For patients with estimated GFR under about 10 mL/min, consider doses of 100 mg/day or specialist guidance on extended intervals.
Monitor renal function during titration and adjust dose if eGFR changes.
Paediatric And Oncology Regimens
Children requiring allopurinol for genetic uric acid overproduction or TLS are dosed at approximately 10–20 mg/kg/day divided into three doses, with a practical maximum near 400 mg/day under specialist care.
Oncology teams use high-dose short courses for TLS prophylaxis, then transition to maintenance dosing as risk diminishes.
During titration, consider prophylactic anti-inflammatory therapy (colchicine or NSAID) to reduce mobilisation flares where appropriate.
Safety Protocols
Contraindications (Canadian Advisories)
One common concern is which patients should never receive allopurinol.
Absolute contraindications include known hypersensitivity to allopurinol or any ingredient in the product.
Starting allopurinol during an acute gout flare is not advised, although patients already taking it should continue treatment.
Severe hepatic or renal impairment requires specialist oversight before use.
Adverse Effects (Post-Market Reports)
Post-market surveillance in Canada and internationally highlights skin reactions ranging from mild rash to life-threatening SJS/TEN and AHS/DRESS, although severe events are rare.
More common mild adverse effects include nausea, diarrhoea, headache and transient rash or pruritus.
Hematologic or hepatic events occur infrequently and are usually reversible when the drug is stopped and monitored.
Monitoring & Early-Warning Signs
Baseline tests should include serum urate, creatinine/eGFR, liver enzymes and a complete blood count.
Repeat serum urate every 2–4 weeks during titration and every 3–6 months once stable, along with periodic renal and hepatic monitoring.
Stop allopurinol immediately and seek urgent assessment for progressive rash, fever, lymphadenopathy, eosinophilia or signs of systemic involvement that suggest DRESS or SJS/TEN.
Document patient counselling and informed consent for risk discussion, and review concurrent medications that increase risk, such as azathioprine without appropriate dose reduction.
Interaction Mapping
Food Interactions Common In Canadian Diet
Patients often ask whether food affects Zyloprim’s action.
There are no strict pharmacokinetic food interactions, but purine-rich diets and alcohol can raise serum urate and reduce the clinical benefit of urate-lowering therapy.
Counsel on hydration and moderation of red meat, shellfish and alcohol to support therapeutic goals.
Drug Combinations Flagged By Health Canada
Allopurinol significantly increases azathioprine and 6-mercaptopurine toxicity unless the immunosuppressant dose is reduced or an alternative is used.
Use caution with didanosine and certain antiretrovirals, and be mindful that thiazide diuretics can increase urate and may complicate management.
When considering a switch to febuxostat, review cardiovascular history because of specific cardiovascular advisories for that agent.
Practical Pharmacy Checks
Pharmacists should verify concurrent immunosuppressants and flag the chart for azathioprine interactions and appropriate dose modifications.
Check renal function before dispensing and remind prescribers and patients about baseline labs and HLA-B*5801 testing when ethnicity and history indicate higher risk.
Document interaction counselling in the provincial e-health record or pharmacy profile and provide patient handouts about diet, hydration and signs of adverse reactions.
Patient Experience Analysis
Canadian Survey Data
Many patients worry they will have to stop work or tests for monitoring when starting urate-lowering therapy.
Survey data and pharmacy feedback up to 2025 show adherence challenges cluster in the first three months, often because patients experience mobilisation flares or worry about side effects.
Once serum urate targets are achieved, patients consistently report fewer flares and improved daily function.
Common counselling points from pharmacists include starting low and titrating, not stopping during a flare, and knowing when to seek urgent care for rashes.
Forum & Community Pharmacy Trends
Online forums often discuss access to HLA-B*5801 testing and whether switching to febuxostat is necessary after intolerance.
Community pharmacies in major chains report frequent questions about provincial coverage rules and navigating prior approvals on ODB, BC PharmaCare and RAMQ.
Pharmacists emphasise shared decision-making and documentation of counselling and monitoring plans to improve persistence and safety.
Distribution & Pricing Landscape
National Pharmacy Chains
Zyloprim tablets (100 mg and 300 mg) are stocked across major Canadian chains including Shoppers Drug Mart, Rexall, Jean Coutu and London Drugs, as well as independent pharmacies.
Generic allopurinol is commonly available, and pricing for generics tends to be low across Canada.
Online Pharmacy Availability & Provincial Restrictions
Online pharmacy availability is widespread but subject to provincial dispensing laws and e-prescription requirements.
Public coverage varies by province and may require diagnostic documentation or prior approval, so pharmacists can check DIN-based listings for ODB, BC PharmaCare and RAMQ.
In our online pharmacy, zyloprim is available without a prescription, with discreet delivery to Canada (English) in 5-14 days.
Cross-Border US Comparisons
Some patients compare Canadian generic prices with U.S. brand pricing, where single-fill costs for brands can be higher.
Cross-border importation is regulated and personal imports may be restricted, so purchasing through licensed Canadian pharmacies is the usual route.
Pharmacies commonly offer blister packaging and adherence supports at low incremental cost to help with daily dosing and refill reminders.
Alternative Options
Comparison Table Of DIN-Approved Alternatives
Patients often ask what to try if allopurinol is not tolerated or ineffective.
Alternatives in Canada include febuxostat (another xanthine oxidase inhibitor), uricosurics such as probenecid or sulfinpyrazone, and specialist biologics or enzyme therapies like pegloticase or rasburicase for refractory cases or TLS.
Pros And Cons Checklist
Febuxostat can be effective when allopurinol is contraindicated or not tolerated but may carry cardiovascular considerations and formulary restrictions.
Probenecid works by increasing renal uric acid excretion and is useful when renal function is adequate; it is underused because of interaction profiles and monitoring needs.
Pegloticase is an IV option for refractory gout, used in specialist settings due to cost, immunogenicity and monitoring requirements.
When switching between agents, follow guideline-recommended washout or overlap rules, monitor serum urate closely, and coordinate care with specialists where indicated.
Regulatory Status
Health Canada Approval Process
Manufacturers seeking to market Zyloprim in Canada must obtain Health Canada approval and a Drug Identification Number that links the product to its monograph and manufacturer licence.
Health Canada evaluates chemistry, manufacturing and clinical safety data, and post-market vigilance contributes to ongoing advisories.
DIN And Bilingual Labelling Rules
Products marketed in Canada must include bilingual English/French labelling and patient information leaflets in consumer packaging.
Allopurinol is classified as prescription-only nationally, and provincial substitution rules and interchangeability policies determine whether generics may be dispensed in place of brand products.
Serious adverse events should be reported to Canada Vigilance as required, and provincial formularies commonly reference DINs in coverage decisions.
Consolidated FAQ
Patients ask the same five practical questions when they call the pharmacy.
-
Can I Start Zyloprim During A Gout Flare?
Generally avoid initiating allopurinol during an acute flare, but do not stop existing therapy if already taking it.
Delay new starts until the flare subsides or use anti-inflammatory prophylaxis per prescriber guidance.
-
Do I Need HLA‑B*5801 Testing?
Consider testing for patients of higher-risk ancestry and for those with prior severe drug reactions; availability and funding vary by province.
-
How Is Dosing Adjusted For Kidney Disease?
Start at lower doses and titrate more slowly; severe renal impairment may warrant doses around 100 mg daily or extended intervals with specialist input.
-
Will My Provincial Plan Cover It?
Coverage criteria differ by province and plan; pharmacists can check ODB, BC PharmaCare, RAMQ or private formularies using the DIN.
-
What If I Develop A Rash?
Stop the drug immediately and seek urgent assessment for severe reactions; even mild rashes warrant prompt evaluation and documentation.
Visual Guide
Patients and clinic staff often want quick reference visuals to follow at home and in clinic.
Recommended infographic set includes a dosage titration flowchart starting at 100 mg with weekly 100 mg increases, a renal-adjustment matrix with eGFR bands and suggested start doses, a provincial coverage map summarising ODB, BC PharmaCare and RAMQ criteria, and a pharmacy access flow showing prescription, in-store or online ordering and prior-approval steps.
Also include a safety alert strip illustrating signs of severe cutaneous reactions and the guidance to stop drug immediately and seek care.
Design notes: bilingual English/French labels, clear iconography for at-risk populations, printable two-page patient handout and a QR code linking to the Health Canada monograph and provincial formulary pages are helpful for clinic use.
Storage & Transport
Canadian Household Guidelines
Patients frequently ask how to store Zyloprim at home and whether refrigeration is needed.
Store allopurinol tablets at standard ambient conditions, approximately 20–25°C (68–77°F), and protect from moisture and excessive heat.
Keep medication in the original labelled container, out of reach of children, and avoid storage in humid areas such as the bathroom.
Cold-Chain Storage Where Applicable
Oral tablets do not require refrigeration and are stable at ambient temperatures for routine transport and storage.
Hospital powdered injection vials follow manufacturer vial-storage and aseptic reconstitution guidance and are handled by pharmacy sterile compounding procedures.
Dispose of unused or expired tablets via pharmacy take-back programs rather than household waste.
Guidelines For Proper Use
Advice From Canadian Pharmacists
Many patients want practical steps they can follow to reduce flares and stay on therapy.
Start low and titrate gradually while providing written, bilingual counselling explaining not to stop during a flare, the importance of hydration and diet, and how to recognise early signs of adverse reactions.
Offer prophylactic colchicine or an NSAID during initiation where clinically appropriate to prevent mobilisation flares.
Provincial Health Authority Guidance
Follow Health Canada product monographs and provincial formulary criteria for prescription and coverage checks using the DIN.
Coordinate with specialists for tumour-lysis prophylaxis or complex renal dosing scenarios and document monitoring plans in the pharmacy record.
Monitoring Checklist
- Baseline: serum urate, creatinine/eGFR, LFTs, CBC.
- During titration: serum urate every 2–4 weeks and renal/liver checks as clinically indicated.
- Maintenance: serum urate and renal function every 3–6 months once stable.
Screen for HLA-B*5801 where indicated and instruct patients to report rashes, fever or systemic symptoms immediately.
Use blister packs and e-reminder tools to support adherence and document informed counselling in the patient file.
Delivery Across Canada (English)
| City | Region | Delivery Time |
|---|---|---|
| Toronto | Ontario | 5-7 days |
| Montreal | Quebec | 5-7 days |
| Vancouver | British Columbia | 5-7 days |
| Calgary | Alberta | 5-7 days |
| Ottawa | Ontario | 5-7 days |
| Edmonton | Alberta | 5-7 days |
| Winnipeg | Manitoba | 5-7 days |
| Halifax | Nova Scotia | 5-9 days |
| Victoria | British Columbia | 5-9 days |
| Saskatoon | Saskatchewan | 5-9 days |
| St. John’s | Newfoundland and Labrador | 5-9 days |
| Kingston | Ontario | 5-9 days |
| London | Ontario | 5-9 days |
| Charlottetown | Prince Edward Island | 5-9 days |
Alternative Options
Comparison Table Of DIN-Approved Alternatives
When allopurinol is not suitable, alternatives include febuxostat, probenecid, sulfinpyrazone and specialist biologics such as pegloticase or rasburicase.
Febuxostat is another xanthine oxidase inhibitor used for intolerance or inadequate response to allopurinol, with cardiovascular considerations to review.
Probenecid requires good renal function and increases uric acid excretion; it is less commonly used but still appropriate for selected patients.
Pegloticase is an IV enzyme therapy reserved for refractory gout in specialist settings due to cost and immunogenicity concerns.
Pros And Cons Checklist
Consider efficacy, renal function dependence, known adverse-event risks (for example HLA-linked rash with allopurinol and cardiovascular caution with febuxostat), monitoring burden and formulary access.
When switching, follow guideline-recommended overlap or washout rules and monitor urate and symptoms closely during transition.
Storage & Transport Summary
For quick reference: store Zyloprim tablets at ambient temperatures (20–25°C / 68–77°F), protect from moisture, and avoid high humidity.
Tablets do not require refrigeration and may be transported under normal courier conditions.
Hospital vials for IV use follow sterile handling protocols and manufacturer instructions for reconstitution and storage.
Return unused or expired medicines to pharmacy take-back programs for safe disposal.
Guidelines For Proper Use — Checklist
Use this short checklist when initiating or managing therapy with Zyloprim.
- Confirm indication and review contraindications including prior hypersensitivity.
- Obtain baseline serum urate, creatinine/eGFR, LFTs and CBC.
- Consider HLA-B*5801 testing for higher-risk ethnicities or history of severe reactions.
- Start 100 mg daily and plan increments of about 100 mg weekly until target urate or maximum tolerated dose.
- Monitor urate every 2–4 weeks during titration, then every 3–6 months once stable.
- Advise hydration, diet modification, and provide flare prophylaxis when appropriate.
- Instruct patients to stop drug and seek urgent care for progressive rash, fever or systemic symptoms.
Document counselling and monitoring plans in the chart and coordinate with specialists for TLS or complicated renal dosing.