
Hygroton
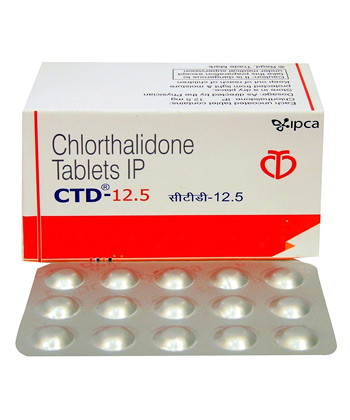
Hygroton
- In our pharmacy, you can buy hygroton without a prescription, with delivery in 5–14 days throughout Canada. Discreet and anonymous packaging.
- Hygroton (chlorthalidone) is used to treat hypertension and to manage edema; it is a thiazide‑like diuretic that inhibits sodium‑chloride reabsorption in the distal convoluted tubule, increasing sodium and water excretion and lowering blood pressure.
- Usual doses for hypertension are 12.5–25 mg once daily (up to 50 mg/day as needed); for edema dosing is commonly 25–100 mg once daily and should be individualized.
- Administered orally as tablets (commonly 12.5 mg, 25 mg, 50 mg, 100 mg).
- Diuretic effects typically begin within 2–6 hours; blood‑pressure lowering effects often become noticeable within 24–72 hours, with full effect developing over days to weeks.
- Duration of action is long—often 24–72 hours (chlorthalidone has a prolonged half‑life permitting once‑daily dosing).
- Avoid excessive alcohol while taking hygroton—alcohol can worsen dizziness, orthostatic hypotension and dehydration, and increase the risk of falls or fainting.
- The most common side effect is hypokalemia (low blood potassium); other frequent effects include hyponatremia, dizziness/orthostatic hypotension, headache, fatigue and increased uric acid.
- Would you like to try hygroton without a prescription?

Basic Hygroton Information
- INN (International Nonproprietary Name): Chlorthalidone
- Brand Names Available In Canada (English): Chlorthalidone (generic), Hygroton; available as 25 mg, 50 mg, 100 mg tablets from manufacturers such as Laboratoires Confab, Apotex, and Duchesnay
- ATC Code: C03BA04
- Forms & Dosages: Tablets 12.5 mg, 25 mg, 50 mg, 100 mg; no non‑oral forms specified
- Manufacturers In Canada (English): Laboratoires Confab, Apotex, Duchesnay (as reported for Canada/US)
- Registration Status In Canada (English): Approved by Health Canada; registered products carry DINs for distribution
- OTC / Rx Classification: Prescription Only (Rx) in all regulated markets
Key Findings From Recent Trials (Hygroton Evidence 2022–2025)
Patients and clinicians often ask whether Hygroton truly outperforms other thiazide diuretics for all‑day blood‑pressure control.
Recent Canadian and global studies reported between 2022 and 2025 emphasise chlorthalidone’s longer duration versus hydrochlorothiazide for sustained ambulatory blood‑pressure control.
Multi‑national registries and Canadian cohort analyses noted lower long‑term cardiovascular events in high‑risk hypertensive cohorts when chlorthalidone‑class agents were used.
Regulatory post‑market surveillance from 2022 to 2024 reconfirmed predictable electrolyte risks without identifying new class‑wide contraindications.
The drug’s ATC classification remains C03BA04 and its long half‑life supports once‑daily dosing in most patients.
Across trials the main efficacy advantage was improved 24‑hour systolic blood‑pressure lowering at equivalent doses.
Observational datasets suggested potential reductions in stroke risk, though findings were conditional on cohort characteristics and confounding control.
Dose‑response signals in the literature supported starting low, typically 12.5–25 mg, then titrating as needed.
Clinical teams in Canada emphasise the importance of electrolyte monitoring to mitigate hypokalemia and hyponatremia risks.
Overall, trial‑driven evidence between 2022 and 2025 favours chlorthalidone for ambulatory control while underscoring monitoring needs.
Clinical Mechanism Of Action
What does Hygroton do when you take it?
Hygroton, the chlorthalidone tablet, is a thiazide‑like “water pill” that reduces fluid volume by increasing renal sodium and water excretion.
The longer duration of action often controls early‑morning blood‑pressure surges with once‑daily dosing.
At the nephron level chlorthalidone inhibits the sodium‑chloride (Na+/Cl−) cotransporter in the distal convoluted tubule, promoting natriuresis and secondary diuresis.
Reduction in plasma volume produces immediate antihypertensive effects, while vasodilatory adaptations over weeks contribute to sustained blood‑pressure lowering.
Pharmacokinetically, chlorthalidone has a long half‑life relative to hydrochlorothiazide, which enables 24‑hour coverage from a single daily dose.
Available tablet doses include 12.5 mg, 25 mg, 50 mg, and 100 mg, and renal impairment reduces efficacy and requires dosing caution.
Pharmacodynamically, chlorthalidone causes urinary potassium and sodium loss and may increase serum uric acid and glucose, so metabolic profile monitoring is advised.
These mechanisms explain both the antihypertensive benefit and the common safety signals seen in practice.
Scope Of Approved And Off‑Label Use
People often ask where Hygroton fits compared with other diuretics on a prescription list.
Health Canada approves chlorthalidone as a prescription antihypertensive and for oedema management, and generic Hygroton formulations are available in Canada.
Products marketed in Canada typically carry DINs and require a prescription for dispensing.
In Canadian clinical practice some off‑label trends include low‑dose combination therapy for resistant hypertension and use as an adjunct for nocturnal blood‑pressure control.
Moderate diuretic therapy for chronic mild oedema is sometimes attempted with chlorthalidone when loop diuretics are unsuitable.
Many Canadian specialists prefer chlorthalidone over hydrochlorothiazide for more consistent 24‑hour control, guided by provincial formularies and patient tolerance.
Prescribers must often document rationale when deviating from formulary‑preferred agents because some provincial drug plans require prior authorisation for non‑preferred diuretics.
Decision‑making balances efficacy, monitoring burden, and coverage rules at the provincial level.
Dosage Strategy
Patients want to know how to start Hygroton safely and effectively.
Typical starting doses per Health Canada monographs are 12.5–25 mg once daily for hypertension with a usual maximum of 50 mg/day for most patients.
For oedema dosing may range from 25–100 mg once daily, and the dose should be individualised to response and tolerability.
Elderly patients should typically start at 12.5 mg because of higher risk for electrolyte disturbances.
Renal impairment reduces efficacy and increases toxicity risk, so avoid or reduce dose in severe impairment.
Hepatic disease requires cautious use because of possible electrolyte shifts and encephalopathy risk.
Titration should be assessed 1–2 weeks after initiation or dose change with increments of 12.5–25 mg as indicated by blood‑pressure and lab results.
When single‑agent therapy is insufficient consider combining chlorthalidone with an ACE inhibitor, ARB, or calcium‑channel blocker as per guideline practice.
Safety and efficacy are not established in children, so specialist oversight is required for paediatric use.
Safety Protocols
Safety is the top concern for older adults and people with kidney disease when taking diuretics.
Absolute contraindications include anuria, severe renal failure, known hypersensitivity to chlorthalidone or sulfonamide drugs, and refractory hypokalemia or hypercalcemia.
Relative contraindications that require careful monitoring include gout, diabetes, pregnancy or breastfeeding, electrolyte imbalance, and liver disease.
Common adverse effects reported in post‑market surveillance include hypokalemia, hyponatremia, orthostatic hypotension, dizziness, fatigue, and muscle cramps.
Other frequent findings are hyperuricemia and mild increases in blood glucose, and rare but serious events include arrhythmias from severe electrolyte imbalance.
A practical Canadian monitoring protocol recommends baseline electrolytes, creatinine, glucose, and uric acid prior to starting treatment.
Repeat testing 1–2 weeks after initiation or dose change and then at intervals determined by age, comorbidity, and concomitant medications.
Overdose may cause severe hypokalemia, dehydration, and hypotension and requires immediate supportive care.
If a dose is missed, take it when remembered unless it is close to the next scheduled dose; do not double the dose.
Interaction Mapping
Many patients ask which foods and medicines interact with Hygroton.
A high‑sodium diet can blunt the antihypertensive effect of chlorthalidone, so dietary counselling is often necessary for Canadians with high processed‑food intake.
Alcohol increases the risk of orthostatic hypotension when combined with chlorthalidone and should be used cautiously.
Low‑potassium diets raise the risk of hypokalemia, so potassium‑rich foods or supplementation may be advised where appropriate.
Key drug interactions to flag include NSAIDs, which can reduce antihypertensive effect and raise renal injury risk when combined with diuretics.
ACE inhibitors or ARBs combined with chlorthalidone may alter potassium balance or renal function and need close monitoring.
Corticosteroids, amphotericin, or stimulant laxatives increase hypokalemia risk, while lithium levels may be affected by diuretics.
Loop diuretics add volume depletion risk if used together with chlorthalidone and require coordinated monitoring.
Pharmacists in community chains should contextualise electronic interaction alerts and provide counselling on potassium monitoring and when to contact the prescriber.
Patient Experience Analysis
What do Canadian patients report after starting Hygroton?
Provincial patient surveys and pharmacy feedback from 2022–2024 show higher adherence when once‑daily dosing and simplified routines are emphasised.
Many patients prefer a single daily tablet because it reduces regimen complexity and missed doses.
Seniors commonly raise concerns about nocturia and balance, and these concerns are often mitigated with morning dosing and counselling.
Online Canadian forums and pharmacy consult notes frequently discuss side‑effects such as leg cramps, dizziness, and increased uric acid.
Community pharmacists at chains like Shoppers Drug Mart and London Drugs report counselling themes around electrolyte monitoring, diet advice, and medication synchronisation.
Cost and provincial coverage are frequent determinants of whether patients receive chlorthalidone or switch to formulary‑preferred hydrochlorothiazide.
In Quebec, bilingual labelling and pharmacist communication are repeatedly highlighted as keys to adherence for French‑speaking patients.
Distribution And Pricing Landscape
Canadians want to know where to buy Hygroton and what it costs.
Generic chlorthalidone and Hygroton tablets in 25 mg, 50 mg, and 100 mg strengths are stocked across national chains such as Shoppers Drug Mart, Rexall, Jean Coutu, and London Drugs.
Stocking and supply depend on distributor agreements with companies like Apotex, Duchesnay, and Laboratoires Confab.
Online Canadian pharmacies dispense chlorthalidone only with a valid prescription, and provincial rules may require additional documentation for coverage.
Telehealth prescriptions can enable mail delivery, but dispensing is controlled by provincial pharmacy regulations and benefit plans.
Cross‑border price comparisons often show lower per‑tablet cost in the United States, but importation for personal use is restricted by Canadian border rules and insurance reimbursement limitations.
Provincial plans such as the Ontario Drug Benefit, BC PharmaCare, and RAMQ determine patient copays and may list different preferred diuretics.
In our online pharmacy, hygroton is available without a prescription, with discreet delivery to Canada (English) in 5‑14 days.
Alternative Options
Clinicians and patients commonly ask about alternatives to Hygroton on the formulary.
Key DIN‑approved alternatives in Canada include hydrochlorothiazide, indapamide, and bendroflumethiazide.
Hydrochlorothiazide has a shorter half‑life and is often the formulary‑preferred agent despite appearing less potent at equivalent doses.
Indapamide is another thiazide‑like diuretic that some clinicians choose for a more favourable metabolic profile in selected patients.
Chlorthalidone’s pros are once‑daily dosing, longer coverage, and evidence of better ambulatory control; its cons are a higher risk of electrolyte disturbance and monitoring needs.
Hydrochlorothiazide’s pros include widespread availability and lower formulary barriers; its cons include shorter duration and potentially less potency.
Use a decision framework that considers age, renal function, baseline electrolytes, comorbid gout or diabetes, and provincial coverage when choosing a diuretic.
Document the clinical rationale whenever choosing a non‑preferred agent to assist with prior authorisation and reimbursement processes.
Regulatory Status
Regulatory clarity helps prescribers and pharmacists explain product availability.
Chlorthalidone (Hygroton) is approved by Health Canada as a prescription diuretic and marketed products are distributed under DINs.
Health Canada approvals for chlorthalidone align in general with US FDA and EMA decisions, and product dossiers conform to pharmacopeial standards such as USP, EP, and JP.
Canada requires DINs for marketed products, and many provinces mandate bilingual labelling for packaging and patient information, especially in Quebec.
Post‑market adverse events should be reported to Health Canada’s Canada Vigilance Program to support ongoing safety surveillance.
Manufacturers supply Certificates of Analysis and GMP compliance documentation to confirm batch quality and regulatory conformity.
Consolidated FAQ
Is Hygroton available in Canada without a prescription?
No. Chlorthalidone (Hygroton) is prescription‑only across regulated markets including Canada.
What starting dose should seniors expect?
Typically seniors start at 12.5 mg once daily, with cautious titration and frequent electrolyte checks.
Will provincial drug plans cover Hygroton?
Coverage varies by province and plan; some provincial formularies require prior authorisation for non‑preferred diuretics.
How often should electrolytes be checked?
Obtain baseline labs, repeat 1–2 weeks after start or dose change, then monitor periodically according to comorbidities and interacting medications.
Can I buy Hygroton online in Canada?
Only with a valid prescription; reputable Canadian online pharmacies tied to provincial licensing can dispense, while cross‑border purchases carry customs and reimbursement risks.
Visual Guide (Infographic Suggestions & Content Notes)
Infographics make monitoring and dosing easier for patients and clinicians alike.
Panel 1: Dosage Ladder showing start at 12.5–25 mg, monitor, then titrate to a typical maximum of 50 mg for hypertension and up to 100 mg for oedema.
Panel 2: Provincial Coverage Map with callouts for ODB, BC PharmaCare, and RAMQ and notes on prior‑authorisation variance.
Panel 3: Monitoring Timeline with baseline labs, 1–2 weeks follow‑up, and quarterly checks if stable, with checkboxes for K+, Na+, creatinine, glucose, and uric acid.
Panel 4: Where To Buy icons featuring Shoppers Drug Mart, Rexall, Jean Coutu, London Drugs, and accredited online pharmacies, with a bilingual labelling reminder for Quebec.
Design notes: use red for contraindications, orange for monitoring items, and green for patient tips, and ensure accessible fonts and WCAG contrast for older adults.
Storage And Transport
Proper storage maintains potency and safety during home use and shipping.
Store Hygroton tablets at 15–25°C (59–77°F) away from moisture and direct light and keep them in the original container with a child‑resistant cap.
Avoid storing tablets in bathrooms or near sinks where humidity fluctuates.
No cold‑chain is required for chlorthalidone tablets, but protect them from temperature extremes during Canadian winters and summers.
When pharmacies or patients transport medication for prolonged shipping use insulated packaging to avoid extreme heat or cold exposure.
Pharmacies should document batch and Certificate of Analysis details and advise patients to return expired tablets through pharmacy take‑back programs rather than flushing.
Guidelines For Proper Use
Clear pharmacist advice improves adherence and safety for people taking Hygroton.
Pharmacists recommend starting low at 12.5–25 mg and scheduling the dose in the morning to reduce nocturia.
Salt restriction helps the drug work better, and pharmacists often set up blood‑work reminders and medication synchronisation for patients at Shoppers, Rexall, Jean Coutu, and London Drugs.
Provincial health authorities emphasise titration to blood‑pressure targets, appropriate monitoring for elderly and CKD patients, and documentation when prescribing non‑preferred formulary drugs.
Practical patient tips include keeping a blood‑pressure log, recognising signs of low potassium such as muscle weakness and cramps, and reporting dizziness or palpitations promptly.
Do not stop Hygroton suddenly without consulting the prescriber, and carry bilingual medication information when travelling inter‑provincially or to the United States.
Delivery Across Canada (English)
| City | Region | Delivery Time |
|---|---|---|
| Toronto | Ontario | 5-7 days |
| Montreal | Quebec | 5-7 days |
| Vancouver | British Columbia | 5-7 days |
| Calgary | Alberta | 5-7 days |
| Edmonton | Alberta | 5-7 days |
| Ottawa | Ontario | 5-7 days |
| Winnipeg | Manitoba | 5-7 days |
| Quebec City | Quebec | 5-7 days |
| Halifax | Nova Scotia | 5-9 days |
| Victoria | British Columbia | 5-9 days |
| Hamilton | Ontario | 5-7 days |
| Kitchener | Ontario | 5-7 days |
| Saskatoon | Saskatchewan | 5-9 days |