
Allopurinol
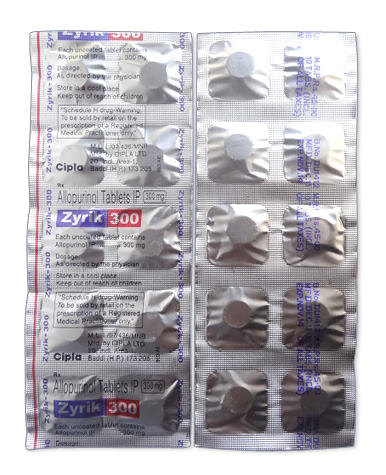
Allopurinol
- In our pharmacy, you can buy allopurinol without a prescription, with delivery across Canada in 5–14 days and discreet packaging; please note that in many jurisdictions allopurinol is officially prescription-only due to risk of serious side effects.
- Allopurinol is used to treat gout (chronic hyperuricemia), prevent uric acid kidney stones and for tumor lysis syndrome prophylaxis; it is a xanthine oxidase inhibitor that blocks uric acid synthesis.
- Usual adult dosing: start at 100 mg/day and titrate up; common maintenance is 200–300 mg/day (mild) or 400–600 mg/day (severe); doses up to 800 mg/day may be used in specialist care; tumor lysis prophylaxis often uses 600–800 mg/day divided. Dose reductions are required in renal impairment; children: ~10–20 mg/kg/day (max ~400 mg/day).
- Form of administration: oral tablets (standard 100 mg and 300 mg); some regions offer 200/400 mg or compounded suspensions; no routine injectable form.
- Onset time: uric acid lowering is gradual — reductions are often seen within days, clinically meaningful improvement within 1–2 weeks, with full effect over 2–4 weeks.
- Duration of action: once-daily dosing is typical; the active metabolite oxypurinol has a long half-life (often 15–30 hours), so the urate-lowering effect persists over 24 hours and requires continuous therapy to maintain levels.
- Alcohol warning: avoid excessive alcohol consumption while taking allopurinol — alcohol can raise uric acid and precipitate gout flares and may worsen liver effects; discuss intake with your healthcare provider.
- The most common side effect is skin rash (stop and seek medical attention if a rash develops); other common effects include gastrointestinal upset, elevated liver enzymes, headache and possible acute gout flares when starting therapy.
- Would you like to try allopurinol without a prescription?
Basic Allopurinol Information
- INN (International Nonproprietary Name): Allopurinol.
- Brand Names Available In Canada (English): Zyloprim and generics (tablets 100 mg, 300 mg).
- ATC Code: M04AA01.
- Forms & Dosages: Oral tablets are standard, commonly 100 mg and 300 mg; some regions may have 200 mg, 400 mg, suspension, or compounded forms; no typical injectable forms.
- Manufacturers In Canada (English): Multiple generics supplied by major global manufacturers such as Teva, Sandoz, Mylan, and originator brands including Sanofi (Zyloric/Zyloprim) are distributed in Canada.
- Registration Status In Canada (English): Widely registered internationally and listed for use in Canada; included on WHO Essential Medicines lists and registered with multiple national regulators.
- OTC / Rx Classification: Prescription-only (Rx) throughout Canada and other jurisdictions due to potential for serious adverse reactions.
Key Findings From Recent Trials
Major 2022–2025 Canadian & Global Studies
Patients and clinicians asked whether long‑term allopurinol still performs as first‑line therapy for gout and hyperuricaemia.
Recent evidence from 2022–2025 continues to support allopurinol as first‑line xanthine oxidase inhibition for chronic hyperuricaemia and gout.
Large international cohort analyses and guideline updates emphasise a treat‑to‑target uric acid approach, aiming for serum urate below 360 μmol/L.
Canadian provincial prescribing data analyses showed improvements in initiation protocols when prophylactic colchicine or an NSAID is used around the start of urate lowering therapy.
Oncology practice data indicate that short‑term high‑dose allopurinol remains used for tumour lysis prophylaxis, but rasburicase is more common for high‑risk patients in many centres.
Main Outcomes
Trial outcomes show consistent long‑term urate lowering with allopurinol and reduced progression of tophi versus non‑urate‑lowering care.
Treat‑to‑target regimens with low‑start dose titration produced higher rates of achieving serum urate <360 μmol/L compared with fixed low doses.
Dose titration strategies beginning at 100 mg/day and increasing based on serum urate were associated with fewer discontinuations for intolerance.
Population cohort analyses in Canada confirmed improved flare control when initiation included prophylactic colchicine for approximately three months.
Safety Observations
Safety signals from 2022–2025 emphasise pharmacogenomic risk mitigation, notably HLA‑B*5801 screening in higher‑risk ethnic groups to reduce severe cutaneous adverse reactions.
Renal dosing algorithms implemented in several provinces correlated with lower hospital admissions for allopurinol‑related toxicity.
Allopurinol hypersensitivity syndrome remains rare but serious, and monitoring programs flagged early rash as a sentinel event requiring immediate drug cessation.
Overall, trial safety data support careful initiation, renal dose adjustment, and appropriate genetic screening where clinically indicated.
Clinical Mechanism Of Action
Layman’s Explanation
Many people ask how allopurinol actually prevents gout attacks and kidney stones.
Allopurinol reduces the production of uric acid by blocking the enzyme that makes it, which lowers serum urate and helps prevent gout attacks, tophi formation and uric acid stones.
Starting treatment slowly and staying on therapy long term reduces the chance of future painful attacks and the gradual buildup of urate deposits.
Scientific Breakdown
Allopurinol (INN: Allopurinol; ATC M04AA01) is metabolised to oxypurinol, which irreversibly inhibits xanthine oxidase.
This inhibition decreases conversion of hypoxanthine and xanthine to uric acid and reduces oxidative by‑products produced by the enzyme.
Oral tablets, commonly 100 mg and 300 mg, deliver systemic exposure and oxypurinol is renally cleared, so creatinine clearance affects dosing and accumulation.
Mechanistically relevant clinical points include slow titration to avoid urate mobilisation that may precipitate flares, and routine use of prophylactic colchicine or an NSAID during initiation to reduce early flares.
Pharmacogenomics: carriers of HLA‑B*5801 have higher risk of severe cutaneous adverse reactions, likely related to altered immune presentation of drug metabolites.
The mechanism supports long‑term use for chronic hyperuricaemia and short‑term high‑dose regimens for tumour lysis prophylaxis when indicated.
Scope Of Approved & Off‑Label Use
Health Canada Approvals (DIN‑Based)
Canadians frequently ask what allopurinol is approved for by Health Canada.
Health Canada classifies allopurinol as prescription‑only and marketed forms in Canada align with the commonly sold tablet strengths of 100 mg and 300 mg, often under brand names such as Zyloprim and various generics.
Each marketed product carries a Drug Identification Number (DIN) that pharmacists check for substitution and provincial reimbursement.
Approved indications include chronic gout and hyperuricaemia, prevention of uric acid nephrolithiasis, and tumour lysis syndrome prophylaxis in oncology protocols when clinicians select it.
Notable Off‑Label Trends In Canadian Practice
Some clinicians consider off‑label allopurinol use for asymptomatic hyperuricaemia in chronic kidney disease, but evidence remains investigational and practice varies by region.
Where rasburicase is inaccessible or restricted, some oncology services use short‑course high‑dose allopurinol for intermediate tumour lysis risk, consistent with real‑world practice patterns.
Pediatric use is limited and mainly oncology‑related, typically dosed at 10–20 mg/kg/day with a common maximum of 400 mg/day in children receiving chemotherapy.
Provincial formularies such as Ontario Drug Benefit, BC PharmaCare and RAMQ list allopurinol under differing criteria, and pharmacists routinely use the DIN to manage substitutions and coverage queries.
Dosage Strategy
General Dosing Per Health Canada Monographs
Patients often want practical starting doses and how escalation works.
General strategy is to start low, commonly at 100 mg/day, and titrate up based on serum uric acid until the treat‑to‑target level is reached.
Maintenance dosing for mild disease is commonly 200–300 mg/day, and severe cases may require 400–600 mg/day, with specialist care sometimes using up to 800 mg/day in selected situations.
Titration decisions should be guided by serum urate measurements and tolerability, and the choice of tablet strength (100 mg, 300 mg) helps with flexible dose adjustments.
Condition‑Specific Dosing Adjustments
Renal impairment necessitates dose reduction because oxypurinol is renally cleared; for patients with creatinine clearance below 20 mL/min, doses are often limited to about 100 mg/day and specialist review is recommended.
Hepatic impairment requires caution and monitoring of liver function tests during therapy.
For tumour lysis syndrome prophylaxis a short‑term regimen of 600–800 mg/day in divided doses is commonly used in adults.
Children receive 10–20 mg/kg/day in divided doses for chemo‑related hyperuricaemia, with a usual maximum of 400 mg/day.
Concurrent colchicine or an NSAID for approximately three months reduces early flares after initiation of allopurinol.
Monitoring should include baseline and periodic serum urate, renal function and liver enzymes, and dose escalation should follow assessment of tolerance and urate response.
Safety Protocols
Contraindications (Canadian Advisories)
Patients commonly ask what would make allopurinol unsafe for them.
Absolute contraindications include known hypersensitivity to allopurinol or any excipients, and prior severe cutaneous adverse reactions such as Stevens‑Johnson Syndrome or Toxic Epidermal Necrolysis.
Initiating allopurinol during an acute gout flare is not advised because it may worsen the attack.
Because of serious risk profiles, Health Canada and product monographs recommend prescription‑only status and careful screening before initiation.
Adverse Effects (Post‑Market Reports)
Skin rash is the most important sentinel sign and any new rash requires stopping allopurinol and urgent assessment.
Common milder effects include gastrointestinal upset, transient liver enzyme elevations, headache and drowsiness.
Initiation can paradoxically trigger acute gout flares, which is why prophylaxis with colchicine or an NSAID is standard practice at the start of therapy.
Allopurinol hypersensitivity syndrome (AHS) is rare but severe, often involving systemic illness and renal or hepatic impairment; risk factors include CKD, concurrent diuretic use and HLA‑B*5801 positivity.
Consider HLA‑B*5801 testing for patients of Korean, Han Chinese or Thai ancestry and for others at higher risk per provincial and specialty guidance.
Adverse events should be reported to Health Canada’s Canada Vigilance Program.
Interaction Mapping
Food Interactions Common In Canadian Diet
Patients often ask whether they must change diet when starting allopurinol.
Allopurinol has no major food absorption issues, but counsel about hydration and limiting high‑purine foods such as red meat and shellfish, which are common in many Canadian diets.
Alcohol, particularly beer and spirits, raises uric acid and undermines urate lowering therapy and should be reduced.
Drug Combinations Flagged By Health Canada
Azathioprine and mercaptopurine interact dangerously with allopurinol through reduced thiopurine metabolism, increasing risk of myelosuppression; dose adjustments or avoidance are required.
Thiazide diuretics can increase serum urate and may raise hypersensitivity risk when combined with allopurinol; these combinations need careful monitoring.
Warfarin and other anticoagulants may require INR monitoring if used with allopurinol.
Febuxostat is redundant with allopurinol and should not be co‑prescribed, whereas probenecid can be complementary in uricosuric strategies when renal function permits.
Pharmacists at major chains will check DINs and interaction flags during dispensing and counsel patients on dietary and drug interaction risks.
Patient Experience Analysis
Canadian Survey Data
A frequent patient worry is whether treatment will actually reduce attacks and how side effects will feel.
Canadian surveys from 2022–2025 show most patients report symptom improvement when allopurinol is titrated appropriately to target serum urate.
Common complaints include early flare frequency, gastrointestinal upset and concerns about skin reactions.
Patients counselled on hydration, diet and flare prophylaxis demonstrate better adherence in community survey data.
Forum & Community Pharmacy Trends
Community pharmacists report high generic substitution rates, with widespread dispensing of generics versus brand Zyloprim and frequent patient questions about pricing and DINs for public coverage.
Online patient forums highlight inconsistent access to HLA‑B*5801 testing and variable provincial coverage for genetic screening.
Oncology patients note disparities in rapid access to rasburicase compared with high‑dose allopurinol across provinces, affecting local prophylaxis choices.
Bilingual counselling (English/French) remains important in Quebec and federal settings, and chain pharmacies provide printed monographs and benefit navigation for public formularies.
Distribution & Pricing Landscape
National Pharmacy Chains
Allopurinol tablets are widely distributed through major Canadian chains including Shoppers Drug Mart, Rexall, Jean Coutu and London Drugs, and via independent pharmacies.
Generics dominate dispensing and pharmacists verify DINs for substitution compliance and coverage.
Chain services like home delivery and auto‑refill help maintain adherence for chronic users.
Online Pharmacy Availability & Provincial Restrictions
Licensed Canadian online pharmacies commonly provide allopurinol, but provincial prescribing rules and Rx requirements govern dispensing and limit direct retail sale without a valid prescription.
Provincial drug plans vary in criteria and copays, and pharmacists check DINs when managing reimbursement and substitutions.
Cross‑Border US Comparisons
Generic tablet prices in Canada are generally lower than branded Zyloprim but may be higher than some U.S. cash prices when exchange rates and import regulations are considered.
Cross‑border purchasing raises regulatory and safety considerations, so pharmacists recommend sourcing through licensed Canadian distributors and verifying DINs.
Alternative Options
Comparison Table Of DIN‑Approved Alternatives
When allopurinol is unsuitable, alternative classes include febuxostat, uricosurics such as probenecid or sulfinpyrazone, and rasburicase for tumour lysis syndrome.
Febuxostat is another xanthine oxidase inhibitor that may be used when allopurinol intolerance or contraindication exists, but cardiovascular safety signals affect its selection.
Probenecid increases renal uric acid excretion and may be useful in underexcretors with adequate renal function, although it has multiple drug interactions.
Rasburicase is an IV enzyme used to rapidly degrade uric acid in TLS and is typically managed in oncology formularies due to cost and administration requirements.
Pros And Cons Checklist
- Allopurinol: Oral, low cost, well studied; cons include hypersensitivity risk and need for renal dosing.
- Febuxostat: Alternative when allopurinol not tolerated; cons include higher cost and cardiovascular safety considerations.
- Probenecid: Useful for underexcretors; cons include ineffectiveness in renal impairment and interaction profile.
- Rasburicase: Rapid TLS treatment; cons include IV route, high cost and restricted oncology access.
Regulatory Status
Health Canada Approval Process
Allopurinol is approved in Canada as a prescription medicine and manufacturers must submit data on safety, efficacy and manufacturing quality for registration.
Manufacturers supply bilingual product monographs, perform post‑market surveillance and report safety signals to Health Canada.
Inclusion on provincial formularies involves separate health technology assessment and negotiation processes, with the DIN required for listing and reimbursement.
DIN And Bilingual Labelling Rules
Each formulation and manufacturer has a unique DIN and federal rules require bilingual labelling in English and French for product monographs and patient leaflets where applicable.
Pharmacies must display or provide bilingual patient information in jurisdictions where required, and adverse events are reportable to Canada Vigilance.
Consolidated FAQ
Can I start allopurinol during an acute gout attack?
No. Do not initiate allopurinol during an acute flare; start after resolution and consider prophylaxis to reduce subsequent flares.
Do I need a genetic test before starting allopurinol?
Consider HLA‑B*5801 testing for patients of Korean, Han Chinese or Thai ancestry, or others at higher risk; testing access and coverage vary by province.
How is dosing adjusted for kidney disease?
Renal dose reduction is required; severe impairment often limits dosing to about 100 mg/day and specialist input is recommended for safe management.
Is generic as effective as branded Zyloprim?
Yes. Generics meet DIN standards and provide equivalent active ingredient and effectiveness; confirm tablet strength (100 mg/300 mg) at dispensing.
Will my provincial plan cover it?
Coverage depends on specific ODB, PharmaCare or RAMQ criteria and the product DIN; pharmacists can check eligibility and suggest substitutions where appropriate.
Visual Guide
The following infographic concepts help patients and clinicians visualise dosing, coverage and safety.
Dosage ladder: start 100 mg → titrate to 200–300 mg → severe cases 400–600 mg (max up to 800 mg in specialist care), with renal adjustment notes for CrCl thresholds.
Provincial coverage flowchart: prescription → DIN check → ODB/PharmaCare/RAMQ criteria → generic substitution as allowed.
Purchase channels: community chains (Shoppers, Rexall, Jean Coutu, London Drugs) vs licensed online pharmacies vs hospital oncology pharmacy for rasburicase.
Safety icons: HLA‑B*5801 testing decision aid, rash red flag and monitoring schedule (baseline and periodic renal/LFT/urate checks) with bilingual captions for federal distribution.
Storage & Transport
Canadian Household Guidelines
Store allopurinol tablets below 25°C (77°F) in the original packaging to protect from light and moisture.
Avoid freezing the product and keep tablets out of reach of children.
Use pharmacy takeback programs at chains such as Shoppers or London Drugs for safe disposal of expired or unwanted medication.
Cold‑Chain Storage Where Applicable
Oral allopurinol requires no cold chain and standard transport conditions are acceptable for short trips.
Injectable alternatives like rasburicase require refrigerated management and are handled by hospital pharmacies with controlled cold‑chain logistics.
For mail delivery, pharmacies should package product to minimise moisture and temperature extremes and include the DIN on shipping labels for traceability.
Guidelines For Proper Use
Advice From Canadian Pharmacists
Pharmacists advise verifying DIN and product strength at dispensing and counselling patients on starting low and titrating based on serum urate.
Recommend flare prophylaxis with colchicine or an NSAID for at least three months after initiation and schedule baseline and follow‑up labs.
Document and consider HLA‑B*5801 testing for at‑risk ethnicities and record results in the patient chart where available.
Teach rash recognition and instruct patients to stop the drug and seek urgent assessment for any suspected severe cutaneous reaction.
Provincial Health Authority Guidance
Ontario, British Columbia and Quebec guidance emphasises formulary navigation and the pharmacist’s role in ODB, PharmaCare and RAMQ applications where criteria exist.
In oncology TLS prevention, coordinate with oncology pharmacy to determine rasburicase versus high‑dose allopurinol based on risk stratification.
Report severe adverse events to Canada Vigilance and provide bilingual counselling aids for patients in Quebec and federal environments.
Patient Access And Ordering
Many patients wonder how quickly they can get allopurinol and whether they need a prescription to order online.
Prescription status remains standard in Canada, and most pharmacies require a valid prescription to dispense allopurinol in accordance with provincial rules.
Pharmacists can assist with provincial formulary queries and generic substitution to reduce cost where appropriate.
In our online pharmacy, allopurinol is available with a prescription, with discreet delivery to Canada (English) in 5‑14 days.
Delivery Across Canada (English)
| City | Region | Delivery Time |
|---|---|---|
| Toronto | Ontario | 5–7 days |
| Montreal | Quebec | 5–7 days |
| Vancouver | British Columbia | 5–7 days |
| Calgary | Alberta | 5–7 days |
| Edmonton | Alberta | 5–7 days |
| Ottawa | Ontario | 5–7 days |
| Winnipeg | Manitoba | 5–7 days |
| Halifax | Nova Scotia | 5–9 days |
| St. John's | Newfoundland and Labrador | 5–9 days |
| Regina | Saskatchewan | 5–9 days |
| Charlottetown | Prince Edward Island | 5–9 days |
| Whitehorse | Yukon | 5–9 days |
| Iqaluit | Nunavut | 5–9 days |
| Yellowknife | Northwest Territories | 5–9 days |
Storage And Disposal Reminders
Keep the tablet bottle for DIN and expiry verification and store allopurinol below 25°C in original packaging away from moisture and light.
Avoid leaving medication in hot cars or gloveboxes during Canadian summers and do not freeze the product.
Use pharmacy takeback programs or municipal hazardous waste programs for unused or expired tablets rather than household trash.
Final Safety Checklist For Patients
Before starting allopurinol, ensure baseline blood tests include serum urate, renal function and liver enzymes.
Discuss HLA‑B*5801 testing if of relevant ancestry or with other risk factors and record results when available.
Arrange follow‑up labs after dose titration and contact a clinician immediately for any rash, fever or unexplained systemic symptoms.
Carry a list of current medications and inform your pharmacist if you are taking azathioprine, mercaptopurine, a thiazide diuretic or warfarin.
Maintain good hydration and reduce high‑purine foods and alcohol to support urate lowering therapy.