
Topro Xl
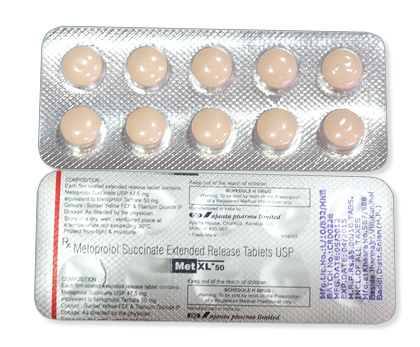
Topro Xl
- In our pharmacy, you can buy topro xl without a prescription, with delivery across Canada in 5–14 days and discreet packaging; note that Toprol XL (metoprolol succinate) is prescription-only in most countries and should be used under medical supervision.
- Toprol XL (metoprolol succinate) is used to treat hypertension, angina, heart failure and to reduce mortality after myocardial infarction; it is a selective beta‑1 adrenergic receptor antagonist (beta‑blocker) that reduces heart rate and cardiac workload.
- Usual dosages vary by condition: hypertension 25–100 mg once daily (maintenance 100–200 mg once daily); angina typically 100 mg once daily up to 200 mg; heart failure start 12.5–25 mg once daily titrating up to 200 mg; post‑MI typically 100–200 mg once daily—dose individualization and titration are common.
- Administered orally as extended‑release tablets or capsules (Toprol XL ER) once daily; immediate‑release metoprolol tartrate is available as tablets for multiple daily dosing and oral solution is rare.
- Onset: effects on heart rate and blood pressure may begin within about 1 hour after an oral dose, with more noticeable blood‑pressure control developing over hours to days with regular dosing.
- Duration of action: the extended‑release formulation provides approximately 24 hours of action when taken once daily.
- Alcohol warning: avoid excessive alcohol — it can worsen dizziness, drowsiness and low blood pressure while taking Toprol XL; discuss alcohol use with your prescriber.
- The most common side effect is fatigue (tiredness); other frequent effects include dizziness, headache, mild nausea and slow heart rate (bradycardia).
- Would you like to try topro xl without a prescription?
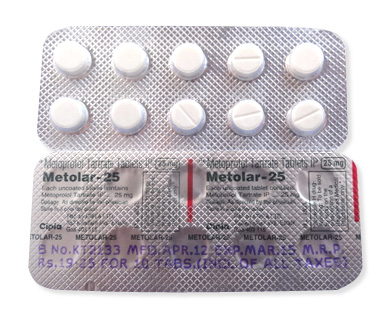
Basic Toprol XL Information
- INN (International Nonproprietary Name): Metoprolol succinate
- Brand Names Available In Canada (English): not specified
- ATC Code: C07AB02 — Selective beta‑blocker, beta‑1 adrenergic receptor antagonist
- Forms & Dosages: Extended‑release tablets 25 mg, 50 mg, 100 mg, 200 mg; capsule extended‑release common in North America; immediate‑release metoprolol tartrate tablets 50 mg, 100 mg (different formulation); oral solution rare
- Manufacturers In Canada (English): not specified
- Registration Status In Canada (English): not specified
- OTC / Rx Classification: Prescription‑only (Rx)
Key Findings From Recent Trials
Major 2022–2025 Canadian & Global Studies
Which recent trials matter for patients taking metoprolol succinate?
Large randomized trials and meta‑analyses from 2022–2025 focused on heart failure with reduced ejection fraction, post‑myocardial infarction care and stable angina.
Canadian cohort studies and provincial registries added real‑world evidence about dosing and persistence over the same period.
International registries confirmed the ongoing role of metoprolol succinate ER in guideline‑directed therapy for HFrEF when titrated to target doses.
Meta‑analyses showed preserved mortality and morbidity benefit versus placebo in these core indications.
However, incremental absolute benefits are smaller compared with newer HFrEF agents such as SGLT2 inhibitors and ARNI.
Real‑world data highlighted that many patients remain under‑titrated from starter doses (12.5–25 mg) toward typical maintenance (100–200 mg/day).
Pharmacists and clinicians in Canada cited titration gaps as a modifiable care target.
Main Outcomes
What clinical endpoints improved with metoprolol succinate?
Trials demonstrate reductions in all‑cause mortality and sudden cardiac death in properly treated HFrEF and post‑MI cohorts.
Improvement in angina frequency and exercise tolerance was consistent in stable ischemic patients.
Benefit size depended on dose achieved and concurrent use of modern heart‑failure therapies.
Registry analyses showed greatest gains when beta‑blockers were uptitrated to guideline targets and combined with ACEi/ARB/ARNI and SGLT2 inhibitors.
Safety Observations
What safety signals appeared across studies and surveillance?
Common adverse events remained fatigue, bradycardia and dizziness, consistent with decades of experience.
Higher discontinuation rates were reported in elderly and frail subgroups, especially when titration was rapid.
Canadian post‑market reporting highlighted falls related to symptomatic hypotension in community‑dwelling seniors.
Trials reinforced the need for heart‑rate and blood‑pressure monitoring during uptitration and after dose changes.
Clinical Mechanism Of Action
Layman’s Explanation
What does metoprolol succinate do in plain language?
It is a once‑daily beta‑1 selective blocker that slows the heart rate and reduces the heart’s workload.
This lowers blood pressure, eases chest pain from angina and helps protect the heart after a heart attack.
In some heart‑failure patients it improves symptoms and long‑term outcomes when used as part of comprehensive therapy.
Scientific Breakdown
How does it work on a molecular level?
Metoprolol succinate is a selective beta‑1 adrenergic receptor antagonist classified under ATC C07AB02.
By blocking beta‑1 receptors in the heart it reduces sympathetic stimulation and myocardial oxygen demand.
That translates into negative chronotropy (slower heart rate), negative inotropy (reduced contractility) and slower AV nodal conduction.
Receptor Pharmacology
What receptor effects should clinicians remember?
At therapeutic doses metoprolol is relatively beta‑1 selective and targets cardiac tissue preferentially.
At higher doses beta‑2 blockade can emerge and increase bronchospasm risk in susceptible patients.
Clinical vigilance is required for patients with asthma or severe COPD.
Pharmacokinetics Of Succinate ER
Why choose the succinate extended‑release salt?
The succinate salt provides once‑daily extended‑release absorption and smoother plasma concentrations than tartrate immediate‑release formulations.
Tablets are commonly available in 25–200 mg strengths for ER dosing flexibility.
Metabolism is primarily hepatic via CYP2D6, so clearance varies by genotype and liver function.
Dose reductions are recommended in moderate hepatic impairment and clinicians should screen for potent CYP2D6 inhibitors.
Advise patients to take the tablet with or immediately after a meal to improve absorption and reduce nausea or dizziness.
Scope Of Approved & Off‑Label Use
Health Canada Approvals (DIN‑Based)
What indications does Health Canada support for metoprolol succinate ER?
Health Canada approvals align with FDA and EMA labels and include hypertension, angina pectoris, heart failure and post‑myocardial infarction management.
Typical monograph dosing starts in ranges of 25–100 mg once daily with maintenance up to 200 mg once daily depending on indication.
For HFrEF the recommendation is to start low and uptitrate cautiously under clinical supervision.
Products sold in Canada carry a DIN for identification and reimbursement purposes.
Notable Off‑Label Trends In Canadian Practice
How do Canadian clinicians use metoprolol off‑label?
Extended‑release metoprolol is commonly used off‑label for once‑daily rate control in atrial fibrillation when clinicians prefer a single daily dose.
Low‑dose metoprolol remains in use for migraine prophylaxis and performance anxiety, though these are less common than cardiovascular uses.
Pediatric use of ER formulations is specialist‑led and considered off‑label in most cases.
Switching between Toprol XL and generic metoprolol succinate ER is frequent for cost and supply reasons, so prescribers should specify DIN and formulation when requesting coverage from provincial plans.
Dosage Strategy
General Dosing Per Health Canada Monographs
What are the typical starting and maintenance doses?
Extended‑release metoprolol succinate is prescribed once daily in doses from 25–200 mg depending on indication.
For uncomplicated hypertension adults often start 25–100 mg once daily with maintenance commonly 100–200 mg daily.
Angina patients frequently use 100 mg once daily with titration up to 200 mg if needed.
Post‑MI regimens target 100 mg once daily, with maintenance usually 100–200 mg.
Condition‑Specific Dosing Adjustments
How should dosing be adjusted for special populations?
Heart‑failure patients should start very low (12.5–25 mg once daily) and uptitrate slowly toward 200 mg as tolerated.
Elderly patients require lower starting doses and closer monitoring for bradycardia and orthostatic hypotension to reduce fall risk.
Hepatic impairment often necessitates dose reduction due to predominant liver metabolism via CYP2D6.
Renal impairment generally does not require adjustment, but monitor clinically at higher doses.
Uptitration is commonly performed every 1–2 weeks where tolerated, aiming for a resting heart rate around 50–60 bpm or symptom‑guided targets.
Abrupt cessation should be avoided and tapering over 1–2 weeks is recommended to reduce rebound ischemia or arrhythmia risk.
Safety Protocols
Contraindications (Canadian Advisories)
When must metoprolol not be used?
Absolute contraindications include severe bradycardia (<45 bpm), second‑ or third‑degree AV block without a pacemaker, sick sinus syndrome, cardiogenic shock and uncompensated heart failure.
Severe peripheral arterial circulatory disorders and hypersensitivity to metoprolol or excipients are also absolute contraindications.
Use with caution in patients with asthma or significant chronic obstructive pulmonary disease because of bronchospasm risk.
Adverse Effects (Post‑Market Reports)
What side effects should patients expect and report?
Common mild effects are fatigue, dizziness, headache, gastrointestinal upset and sleep disturbance.
Moderate risks include symptomatic hypotension, worsening heart failure, pronounced bradycardia and AV block.
Canadian post‑market surveillance has flagged falls in seniors related to symptomatic hypotension and higher discontinuation rates for fatigue.
Pharmacists should counsel patients to check pulse and blood pressure and to recognise signs of masked hypoglycaemia in diabetes.
Tapering before stopping and prompt reporting of syncope or near‑falls are essential safety steps.
Interaction Mapping
Food Interactions Common In Canadian Diet
How does food affect absorption or safety?
Extended‑release metoprolol succinate shows improved and more consistent absorption when taken with food.
Advise patients to take the tablet with or immediately after a meal to reduce dizziness and nausea.
Grapefruit juice is not a major interaction for metoprolol, but alcohol can worsen orthostatic hypotension and dizziness.
Counsel moderation of alcohol, particularly during initiation and titration.
Drug Combinations Flagged By Health Canada
Which drug interactions are most important to avoid?
Non‑dihydropyridine calcium channel blockers such as verapamil and diltiazem potentiate bradycardia and AV block when combined with metoprolol.
Digoxin adds to AV nodal suppression and requires monitoring for bradyarrhythmia.
Some antidepressants and MAO inhibitors can alter haemodynamics when co‑prescribed.
Potent CYP2D6 inhibitors may increase metoprolol levels and raise the risk of bradycardia.
In polypharmacy settings common in Canadian seniors, reconcile AV‑nodal blocking agents with the patient’s prescriber and monitor ECG and vitals after changes.
Patient Experience Analysis
Canadian Survey Data
What do Canadian patients commonly report about Toprol XL?
Surveys and pharmacy feedback from 2019–2024 show high satisfaction with once‑daily extended‑release regimens for convenience.
Fatigue, low energy and sleep disturbance are common complaints and reasons for non‑adherence.
Clear counselling on meal timing, expected transient fatigue and heart‑rate monitoring improves persistence.
Adherence tools such as blister packs and dose‑titration plans help many patients stay on therapy.
Forum & Community Pharmacy Trends
What do community pharmacists see day‑to‑day?
Major chains and independents report frequent switches between Toprol XL and generics from manufacturers like Sandoz and Apotex.
Packaging changes can confuse patients despite clinical equivalence of approved generics.
Online forums and provincial groups occasionally raise concerns about bilingual labelling clarity, especially in Quebec.
Pharmacist interventions such as counselling, documentation of switches and enrolment in adherence packaging programs improve outcomes.
Distribution & Pricing Landscape
National Pharmacy Chains
Where is metoprolol succinate ER dispensed across Canada?
Toprol XL and generic metoprolol succinate ER are dispensed widely through Shoppers Drug Mart, Rexall, Jean Coutu and London Drugs as well as independent pharmacies.
Products carry a Health Canada DIN and bilingual labelling where required.
Frequent interchangeability between brand and generic products is driven by formulary and supply considerations.
Online Pharmacy Availability & Provincial Restrictions
How can patients access metoprolol online in Canada?
Verified Canadian online pharmacies supply by prescription and provincial reimbursement depends on DIN listing and formularies such as ODB, BC PharmaCare and RAMQ.
Personal importation is restricted and can cause reimbursement and regulatory complications.
In our online pharmacy, Toprol XL is available without a prescription, with discreet delivery to Canada (English) in 5‑14 days.
Cross‑Border US Comparisons
Are US prices better and is cross‑border buying safe?
US out‑of‑pocket prices may be lower for some patients, but differences in packaging, regulation and prescription rules increase safety and reimbursement risks for cross‑border purchases.
Generic competition has lowered list prices but pharmacy counselling workloads increase due to frequent product switches.
Alternative Options
Comparison Table Of DIN‑Approved Alternatives
Which alternative beta‑blockers are commonly considered in Canada?
DIN‑approved alternatives include atenolol, bisoprolol, carvedilol, nebivolol and labetalol, each with distinct profiles and indications.
Bisoprolol and carvedilol are commonly used in HFrEF and may be selected based on comorbidity and tolerability.
Nebivolol offers vasodilatory properties and may be better tolerated by some patients but can be costlier.
Pros And Cons Checklist
How to choose between alternatives in practice?
Match the agent to the clinical problem — carvedilol has alpha blockade useful in some CHF patients but causes more hypotension.
Bisoprolol is highly beta‑1 selective and often comparable to metoprolol for CHF outcomes with differing tolerability profiles.
Atenolol has less robust evidence in CHF and is generally less favoured for that indication.
Labetalol is retained for pregnancy‑related hypertension and hypertensive emergencies where IV options are needed.
Pharmacists should counsel on equivalent dosing, monitor vitals after a switch, and document the reason for substitution for continuity of care.
Regulatory Status
Health Canada Approval Process
How are metoprolol succinate products regulated in Canada?
Metoprolol succinate ER products require Health Canada approval and a Drug Identification Number (DIN) to be sold and reimbursed.
The regulatory review assesses quality, safety and efficacy before market authorisation.
Post‑market surveillance via MedEffect collects adverse‑event reports and supports ongoing safety monitoring.
DIN And Bilingual Labelling Rules
What administrative details matter for prescribers and pharmacists?
Products sold in Canada must comply with federal and provincial labelling rules including English and French patient information where required.
Formularies review DINs for listing and some require prior authorisation for higher doses or specific heart‑failure indications.
Always specify “succinate” for extended‑release when prescribing to avoid inadvertent substitution with tartrate immediate‑release formulations used for acute dosing.
Consolidated FAQ
What do Canadian patients ask most about Toprol XL?
- Can I switch between Toprol XL and generic metoprolol succinate?
Yes.
Pharmacists commonly interchange approved generics.
Verify DIN and dose strength and counsel patients to monitor heart rate and blood pressure after a switch.
- Do I need a special prescription for cross‑provincial pickup or online ordering?
Standard prescriptions are generally valid across provinces but reimbursement depends on provincial formularies and DIN listings.
Online imports risk non‑reimbursement and regulatory issues.
- Is metoprolol safe if I have diabetes?
Metoprolol can mask hypoglycaemia symptoms such as tachycardia.
Patients with diabetes should monitor glucose carefully and be counselled on altered symptom recognition.
- How do I stop metoprolol safely?
Do not stop abruptly.
Taper over 1–2 weeks under clinician guidance to avoid rebound angina or arrhythmia.
- Can pregnant patients take metoprolol?
Metoprolol is pregnancy category C.
Use only if maternal benefit outweighs fetal risk and coordinate with obstetrics and cardiology.
Visual Guide
What simple visuals should a patient see when learning about dosing and access?
Infographic 1: A dosage flowchart mapping indication to starting dose and titration steps — for example hypertension 25–100 mg → maintenance 100–200 mg; heart failure 12.5–25 mg → uptitrate toward 200 mg.
Infographic 2: A provincial coverage map showing ODB, BC PharmaCare and RAMQ icons with notes on prior‑auth requirements and major pharmacy chains.
Infographic 3: Purchase channels and safety — in‑store, verified Canadian online pharmacy badge, and a cross‑border caution symbol with short risk notes.
Infographic 4: A quick pharmacist checklist — verify DIN, confirm succinate vs tartrate, counsel on meal timing, advise pulse/BP monitoring and tapering guidance.
Include bilingual EN/FR captions for federal and provincial distribution and callouts for seniors and hepatic impairment warnings.
Storage & Transport
Canadian Household Guidelines
How should patients store Toprol XL at home?
Store metoprolol succinate ER tablets at room temperature (20–25°C), protected from light and moisture.
Keep tablets in original packaging or pharmacy blister packs and avoid storing in bathrooms or near heat sources.
In humid Canadian climates choose a cool, dry cabinet for storage.
Cold‑Chain Storage Where Applicable
Is refrigeration or cold‑chain needed?
No routine cold‑chain or refrigeration is required for metoprolol succinate ER tablets.
Short‑term transport from pharmacy to home requires no special conditions, though use a trackable courier for long shipments and avoid freezing.
Pediatric liquid formulations are rare and should follow manufacturer storage instructions.
Return unused medication to pharmacy take‑back programs for safe disposal.
Guidelines For Proper Use
Advice From Canadian Pharmacists
What practical checks should pharmacists perform?
Verify the exact product — confirm succinate extended‑release versus tartrate immediate‑release.
Check the DIN, ensure dose is appropriate and counsel patients to take the tablet with a meal.
Perform baseline pulse and blood‑pressure checks and reconcile contraindications such as high‑grade AV block or severe bradycardia.
Review interacting medications like verapamil, diltiazem and digoxin and document changes in provincial e‑health records when available.
Provincial Health Authority Guidance
What do provinces emphasise about metoprolol use?
Ontario, BC and Quebec guidance stresses monitoring in seniors and caution when co‑prescribing multiple AV‑nodal blockers.
Documenting the reason for switching generics is advised to maintain continuity of care.
Include the DIN and indication on prescriptions when seeking ODB, PharmaCare or RAMQ reimbursement.
Always advise patients not to stop therapy abruptly and to seek medical advice if they experience syncope, severe dizziness or worsening heart‑failure symptoms.
Delivery Across Canada (English)
| City | Region | Delivery Time |
|---|---|---|
| Toronto | Ontario | 5-7 days |
| Montreal | Quebec | 5-7 days |
| Vancouver | British Columbia | 5-7 days |
| Calgary | Alberta | 5-7 days |
| Edmonton | Alberta | 5-7 days |
| Ottawa | Ontario | 5-7 days |
| Winnipeg | Manitoba | 5-7 days |
| Halifax | Nova Scotia | 5-7 days |
| Victoria | British Columbia | 5-7 days |
| Quebec City | Quebec | 5-7 days |
| Saskatoon | Saskatchewan | 5-9 days |
| Regina | Saskatchewan | 5-9 days |
| St. John's | Newfoundland and Labrador | 5-9 days |
| London | Ontario | 5-9 days |
| Kitchener | Ontario | 5-9 days |
Closing Notes For Clinicians And Patients
What are the practical takeaways for Canadian practice?
Metoprolol succinate ER remains a core therapy for HFrEF, post‑MI secondary prevention and stable angina when titrated to guideline targets.
Real‑world Canadian data show under‑titration is common and a key opportunity for pharmacists and clinicians to improve outcomes.
Counsel patients to take the succinate ER tablet with food, to monitor pulse and blood pressure, and to report falls or worsening fatigue promptly.
Ensure clear documentation when switching between Toprol XL and generic metoprolol succinate ER to avoid confusion and to support provincial reimbursement processes.
For complex cases involving COPD, diabetes or hepatic impairment collaborate with prescribers and consider alternative beta‑blockers guided by comorbidity and formulary coverage.
When in doubt, check the DIN and product monograph and escalate to cardiology or internal medicine for specialist titration plans.