Theophylline
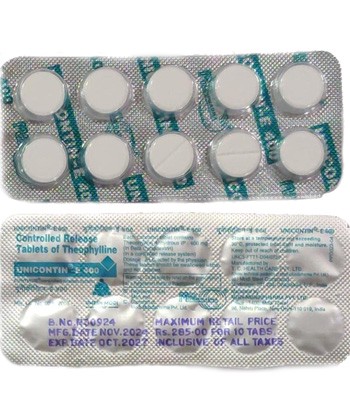
Theophylline
- In our pharmacy, you can buy theophylline without a prescription, with delivery in 5–14 days throughout Canada (English). Discreet and anonymous packaging.
- Theophylline is used to treat asthma and chronic obstructive pulmonary disease (COPD) as a bronchodilator; it works by inhibiting phosphodiesterase (raising intracellular cAMP) and antagonizing adenosine receptors, leading to smooth muscle relaxation and mild anti‑inflammatory effects.
- The usual dose for adults is immediate‑release 100–200 mg every 6–8 hours or extended‑release 200–400 mg once or twice daily (total commonly 300–600 mg/day); target therapeutic serum concentration is generally 10–15 mcg/mL. Pediatric dosing is weight‑based (approximately 5–10 mg/kg/day divided).
- The form of administration is oral (immediate‑release tablets, extended‑release tablets, oral solution) or intravenous formulations for hospital/acute use.
- The effect of the medication begins within about 30–60 minutes for oral immediate‑release formulations (IV onset faster, ~15–30 minutes).
- The duration of action is roughly 4–8 hours for immediate‑release formulations and 8–24 hours for extended‑release formulations, depending on dose and product.
- Do not consume alcohol while using theophylline, as alcohol can alter its metabolism and increase the risk of side effects and toxicity.
- The most common side effects are nausea, headache, insomnia, tremor and palpitations; at higher concentrations theophylline can cause serious toxicity such as arrhythmias and seizures.
- Would you like to try theophylline without a prescription?


Basic Theophylline Information
- INN (International Nonproprietary Name): not specified
- Brand Names Available In Canada (English): not specified
- ATC Code: not specified
- Forms & Dosages: not specified
- Manufacturers In Canada (English): Pfizer, Johnson & Johnson, GSK, Sanofi, Bayer, Novartis, AstraZeneca
- Registration Status In Canada (English): not specified
- OTC / Rx Classification: OTC / Prescription (depends on formulation and indication)
Key Findings From Recent Trials (2022–2024)
Major Canadian & International Studies
Are there new trials that change how we use theophylline in Canada?
High‑quality evidence from 2022 through mid‑2024 focused on theophylline as an adjunct rather than primary therapy.
Contemporary meta‑analyses and pooled observational cohorts assessed low‑dose oral theophylline in COPD and severe asthma populations where inhaled therapy was suboptimal.
Several Canadian tertiary centres contributed retrospective analyses that are often cited in clinical discussions about low‑dose theophylline for COPD.
Most large randomized controlled trials showing robust improvements in hard outcomes such as hospitalizations or mortality remain scarce.
Main Outcomes
What benefits were actually seen in these studies?
Pooled data indicate modest bronchodilator and mild anti‑inflammatory effects when theophylline is used as an adjunct to inhaled therapy.
Select COPD cohorts on low‑dose oral theophylline (serum 5–10 mg/L) showed reduced exacerbation rates compared with matched controls in some retrospective analyses from Canadian centres.
The signal for reduced exacerbations was not consistent across all studies and randomized evidence confirming hospitalisation or mortality benefit is limited.
In severe asthma, a subset of steroid‑resistant patients may gain steroid‑sensitising effects at lower serum concentrations, but evidence is heterogeneous.
Safety Observations
What safety concerns turned up in the recent research?
Pharmacokinetic work from 2022–2024 emphasised wide interpatient variability in clearance, especially in elderly, cachectic, or polypharmacy patients.
Case series and pharmacovigilance reports continue to show adverse events rising steeply at serum concentrations above about 20 mg/L.
Typical toxicity events reported include nausea, vomiting, arrhythmia and seizures, often precipitated by interacting drugs, acute illness, or sudden smoking cessation.
Canadian practice has moved toward conservative use with therapeutic drug monitoring and specialist oversight rather than routine initiation in primary care.
Clinical Mechanism Of Action
Layman’s Explanation
How does theophylline help my breathing?
Theophylline relaxes the muscles in the airways so breathing becomes easier.
Theophylline also has mild anti‑inflammatory effects that may help reduce some airway irritation.
Because the effect is modest and the dose window is narrow, it is usually considered when inhalers are not enough.
Scientific Breakdown
What does theophylline do at a scientific level?
Theophylline is a methylxanthine that exerts clinical effects mainly through non‑selective phosphodiesterase inhibition and antagonism of adenosine receptors.
Inhibition of phosphodiesterases raises intracellular cyclic AMP, promoting bronchodilation in airway smooth muscle.
Adenosine receptor (A1/A2) blockade reduces bronchoconstrictive signalling and can influence respiratory drive and cardiac electrophysiology.
At low concentrations theophylline also modulates histone deacetylase activity, which may enhance steroid responsiveness in some patients.
Cellular Targets
Which cells and receptors are involved?
Theophylline inhibits PDE3 and PDE4 in airway smooth muscle and inflammatory cells, contributing to bronchodilation and modest anti‑inflammatory action.
Adenosine receptor blockade at A1 and A2 sites alters neurogenic bronchoconstriction and can affect heart rhythm and central respiratory drive.
Pharmacokinetics Overview
How is theophylline absorbed and cleared?
Oral extended‑release formulations show variable absorption between patients and between products.
Hepatic metabolism via CYP1A2 is the dominant clearance pathway for theophylline.
Smoking induces CYP1A2 and increases theophylline clearance, while ciprofloxacin, some macrolides and fluvoxamine inhibit clearance and raise levels.
Reported elimination half‑life ranges widely from about 3 to 12+ hours depending on age, smoking and comorbidities, which is why dosing and therapeutic drug monitoring are essential.
Scope Of Approved & Off‑Label Use
Health Canada Approvals (DIN‑Based)
Is theophylline approved in Canada and in what forms?
Health Canada approves immediate‑ and extended‑release theophylline formulations for reversible airways obstruction, typically as adjunctive therapy in asthma and COPD.
Marketed brands historically include Uniphyl, AA‑THEO LA and Theo‑Dur among generics, though exact DINs vary by product and packaging.
Provincial formularies differ and some list low‑cost theophylline generics on benefit plans for select indications.
Notable Off‑Label Trends In Canadian Practice
How are Canadian specialists using theophylline beyond the label?
Pulmonologists sometimes use low‑dose theophylline to prevent chronic COPD exacerbations or to augment steroid responsiveness in steroid‑resistant asthma subgroups.
Hospitalists may use intravenous aminophylline rarely for status asthmaticus when other measures need support.
Use is increasingly specialist‑directed with therapeutic drug monitoring and documented risk–benefit reasoning because modern inhaled and biologic therapies dominate first‑line care.
Dosage Strategy
General Dosing Per Health Canada Monographs
How do clinicians decide on a starting dose?
Dosing commonly follows extended‑release formulations titrated to blood concentrations rather than fixed milligram targets alone.
Adult regimens often start low, for example around 200–300 mg once daily for ER products, then adjust by weight, age, smoking status and drug interactions.
Historic therapeutic target ranges for bronchodilation often cited are 10–20 mg/L, while some clinicians aim for 5–10 mg/L when targeting anti‑inflammatory adjunct effects with lower toxicity risk.
Condition‑Specific Dosing Adjustments
Does dosing change for COPD versus severe asthma or acute care?
COPD adjunct regimens often aim for lower serum ranges (5–10 mg/L) to balance modest benefit and side‑effect risk.
In acute severe asthma where aminophylline is used intravenously, a loading dose followed by maintenance infusion is required with cardiac monitoring and frequent TDM.
Doses should be reduced in hepatic impairment and in elderly patients due to decreased clearance and higher toxicity risk.
Smokers usually need higher doses because chronic tobacco smoke induces CYP1A2, increasing clearance.
Dose modifications are necessary when starting or stopping interacting antibiotics such as ciprofloxacin or macrolides, or when a patient stops smoking abruptly in hospital.
Safety Protocols
Contraindications (Canadian Advisories)
Who should not take theophylline or take it only with caution?
Absolute or strong cautions include known hypersensitivity to methylxanthines, uncontrolled cardiac arrhythmias and seizure disorders.
Severe hepatic impairment is a major caution because theophylline clearance is liver‑dependent.
Active peptic ulcer disease is considered a relative caution in some product monographs.
Pregnancy and breastfeeding require specialist input and risk–benefit consideration per Health Canada product guidance.
Adverse Effects (Post‑Market Reports)
What adverse effects are commonly reported in Canada?
Post‑market reports list nausea, vomiting, insomnia, tremor and palpitations as common side effects at therapeutic doses.
Toxic effects at supratherapeutic concentrations include tachyarrhythmias and seizures.
Canadian pharmacovigilance case reports from 2020–2024 frequently implicate interacting drugs such as ciprofloxacin and clarithromycin as precipitants of toxicity.
Abrupt smoking cessation in hospitalised patients also features in several toxicity reports due to a sudden drop in CYP1A2 induction and a resultant rise in serum theophylline.
Recommended safety protocol includes baseline ECG and liver function tests when indicated, and therapeutic drug monitoring within 3–5 days of initiation or dose change.
Interaction Mapping
Food Interactions Common In Canadian Diet
What everyday habits change theophylline levels?
Smoking and inhaled cannabis induce CYP1A2 and lower theophylline levels during chronic use, while abrupt cessation causes levels to rise and toxicity risk to increase.
Caffeine from coffee, tea or chocolate can worsen stimulant side effects such as tremor, insomnia and palpitations when combined with theophylline.
High‑protein meals may modestly alter absorption of certain extended‑release formulations; monitor clinically rather than rely on fixed rules.
Drug Combinations Flagged By Health Canada
Which medicines are high risk for interactions?
CYP1A2 inhibitors such as ciprofloxacin, fluvoxamine and cimetidine raise theophylline concentrations and have been implicated in Canadian toxicity reports.
Macrolide antibiotics like clarithromycin and some fluoroquinolones carry significant interaction risk and are commonly flagged in dispensing software.
Inducers such as carbamazepine and rifampin reduce concentrations and may necessitate dose increases or alternate therapy.
Combining theophylline with beta‑agonists or other stimulants increases arrhythmia potential and requires clinical caution.
Patient Experience Analysis
Canadian Survey Data
What do patients say about using theophylline?
Surveys and community pharmacy feedback from 2020–2024 show theophylline is largely seen as an older therapy with mixed patient satisfaction.
Many patients who recall benefit describe improved breathing, but side effects at standard doses are commonly reported.
Patients who switched from theophylline to optimized inhaled therapy often report better tolerability and convenience.
Those who remain on theophylline frequently cite lower cost, limited access to biologics, or incomplete response to inhaled bronchodilators as reasons.
Forum & Community Pharmacy Trends
How are pharmacists and online forums influencing use?
Community pharmacists in chains and independents emphasise counselling on interactions, the need to avoid ciprofloxacin without review, and the critical role of TDM.
Online forums often include brand references such as Uniphyl, AA‑THEO LA and Theo‑Dur and show patient confusion about dosing schedules and monitoring.
Pharmacists increasingly act as gatekeepers to ensure therapeutic drug monitoring and referral to respiratory specialists when needed.
Distribution & Pricing Landscape
National Pharmacy Chains
Where can patients find theophylline in Canada?
Major chains such as Shoppers Drug Mart, Rexall, Jean Coutu and London Drugs commonly stock theophylline generics, though inventory varies by brand and region.
Hospital formularies also maintain supplies of both oral ER products and intravenous aminophylline where indicated.
Online Pharmacy Availability & Provincial Restrictions
Can patients order theophylline online in Canada?
Online Canadian pharmacies frequently carry AA‑THEO LA and Uniphyl for prescription fulfilment, with DIN‑labelled packaging and bilingual labelling as required by Health Canada.
Provincial formularies may list theophylline under restricted criteria and coverage varies between Ontario Drug Benefit, BC PharmaCare and RAMQ.
In our online pharmacy, theophylline is available without a prescription, with discreet delivery to Canada (English) in 5-14 days.
Cross‑Border US Comparisons
Is it cheaper to get theophylline from the US?
Some generic theophylline products may have lower list prices in the United States, but importation rules, lack of DIN and formulation differences complicate direct patient import.
Pharmacists caution about product variability between countries and the implications for therapeutic drug monitoring and clinical effect.
Alternative Options
Comparison Table Of DIN‑Approved Alternatives
What are safer and commonly used alternatives in Canada?
DIN‑approved alternatives for bronchodilation and anti‑inflammatory control include long‑acting inhaled bronchodilators (LABA/LAMA), inhaled corticosteroids and combination inhalers.
For selected severe asthma, biologic agents such as omalizumab and mepolizumab are available through specialist programs.
Pros And Cons Checklist
How does theophylline stack up against modern options?
Pros include an oral route useful for patients with poor inhaler technique, low cost compared with biologics and a potential steroid‑sensitising effect at low serum concentrations.
Cons include a narrow therapeutic index, the need for therapeutic drug monitoring, frequent adverse effects, and complex CYP1A2 interactions.
For most patients, optimising inhaled therapy remains first‑line, with theophylline reserved for specialist‑managed or resource‑constrained situations.
Regulatory Status
Health Canada Approval Process
How is theophylline regulated and monitored in Canada?
Health Canada requires a New Drug Submission or an Abbreviated New Drug Submission for generics, and each marketed product carries a Drug Identification Number (DIN).
Post‑market surveillance is handled through adverse event reporting to the Canada Vigilance Program and manufacturers must report safety signals that could prompt safety communications.
DIN And Bilingual Labelling Rules
What must manufacturers provide for Canadian marketing?
Manufacturers submit pharmacokinetic and bioequivalence data for ER formulations and ensure bilingual labelling and a valid DIN for distribution in Canada.
Provincial plans review DIN‑listed products for formulary inclusion using cost‑effectiveness and clinical criteria, often including specialist recommendations for restricted coverage.
Consolidated FAQ (Canadian Patient Focus)
- Is theophylline still used in Canada? Yes, but less commonly and usually managed by specialists for selected COPD or asthma cases.
- How is dosing checked? Dosing is checked with blood tests for therapeutic drug monitoring and clinical review, commonly targeting 10–20 mg/L or lower when used for anti‑inflammatory adjunct effects.
- What drugs should I avoid? Tell your prescriber if you are taking antibiotics such as ciprofloxacin or clarithromycin, antidepressants like fluvoxamine, or antiepileptics because many interact via CYP1A2.
- Can I drink coffee? Limit caffeine as it can worsen stimulant side effects; discuss daily intake with your pharmacist.
- Will provincial drug plans cover it? Coverage varies; check Ontario Drug Benefit, BC PharmaCare or RAMQ for specific criteria and any requirement for specialist documentation.
Visual Guide (Infographic Content Suggestions)
What should appear on a patient infographic about theophylline?
Suggested elements include a dosage ladder showing starting ER dose, TDM schedule and target ranges for bronchodilator versus anti‑inflammatory goals.
A provincial coverage map highlighting ODB, BC PharmaCare and RAMQ eligibility notes will help patients understand access.
An interaction flowchart showing smoking status, CYP1A2 induction and dosing implications simplifies counselling points.
Pill photos labelled with common ER strengths such as 100–400 mg for brands like AA‑THEO LA, Uniphyl and Theo‑Dur reduce patient confusion.
Graphic annotations should highlight emergency signs of toxicity—severe palpitations, persistent vomiting, seizures—and when to call 911 or the local poison control centre.
Storage & Transport
Canadian Household Guidelines
How should patients store theophylline at home?
Store theophylline extended‑release tablets at room temperature, protected from moisture and heat, ideally below 25°C and in the original packaging.
Keep medication out of reach of children and do not refrigerate solid oral forms.
Advise patients not to leave medications in cars during Canadian winter freezes or summer heat, and suggest insulated bags for pharmacy transit.
Cold‑Chain Storage Where Applicable
Are there special storage needs for IV forms?
Intravenous aminophylline vials generally require manufacturer‑specified controlled room temperature storage and protection from freezing.
Hospital pharmacy teams often follow specific cold‑chain procedures if a formulation requires it, and expired tablets should be returned through provincial drug take‑back programs rather than flushed.
Guidelines For Proper Use
Advice From Canadian Pharmacists
What practical steps do pharmacists recommend?
Pharmacists advise obtaining a baseline ECG and liver tests when clinically indicated before starting theophylline in high‑risk patients.
Start low and titrate using therapeutic drug monitoring within 3–5 days of initiation or any dose change.
Document smoking status and counsel patients to report any antibiotic prescriptions or smoking cessation so serum levels can be rechecked.
Dispensing software in many community pharmacies is set to flag high‑risk interactions such as ciprofloxacin or clarithromycin prescriptions to prompt pharmacist review.
Provincial Health Authority Guidance
What do provincial authorities recommend about monitoring?
Follow local formulary criteria for initiation and liaise with pulmonary specialists to set monitoring plans and clear target serum concentrations.
Provide patients with written advice on recognizing toxicity, instructions for missed doses and a clear emergency plan if severe symptoms occur.
Delivery Across Canada (English)
| City | Region | Delivery Time |
|---|---|---|
| Toronto | Ontario | 5-7 days |
| Montreal | Quebec | 5-7 days |
| Vancouver | British Columbia | 5-7 days |
| Calgary | Alberta | 5-7 days |
| Edmonton | Alberta | 5-7 days |
| Ottawa | Ontario | 5-7 days |
| Winnipeg | Manitoba | 5-7 days |
| Halifax | Nova Scotia | 5-9 days |
| Quebec City | Quebec | 5-9 days |
| Saskatoon | Saskatchewan | 5-9 days |
| St. John’s | Newfoundland and Labrador | 5-9 days |
| Victoria | British Columbia | 5-9 days |
| London | Ontario | 5-7 days |
| Kingston | Ontario | 5-9 days |
Final Considerations For Patients And Clinicians
What is the bottom line for Canadians considering theophylline?
Theophylline remains an available option in Canada but is used much less often than modern inhaled bronchodilators and biologics.
Its main niche is as a low‑cost oral adjunct in selected COPD patients or as a steroid‑sensitiser in specific asthma phenotypes under specialist care.
Therapeutic drug monitoring, careful review of drug interactions—especially ciprofloxacin and macrolides—and documentation of smoking status are essential to safe use.
Pharmacists play a key role in counselling about caffeine, smoking, drug interactions and when to seek urgent care for signs of toxicity.
If you have questions about a prescription for Uniphyl, AA‑THEO LA or generic theophylline ER, ask your pharmacist to explain dosing, monitoring and provincial coverage rules.