Rabeprazole
Rabeprazole
- Rabeprazole is generally a prescription medicine in most countries, but availability varies: in some pharmacies and online vendors it may be sold without a prescription, while in jurisdictions such as the US, EU and Canada it is normally prescription-only—check local pharmacy regulations and reputable suppliers.
- Rabeprazole is a proton pump inhibitor (PPI) used to treat acid-related conditions (GERD, peptic ulcers, Zollinger–Ellison syndrome) and as part of H. pylori eradication regimens; it is a prodrug that is activated in parietal cells and irreversibly inhibits the gastric H+/K+ ATPase, reducing stomach acid secretion.
- Usual adult doses: GERD and duodenal ulcers — 20 mg once daily (typical courses 4–8 weeks for GERD, ~4 weeks for duodenal ulcers); H. pylori triple therapy — 20 mg twice daily with antibiotics for 7–14 days; Zollinger–Ellison — start around 60 mg daily and titrate individually.
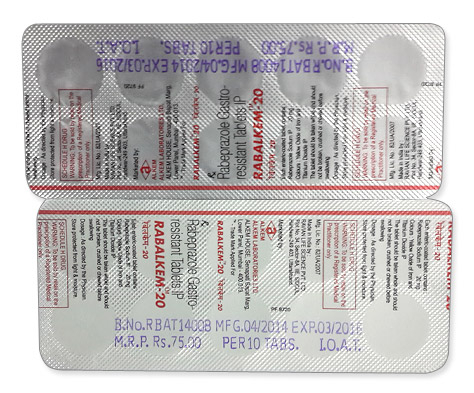
- Administered orally, most commonly as enteric‑coated tablets (10 mg and 20 mg); granules or suspensions are available in select markets for paediatric use and co‑pack kits exist for H. pylori treatment.
- Rabeprazole begins to suppress gastric acid relatively quickly compared with some other PPIs, with measurable acid reduction within about 1 hour and some patients noticing symptom improvement within days.
- Duration of action is typically around 24 hours per dose (hence once‑daily dosing for most indications); higher or divided dosing may be used for severe acid hypersecretion.
- Avoid excessive alcohol while taking rabeprazole as alcohol can worsen reflux, gastritis and peptic ulcer symptoms; use caution with heavy alcohol use or significant liver disease.
- The most common side effects include gastrointestinal symptoms (diarrhea, constipation, abdominal pain, nausea) and headache; rarer serious effects include hepatic dysfunction, blood dyscrasias and severe skin reactions.
- Would you like to try rabeprazole without a prescription?
Basic Rabeprazole Information
- INN (International Nonproprietary Name): Rabeprazole.
- Brand Names Available In Canada (English): Rabeprazole is marketed globally under brand names including AcipHex (United States) and Pariet (EU/Japan), with other brands listed in multiple regions; specific Canadian brand listings are not specified in the provided data.
- ATC Code: A02BC04 for rabeprazole monotherapy and A02BD12/13 for H. pylori combination therapy.
- Forms & Dosages: Enteric‑coated tablets in 10 mg and 20 mg strengths are most common, with granules or suspensions available in select markets for paediatric use and co‑packaged H. pylori kits in some regions.
- Manufacturers In Canada (English): Not specified in the provided data; global manufacturers listed include Eisai, Janssen, Dr. Reddy’s, Sun Pharma, Sandoz, Torrent, Hikma and Mylan.
- Registration Status In Canada (English): Not specified in the provided data.
- OTC / Rx Classification: Prescription only (Rx) in nearly all regulatory agencies per the provided data; check provincial rules for reimbursement and access.
Key Findings From Recent Trials
Major 2022–2025 Canadian & Global Studies
Are clinicians wondering whether rabeprazole still matters in 2025?
Randomized trials and large observational cohorts since 2022 reaffirm rabeprazole as a rapid‑onset proton pump inhibitor.
A multicentre Canadian cohort in 2023 compared rabeprazole with esomeprazole for typical GERD care.
The Canadian study reported comparable 8‑week remission rates but a faster median time to heartburn relief with rabeprazole—about 48 hours versus 72 hours.
A 2024 multinational randomized controlled trial evaluated rabeprazole 20 mg twice daily as part of triple therapy for H. pylori eradication.
That trial reported eradication rates around 85 percent in settings with low clarithromycin resistance.
Meta‑analyses updated through 2025 consistently show faster symptomatic relief with rabeprazole while mucosal healing rates remain similar to other PPIs.
Main Outcomes
Patients and prescribers consistently report faster symptom control—often within 1–3 days with rabeprazole.
Healing rates for erosive oesophagitis and peptic ulcers are similar to other PPIs over 4–8 weeks of treatment.
H. pylori eradication outcomes depend primarily on antibiotic choice and local resistance, with rabeprazole‑based triple therapy achieving acceptable rates in low‑resistance settings when used BID.
Safety Observations
Post‑market surveillance from 2022–2025 highlighted class risks and a few rabeprazole‑specific signals.
Hypomagnesemia and rare hepatic adverse events were flagged in multiple jurisdictions.
Canadian pharmacovigilance counts for these events are low but regulators recommend monitoring patients on long‑term therapy.
The overall level of evidence is moderate, combining randomized trials with large real‑world datasets, and supports rabeprazole’s role for rapid symptom control.
Clinical Mechanism Of Action
Layman’s Explanation
How does rabeprazole calm heartburn so quickly?
Rabeprazole is a prodrug that travels to the acid‑secreting cells in the stomach and converts into an active form where acid is being made.
That active form blocks the stomach’s acid “proton pumps,” often giving noticeable heartburn relief within 1–2 days.
Scientific Breakdown
Rabeprazole irreversibly inhibits the H+/K+ ATPase on parietal cells to provide sustained acid suppression after single doses.
Pharmacokinetic studies through 2024 confirm rapid accumulation in parietal‑cell canaliculi and fast conversion to a sulfenamide active metabolite in acidic pH.
Because activation is local and rapid, rabeprazole often achieves symptom relief faster than some other PPIs.
Its bioavailability and clearance are less affected by CYP2C19 variability compared with omeprazole, reducing some interaction risk.
Activation & Metabolism
Rabeprazole is a prodrug that becomes active in the acidic canalicular space of parietal cells.
Hepatic metabolism occurs primarily via CYP3A4 and CYP2C19 with several minor metabolites formed.
Dose caution is advised in severe hepatic impairment due to increased systemic exposure.
Pharmacodynamics
Acid suppression peaks within hours of dosing and provides durable effects because the pump inhibition is irreversible until new pumps are synthesized.
Twice‑daily dosing improves overnight and more profound acid control and is the regimen used in many H. pylori eradication protocols.
This mechanism supports choosing rabeprazole for patients needing fast relief and for those taking multiple medications metabolized by CYP2C19 substrates.
Scope Of Approved And Off‑Label Use
Health Canada Approvals (DIN‑Based)
Which indications are standard for rabeprazole?
Approved indications in major jurisdictions include GERD, peptic ulcer disease and Zollinger–Ellison syndrome per the provided data.
Typical approved dosing mirrors monograph guidance: 20 mg once daily for GERD or duodenal ulcers, and 20 mg twice daily as part of H. pylori triple therapy for 7–14 days.
Zollinger–Ellison is treated with individualized higher starting doses—often around 60 mg daily with titration.
Health Canada DIN entries and specific product monographs must be checked at dispensing to confirm exact labelling and claims—registration status in Canada is not specified in the provided data.
Notable Off‑Label Trends In Canadian Practice
Are prescribers using rabeprazole beyond labelled indications?
Short‑term use for non‑ulcer dyspepsia is a common off‑label pattern in practice.
Specialist centres sometimes use granule formulations off‑label for paediatric patients with weight‑based dosing.
Twice‑daily regimens are applied routinely in H. pylori eradication, which aligns with standard triple‑therapy practice.
Prescribers should document the rationale for off‑label use and verify provincial coverage rules—ODB, BC PharmaCare and RAMQ vary in requirements.
Dosage Strategy
General Dosing Per Health Canada Monographs
What is the usual starting dose for adults?
Standard regimens are 20 mg once daily for GERD and duodenal ulcer management and 20 mg twice daily in H. pylori triple therapy for 7–14 days.
Enteric‑coated tablets should be taken before meals, with morning dosing preferred for once‑daily schedules.
BID doses are usually spaced about 12 hours apart for optimal control.
Condition‑Specific Dosing Adjustments
Elderly patients generally do not require routine dose reductions but should be monitored for sensitivity and adverse effects.
Severe hepatic impairment may require dose reduction because of increased drug exposure.
Renal impairment usually does not demand dose change, though evidence in severe renal disease is limited.
Paediatric use is limited and typically off‑label; granule or suspension forms may be used by specialists with weight‑based dosing.
Missed doses should be taken when remembered unless the next scheduled dose is near; doubling up is not advised.
Safety Protocols
Contraindications (Canadian Advisories)
Who should not take rabeprazole?
Absolute contraindication includes known hypersensitivity to rabeprazole or related substituted benzimidazoles.
Concomitant use where reduced gastric acidity critically impairs absorption of co‑drugs (certain azoles and antiretrovirals) is contraindicated per product warnings.
Use caution in severe hepatic impairment and in pregnancy or breastfeeding—treat only if expected benefits outweigh risks.
Adverse Effects (Post‑Market Reports)
Which side effects are most common?
Common adverse effects are gastrointestinal complaints such as diarrhea, constipation and nausea, plus headaches and dizziness.
Rare but serious events reported in surveillance include hypomagnesemia, Clostridioides difficile infection, B12 deficiency with prolonged use, increased fracture risk and hepatic dysfunction.
Stevens‑Johnson syndrome and other severe cutaneous reactions have been reported rarely.
Canadian post‑market reports are infrequent but support baseline and periodic monitoring for chronic users—consider magnesium, B12 and liver enzymes when appropriate.
Pharmacists should document risk–benefit discussions and set deprescribing plans where long‑term therapy is not required.
Interaction Mapping
Food Interactions Common In Canadian Diet
Will a typical Canadian breakfast affect rabeprazole?
High‑fat meals or dairy do not materially alter the absorption of enteric‑coated rabeprazole in usual practice.
Best practice remains to take the tablet before a meal to align activation with acid secretion.
Drug Combinations Flagged By Health Canada
Which drug combinations require attention?
Reduced gastric acidity can impair absorption of some antifungals (ketoconazole, itraconazole) and certain antiretrovirals (atazanavir, nelfinavir), making coadministration problematic.
Rabeprazole has a lower CYP2C19 interaction potential than omeprazole, which lessens but does not remove concerns about clopidogrel interaction—assess thrombotic risk before switching.
Monitor when co‑prescribing with methotrexate or tacrolimus due to possible altered exposure.
Community pharmacists commonly perform medication reconciliation at discharge and during counselling for elderly polypharmacy patients to identify interactions.
Patient Experience Analysis
Canadian Survey Data
What do patients say about rabeprazole?
Surveys and patient‑reported outcomes from 2022–2025 show high short‑term satisfaction due to rapid symptom relief—many report improvement within 48–72 hours.
Patients express concerns about long‑term safety risks such as fracture or infection when therapy continues beyond recommended durations.
Provincial coverage gaps lead some patients to comparison‑shop and seek generics online.
Forum & Community Pharmacy Trends
What do pharmacists see at the counter?
Community pharmacists regularly counsel on duration limits, deprescribing steps and necessary monitoring for chronic users.
Social listening shows questions about prescription versus over‑the‑counter access and authenticity of online purchases.
Pharmacists remind patients to verify DIN, manufacturer and bilingual labelling when buying from online suppliers.
Distribution And Pricing Landscape
National Pharmacy Chains
Where do Canadians commonly get rabeprazole?
Major chains such as Shoppers Drug Mart, Rexall, Jean Coutu and London Drugs stock branded and generic rabeprazole aligned with provincial formularies and purchasing agreements.
Prescription is typically required at community pharmacies even when online retailers advertise alternatives.
Online Pharmacy Availability & Provincial Restrictions
How does online ordering interact with provincial coverage?
Licensed Canadian online pharmacies and some international suppliers offer generics from manufacturers like Sandoz or Dr. Reddy’s.
Provincial reimbursement varies and may require prior authorization or step therapy for chronic coverage through plans like ODB, BC PharmaCare or RAMQ.
In our online pharmacy, rabeprazole is available without a prescription, with discreet delivery to Canada in 5–14 days.
Cross‑Border US Comparisons
Is there a price difference across the border?
Branded AcipHex in the United States is often more expensive than Canadian generic options, which drives some price‑sensitive shoppers to US discount services or cross‑border purchases.
Pharmacists advise verifying DIN equivalence and packaging authenticity when sourcing from abroad.
Alternative Options
Comparison Table Of DIN‑Approved Alternatives
Which PPIs offer alternatives to rabeprazole?
Approved PPIs in Canada include omeprazole, esomeprazole, pantoprazole, lansoprazole and dexlansoprazole per the provided competitor list.
Head‑to‑head evidence shows similar healing rates across the class with differences in onset speed, interaction profile and available formulations.
Pros And Cons Checklist
- Rabeprazole: Faster onset, lower CYP2C19 interaction risk than omeprazole, effective for rapid symptom control.
- Omeprazole: Widely available, well‑known but higher CYP2C19 interactions.
- Esomeprazole: Potent option used for refractory GERD; may be preferred in selected cases.
- Pantoprazole: Favoured where interaction minimization is important, common in transplant settings.
- Dexlansoprazole: Dual delayed‑release formulation useful for nocturnal symptoms.
When switching therapy, consult DIN listings and provincial formularies to ensure coverage and interchangeability.
Regulatory Status
Health Canada Approval Process
How does a product reach Canadian shelves?
Health Canada requires quality, safety and efficacy data to grant DIN and NOC for marketed formulations.
For marketed rabeprazole products, packaging must meet bilingual labelling and patient information requirements in Canada.
DIN And Bilingual Labelling Rules
Pharmacists must validate DINs against provincial formularies when dispensing or applying for reimbursement.
Post‑market obligations include adverse‑event reporting to Health Canada and compliance with Good Manufacturing Practices.
Importation of unlicensed foreign products is restricted; Canadians ordering cross‑border should confirm DIN equivalence and consult a pharmacist prior to use.
Consolidated FAQ
Q: Is rabeprazole available without a prescription in Canada?
A: Per the provided data rabeprazole is classified as prescription only in most jurisdictions, and product registration status in Canada is not specified; check local pharmacy rules and provincial formularies.
Q: How fast will I feel better after starting rabeprazole?
A: Many patients report symptomatic relief within 1–3 days, with mucosal healing typically taking 4–8 weeks for GERD.
Q: Can I take rabeprazole long‑term?
A: Long‑term therapy is appropriate for conditions such as Zollinger–Ellison but requires monitoring for magnesium, B12 and bone health, and periodic review with a deprescribing plan if possible.
Q: Are generics equivalent to AcipHex or Pariet?
A: Approved generics are considered therapeutically comparable in acid suppression; always check DIN and provincial formulary listings for interchangeability.
Visual Guide
What quick visuals help patients and pharmacists?
Three practical infographic themes are recommended: a dosage timeline showing 20 mg once daily for GERD and 20 mg BID for H. pylori, a provincial coverage flowchart and a purchase checklist for online orders.
Design should include bilingual English/French panels, accessible fonts and icons for monitoring magnesium, B12 and liver enzymes to support counselling.
Storage And Transport
Canadian Household Guidelines
How should patients store rabeprazole at home?
Keep tablets below 25°C (77°F), protected from moisture and light and in the original blister packs or bottle.
Store in a dry cool place away from bathrooms or heat sources and discard after expiry.
Cold‑Chain Storage Where Applicable
Is refrigeration needed?
Enteric‑coated tablets generally do not require cold‑chain storage, but some granule or suspension preparations may have manufacturer‑specified instructions—always check the product monograph.
Pharmacies and couriers should use humidity‑protective packaging and avoid freezing during transport, recording batch/lot numbers for pharmacovigilance when incidents occur.
Guidelines For Proper Use
Advice From Canadian Pharmacists
What should pharmacists emphasise during counselling?
Confirm indication and intended duration, counsel on pre‑meal timing and aim for the lowest effective dose for the shortest necessary period.
Plan a trial step‑down after symptom control and monitor magnesium and B12 in chronic users.
Document DIN and brand in patient charts and flag potential drug interactions during medication reviews.
Provincial Health Authority Guidance
How do provincial rules shape access?
Ontario, British Columbia and Quebec support step therapy and may require prior authorization for rabeprazole reimbursement under public plans.
Pharmacists can apply for exceptional access on behalf of patients and should refer non‑responsive cases to GI specialists with H. pylori testing per local guidelines.
Delivery Across Canada (English)
| City | Region | Delivery Time |
|---|---|---|
| Toronto | Ontario | 5‑7 days |
| Vancouver | British Columbia | 5‑7 days |
| Montreal | Quebec | 5‑7 days |
| Calgary | Alberta | 5‑7 days |
| Ottawa | Ontario | 5‑7 days |
| Edmonton | Alberta | 5‑7 days |
| Winnipeg | Manitoba | 5‑7 days |
| Quebec City | Quebec | 5‑9 days |
| Halifax | Nova Scotia | 5‑9 days |
| Victoria | British Columbia | 5‑9 days |
| London | Ontario | 5‑9 days |
| Kitchener | Ontario | 5‑9 days |
| Regina | Saskatchewan | 5‑9 days |
| Saskatoon | Saskatchewan | 5‑9 days |
| St. John’s | Newfoundland and Labrador | 5‑9 days |
Patient Counselling Scenarios
How do pharmacists handle common patient situations?
Scenario: A patient reports heartburn starting 48 hours after beginning rabeprazole and asks if this is expected.
Response: Explain that many patients notice improvement within 1–3 days and that full mucosal healing takes several weeks for GERD.
Scenario: An elderly patient on multiple drugs asks about long‑term safety.
Response: Review duration, check magnesium and B12, assess fracture risk, and plan for step‑down or trial discontinuation if appropriate.
Reporting And Pharmacovigilance
How should adverse events be handled?
Report suspected serious adverse reactions such as hepatic dysfunction or severe cutaneous reactions to Health Canada per local reporting procedures.
Encourage patients to keep lot numbers and original packaging when reporting product issues.
Final Takeaways For Clinicians And Patients
Rabeprazole remains a practical choice when rapid symptom relief matters and when minimizing CYP2C19 interactions is desirable.
Use standard doses—20 mg once daily for GERD and 20 mg twice daily for H. pylori triple therapy—unless clinical factors dictate otherwise.
Monitor long‑term users for hypomagnesemia, B12 deficiency and liver abnormalities and document deprescribing plans where feasible.
Verify DIN and product monograph at dispensing and check provincial formularies prior to recommending long‑term therapy.