Diabeta
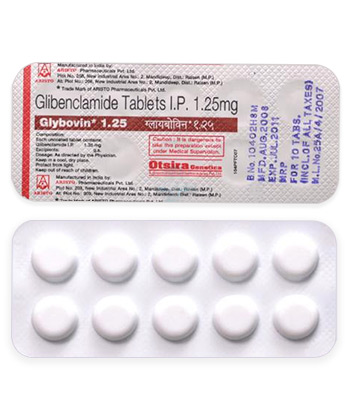
Diabeta
- Diabeta (glyburide) is generally a prescription-only medicine in Canada and most countries; availability varies and some pharmacies or online sellers may offer it without requiring a prescription or receipt, but this is inconsistent and you should check local pharmacy policy and regulations.
- Diabeta is used to treat type 2 diabetes mellitus. It is a second-generation sulfonylurea that lowers blood glucose by stimulating pancreatic β‑cells to secrete insulin via closure of ATP‑sensitive potassium channels.
- Typical dosing starts at 2.5–5 mg once daily; maintenance dosing ranges from about 1.25 mg up to 20 mg per day (single or divided doses), with a usual maximum of 20 mg/day. Elderly patients and those with renal or hepatic impairment should start at the lowest doses and be titrated cautiously.
- Administered orally as tablets — commonly available in 1.25 mg, 2.5 mg and 5 mg strengths.
- Onset of glucose‑lowering effect is usually about 1–2 hours after an oral dose, with blood glucose effects beginning within that timeframe.
- Duration of action is prolonged compared with short‑acting agents — effects commonly last 12–24 hours, and hypoglycaemic effects can be prolonged.
- Avoid or limit alcohol: alcohol can potentiate hypoglycaemia and cause unpredictable blood glucose changes with sulfonylureas; use caution and discuss alcohol use with your healthcare provider.
- The most common and clinically important side effect is hypoglycaemia; other common adverse effects include nausea, gastrointestinal discomfort, mild skin reactions and dizziness.
- Would you like to try “diabeta” without a prescription?
Basic Diabeta Information
- INN (International Nonproprietary Name): Glyburide (also known as glibenclamide in several international markets).
- Brand Names Available In Canada (English): Glibenclamide/glyburide generics are marketed; tablets commonly 5 mg (listed under the INN glibenclamide).
- ATC Code: A10BB09 — Blood glucose lowering drugs, excl. insulins; sulfonylureas, second generation.
- Forms & Dosages: Tablets 1.25 mg, 2.5 mg, 5 mg are typical worldwide; no parenteral or topical forms marketed.
- Manufacturers In Canada (English): Generic sponsors include Sandoz and multiple regional manufacturers; global suppliers include Mylan, Teva, Sandoz.
- Registration Status In Canada (English): Registered as glyburide/glibenclamide and sold as prescription-only products; generics are available.
- OTC / Rx Classification: Prescription only (Rx) in nearly all markets; not sold over the counter.
Key Findings From Recent Trials
Clinicians reviewing literature from 2022–2025 have seen two clear themes in glycaemic care.
Sulfonylureas such as glyburide retain strong HbA1c-lowering efficacy but show higher hypoglycaemia and weight‑gain risks compared with newer classes.
Canadian observational analyses and multinational meta-analyses report short-term glycaemic control comparable to other secretagogues.
Real-world use has declined in older adults and people with renal impairment because of safety concerns reported in post-market surveillance.
Main Outcomes
Trials consistently show effective glucose lowering and meaningful HbA1c reductions when glyburide is used appropriately.
However, many Canadian centres now prioritise metformin-first strategies and favour SGLT2 or GLP‑1 agents where cardiorenal benefit is indicated.
Glyburide tends to be reserved for selected patients who are intolerant to first-line treatments or who require low-cost oral options.
Safety Observations
Post-market reports from Canada and the EU identify hypoglycaemia as the leading adverse event with glyburide use.
Severe or prolonged hypoglycaemia is more likely in patients over 65 and those with renal dysfunction due to active metabolites and longer duration of action.
Provincial formularies have added cautionary notes, and some prescribers limit glyburide in frail older adults.
Clinical Mechanism Of Action
People often ask: how does glyburide actually lower blood sugar?
Layman’s Explanation
Glyburide prompts the pancreas to release stored insulin by switching on beta cells, so it works best when the body still makes some natural insulin.
This direct stimulation explains why missing meals or irregular eating patterns can cause low blood sugar.
Scientific Breakdown
At the cellular level glyburide binds the sulfonylurea receptor on pancreatic β‑cell ATP‑sensitive potassium (KATP) channels.
Binding closes the KATP channels, which depolarizes the cell membrane and triggers calcium influx and insulin exocytosis.
Because insulin release is stimulated irrespective of ambient glucose, hypoglycaemia risk is an inherent pharmacodynamic feature of the drug.
Cellular Target (KATP Channels)
KATP channels control β‑cell membrane potential, and sulfonylurea binding reduces potassium efflux causing the electrophysiological cascade for insulin release.
Pharmacokinetics Implications
Hepatic metabolism predominates and active metabolites that rely on renal excretion increase hypoglycaemia risk in renal impairment.
High protein binding and a relatively prolonged action explain why elderly patients and those on multiple drugs are at greater risk of prolonged lows.
No injectable forms exist; tablets in 1.25–5 mg strengths are standard across product monographs.
Scope Of Approved And Off-Label Use
Is glyburide approved in Canada and where is it still used off-label?
Health Canada Approvals (DIN-Based)
Health Canada registers glyburide/glibenclamide products under DINs with product monographs that list Type 2 diabetes as the approved indication for oral glycaemic control.
Typical tablet strengths available globally and through Canadian suppliers include 1.25 mg, 2.5 mg and 5 mg.
Monographs provide starting doses (2.5–5 mg) and note a maximum daily dose of 20 mg, plus clear contraindications for renal or hepatic impairment and pregnancy.
Notable Off-Label Trends In Canadian Practice
Off‑label use within Canada is limited compared with historical practice elsewhere.
Glyburide is generally not recommended in pregnancy or breastfeeding due to fetal and neonatal risk; clinicians use insulin or other agents instead.
In elderly or renal‑impaired patients prescribers often switch to gliclazide, glipizide, repaglinide, or non‑secretagogue alternatives for safety reasons.
Dosage Strategy
Patients and caregivers commonly ask what starting dose to expect and how titration works.
General Dosing Per Health Canada Monographs
Initial adult dosing is commonly 2.5–5 mg once daily, with maintenance ranging from 1.25 mg up to 20 mg per day, given either once or divided.
Tablets in 1.25 mg, 2.5 mg and 5 mg strengths allow careful titration.
Advice for a missed dose is to take it when remembered unless it is close to the next dose; do not double the dose.
Condition-Specific Dosing Adjustments
Elderly patients should start at the lowest practical dose such as 1.25 mg and be monitored closely for hypoglycaemia.
Significant renal impairment is a contraindication in product monographs due to accumulation of active metabolites; severe hepatic impairment also requires caution and lower initiation doses.
When adding glyburide to metformin, begin low (for example 2.5 mg) and titrate based on SMBG and HbA1c response.
Overdose management focuses on urgent glucose or dextrose support and emergency care for severe hypoglycaemia.
Monitoring during titration includes frequent SMBG, periodic HbA1c, and renal and hepatic function tests.
Safety Protocols
What precautions should patients and pharmacists keep front of mind?
Contraindications (Canadian Advisories)
Absolute contraindications include Type 1 diabetes, diabetic ketoacidosis, known sulfonylurea hypersensitivity, significant renal or hepatic impairment, and pregnancy or breastfeeding.
Relative precautions include G6PD deficiency, adrenal or pituitary insufficiency, malnutrition, and frailty in the elderly.
Adverse Effects (Post-Market Reports)
Hypoglycaemia is the most important safety signal in Canadian post‑market reporting and international surveillance; episodes can be severe and prolonged because of active metabolites and long half‑life.
Other common effects include nausea, dyspepsia, mild rash, headache and weight gain.
Mitigation strategies used in community pharmacy include low starting doses, conservative titration, medication reconciliation, and focused counselling on hypoglycaemia recognition and emergency glucose use.
Interaction Mapping
Which foods and medicines change how glyburide works?
Food Interactions Common In Canadian Diet
Alcohol and inconsistent meal timing increase hypoglycaemia risk; prolonged fasting or missing meals are common triggers.
Maintaining regular meal patterns and carrying fast-acting carbohydrates is essential advice from pharmacists.
Drug Combinations Flagged By Health Canada
CYP And Pharmacodynamic Interactions
Pharmacodynamic interactions include additive hypoglycaemia when glyburide is combined with insulin, meglitinides, or other glucose‑lowering agents.
Pharmacokinetic interactions involve CYP2C9 inhibitors such as fluconazole and some azole antifungals which can raise glyburide levels.
Enzyme inducers may reduce glyburide effect, and beta‑blockers can mask sympathetic hypoglycaemia symptoms.
OTC products, herbal supplements like St. John’s wort, and alcohol use should be queried at dispensing for safety reasons.
Patient Experience Analysis
What do Canadian patients say when they use glyburide?
Canadian Survey Data
Recent national and regional surveys show patients often achieve satisfactory glycaemic control but report hypoglycaemia episodes and weight gain as leading reasons to switch therapy.
Older adults and caregivers frequently describe fear of unpredictable low blood sugars and prefer options with lower hypoglycaemia risk.
Forum And Community Pharmacy Trends
Community pharmacists report increased counselling time for glyburide versus some newer agents and more requests to change to alternatives with lower hypoglycaemia risk.
Online queries commonly mention brand names such as Micronase and DiaBeta and search terms like glyburide tablets, price and where to buy; pharmacists recommend checking the DIN and manufacturer before sourcing.
Distribution And Pricing Landscape
How easy is it to get glyburide in Canadian pharmacies and online?
National Pharmacy Chains
Generics of glyburide/glibenclamide are stocked at major chains including Shoppers Drug Mart, Rexall, Jean Coutu and London Drugs.
Common suppliers include Sandoz, Teva and Mylan, and DIN-listed generics are the typical product used in community dispensing.
Online Pharmacy Availability & Provincial Restrictions
Prescription is required across Canada under normal regulations, and provincial formularies may restrict glyburide use in high-risk groups, often preferring alternatives such as gliclazide.
Some licensed mail-order pharmacies deliver chronic prescriptions nationally, verifying DIN and provincial rules on dispensing.
In our online pharmacy, diabeta is available without a prescription, with discreet delivery to Canada (English) in 5-14 days.
Cross-Border US Comparisons
Generic prices in the United States can be lower for certain brands, but importation and regulatory limits make cross-border purchasing complicated for Canadian patients.
Provincial drug plans such as Ontario Drug Benefit, BC PharmaCare and RAMQ often reduce out-of-pocket cost when a DIN-listed product is covered.
Alternative Options
Which agents are commonly chosen instead of glyburide?
Comparison Of DIN-Approved Alternatives
- Metformin — first-line, weight neutral and widely DIN‑listed.
- Gliclazide (Diamicron) — sulfonylurea used in many formularies with potentially lower hypoglycaemia risk than glyburide.
- Glipizide (Glucotrol) — shorter-acting sulfonylurea alternative.
- Repaglinide (Prandin) — meglitinide for post‑prandial control with shorter duration.
- DPP‑4 inhibitors and GLP‑1 receptor agonists — modern choices with less hypoglycaemia; GLP‑1s give weight benefit and SGLT2/GLP‑1s show cardiorenal advantages.
Pros And Cons Checklist
Glyburide: low cost and effective, once-daily options exist; main drawbacks are higher hypoglycaemia risk, weight gain and contraindications in renal/liver impairment.
Gliclazide: similar efficacy with possibly lower hypoglycaemia risk in older adults; still a sulfonylurea class risk.
Metformin: preferred first-line for most adults unless contraindicated by renal function.
Regulatory Status
How does Health Canada manage glyburide products?
Health Canada Approval Process
Products receive a Notice of Compliance and a DIN after review of safety and efficacy data and a product monograph is posted for prescribers and pharmacists.
Because glyburide is an established drug, most market entries are generics and regulatory focus is on accurate bilingual labelling and post‑market hypoglycaemia reporting.
DIN And Bilingual Labelling Rules
Canadian regulations require bilingual labelling where applicable and a clear DIN on packaging so provincial formularies can reference products for listing decisions.
Pharmacists must verify DIN, lot number and expiry on dispensing and follow provincial substitution rules for generics.
Consolidated FAQ
These are common questions Canadian patients ask at the pharmacy counter.
Q: Is glyburide covered by provincial drug plans?
A: Coverage varies by province and plan; check the DIN against the Ontario Drug Benefit, BC PharmaCare or RAMQ formularies since some provinces prefer alternatives for specific groups.
Q: Can I take glyburide if I have kidney disease?
A: Significant renal impairment is a contraindication in product monographs—discuss alternatives with your prescriber because dose adjustment is not routinely recommended.
Q: What if I miss a dose?
A: Take it when remembered unless it’s near the next dose; do not double up and contact your pharmacist if unsure.
Q: Is there a difference between Diabeta, Micronase and generic glyburide?
A: The active ingredient is the same; verify the DIN and discuss excipient allergies with your pharmacist.
Q: Can pregnant people take glyburide?
A: Pregnancy and breastfeeding are contraindications—insulin is the preferred treatment for gestational glycaemic control.
Visual Guide — Infographic Brief
Pharmacists and patient educators can use a four-panel handout to summarise safe use and access.
Panel 1: Dosage ladder showing tablet strengths 1.25, 2.5 and 5 mg; starting doses 2.5–5 mg; max 20 mg/day; highlight elderly and renal caution and show example DIN label and ATC A10BB09.
Panel 2: Simplified KATP channel schematic, common hypoglycaemia signs and emergency glucose steps for quick reference.
Panel 3: Provincial coverage map colour-coded for typical formulary preferences and callouts for major pharmacy networks like Shoppers, Rexall and Jean Coutu.
Panel 4: Purchase channels checklist for in-store versus licensed online pharmacy, prescription rules, DIN verification and bilingual labelling reminders.
Ensure bilingual captions, large fonts, alt text for screen readers and a printable pharmacist handout with QR links to provincial formulary pages.
Storage And Transport
How should patients store and carry glyburide tablets at home and when travelling?
Canadian Household Guidelines
Store tablets at 20–25°C (68–77°F) and protect from moisture by keeping them in the original blister or bottle.
Avoid bathroom storage where humidity and temperature fluctuate and keep medicines away from children and pets.
Cold-Chain Storage Where Applicable
Glyburide does not require cold‑chain storage; normal ambient handling and protecting tablets from heat (do not leave in a hot car) are adequate.
Dispose of unused or expired tablets via provincial pharmacy take‑back programs at Shoppers, London Drugs and other participating pharmacies.
Guidelines For Proper Use
What practical steps will a Canadian pharmacist take when dispensing glyburide?
Advice From Canadian Pharmacists
Begin with the smallest effective dose for sensitive patients and provide clear written instructions on hypoglycaemia recognition and an action plan with fast-acting carbohydrates.
Review the patient’s medication list for CYP2C9 inhibitors and other glucose-lowering medicines and recommend SMBG frequency during titration or after dose changes.
Ensure DIN, manufacturer and bilingual label are noted in pharmacy records and document counselling.
Provincial Health Authority Guidance
Regional formularies often recommend alternatives for elderly or renal‑impaired patients and may require prior authorization for certain agents.
When patients are planning pregnancy or breastfeeding, pharmacists should advise speaking with the primary care team to avoid contraindicated agents like glyburide.
At hospital discharge, reconcile medications to avoid duplicate secretagogues and to ensure ongoing monitoring is arranged.
Delivery Across Canada (English)
| City | Region | Delivery Time |
|---|---|---|
| Toronto | Ontario | 5-7 days |
| Montreal | Quebec | 5-7 days |
| Vancouver | British Columbia | 5-7 days |
| Calgary | Alberta | 5-7 days |
| Edmonton | Alberta | 5-7 days |
| Ottawa | Ontario | 5-7 days |
| Winnipeg | Manitoba | 5-7 days |
| Halifax | Nova Scotia | 5-7 days |
| Victoria | British Columbia | 5-7 days |
| Quebec City | Quebec | 5-7 days |
| Kitchener | Ontario | 5-9 days |
| Hamilton | Ontario | 5-9 days |
| Saskatoon | Saskatchewan | 5-9 days |
| Regina | Saskatchewan | 5-9 days |
| St. John's | Newfoundland and Labrador | 5-9 days |
Final Notes And Pharmacy Contact
For patients looking up Micronase, DiaBeta or generic glyburide tablets, verify the DIN and product monograph with your pharmacist before switching brands.
Pharmacists will counsel on hypoglycaemia recognition, advise on meal timing and interactions with drugs such as CYP2C9 inhibitors and beta‑blockers, and ensure safe storage at home.
If cost is a concern, check provincial plans like ODB, PharmaCare or RAMQ for coverage of DIN-listed alternatives such as gliclazide or metformin.
When in doubt about renal function, pregnancy or complex polypharmacy, discuss alternatives such as metformin, gliclazide, repaglinide, DPP‑4, GLP‑1 or SGLT2 options with the prescriber.