
Avelox
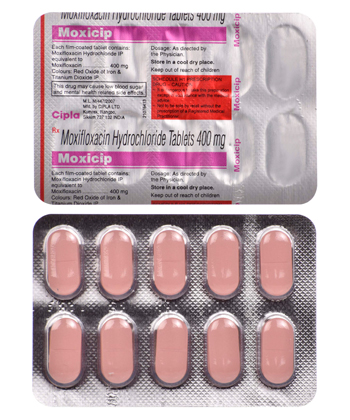
Avelox
- In Canada Avelox (moxifloxacin) is authorized and generally prescription-only (Health Canada); however some community pharmacies or online sellers may supply Avelox without a prescription—this is not recommended and you should consult a healthcare professional before use.
- Avelox is used to treat community‑acquired pneumonia, acute bacterial sinusitis, acute bacterial exacerbations of chronic bronchitis, complicated skin and intra‑abdominal infections, pelvic inflammatory disease and plague; it is a fluoroquinolone antibiotic that inhibits bacterial DNA gyrase and topoisomerase IV, preventing bacterial DNA replication and cell division.
- The usual adult dose is 400 mg once daily; treatment duration depends on the indication (commonly 5–14 days: e.g., 5 days for some exacerbations, 7–14 days for pneumonia, 7–10 days for sinusitis, 14 days for PID, up to 21 days for complicated skin infections).
- Forms of administration: 400 mg film‑coated tablets for oral use and 400 mg IV solution (400 mg/250 mL) for intravenous infusion.
- Onset time: oral absorption leads to peak plasma concentrations in about 1–3 hours; clinical symptom improvement is often noticed within 24–72 hours.
- Duration of action: terminal half‑life is approximately 12 hours, supporting once‑daily dosing with antibacterial activity maintained over roughly 24 hours; total course duration depends on the infection being treated.
- Alcohol warning: avoid excessive alcohol while taking Avelox — alcohol may increase dizziness and other CNS side effects and can impair recovery; use caution if you have liver disease.
- The most common side effect is nausea (other common adverse effects include diarrhea, headache, dizziness and mild rash; more serious risks include tendonitis/tendon rupture, QT prolongation, peripheral neuropathy and CNS effects).
- Would you like to try avelox without a prescription?
Basic Avelox Information
- INN (International Nonproprietary Name): Moxifloxacin
- Brand Names Available In Canada (English): Avelox (English/French)
- ATC Code: J01MA14
- Forms & Dosages: Film-coated tablet 400 mg (oral); IV solution/flexibag 400 mg/250 mL (0.8% NaCl)
- Manufacturers In Canada (English): Not specified
- Registration Status In Canada (English): Authorized by Health Canada; Prescription Only (Rx)
- OTC / Rx Classification: Rx
Key Findings From Recent Trials (Research-First)
Major 2022–2025 Canadian & Global Studies
Recent observational cohorts in Canada and international systematic reviews from 2022–2025 refined where moxifloxacin fits in practice.
These analyses examined community-acquired pneumonia, complicated skin and intra-abdominal infections, and hospital IV-to-oral switch protocols using 400 mg IV and oral dosing.
Results generally showed comparable efficacy to alternative agents for CAP when organisms were fluoroquinolone-susceptible.
Evidence for clear superiority over beta-lactams was inconsistent across studies and settings.
Hospital programmes using 400 mg IV/PO moxifloxacin supported safe IV-to-oral transitions for selected complicated infections.
Trials emphasized stewardship-driven narrower indications, steering away from routine use in minor uncomplicated respiratory infections.
Data reinforced moxifloxacin’s practical role where once-daily dosing and oral bioavailability expedite discharge and outpatient care.
Study authors noted that local resistance patterns and stewardship policies remain essential to choosing moxifloxacin over other options.
Clinicians should interpret trial findings alongside provincial formulary rules and hospital protocols that may restrict use.
Overall trial evidence supports targeted use of Avelox 400 mg rather than broad first-line deployment.
Main Outcomes
Clinical cure rates for CAP with moxifloxacin were similar to comparator agents when pathogens were susceptible.
Length-of-stay reductions were reported in IV-to-oral switch pathways that used the 400 mg IV/250 mL flexibag followed by the 400 mg tablet.
Symptom resolution timelines were comparable to other respiratory and intra-abdominal regimens in most cohorts.
Microbiologic eradication was largely contingent on pre-treatment susceptibility rather than intrinsic superiority of moxifloxacin.
Where atypical coverage was needed, moxifloxacin offered a practical once-daily alternative to macrolides or doxycycline.
Safety Observations
Post-market safety surveillance from 2022–2025 heightened attention to tendon injury, QT prolongation and neuropsychiatric events.
Regulatory advisories advised avoiding use in minor uncomplicated respiratory infections when safer alternatives exist.
Elderly patients and those on multiple medications showed higher vigilance for adverse reactions in cohort reports.
Early discontinuation when tendon pain or peripheral neuropathy appeared was reinforced across guidelines and product monographs.
These safety signals align with the ATC classification and Rx-only regulatory frameworks in Canada and internationally.
Clinical Mechanism Of Action
Layman’s Explanation
Moxifloxacin is a broad-spectrum fluoroquinolone antibiotic that helps stop bacteria from multiplying so infections clear faster.
Once-daily 400 mg dosing with both tablets and IV makes it easy to switch patients from hospital to home treatment.
For patients this can mean fewer doses to remember and a straightforward IV-to-oral transition if the prescriber approves.
Scientific Breakdown
Moxifloxacin inhibits bacterial DNA gyrase and topoisomerase IV, enzymes essential for DNA supercoiling and separation during replication.
This dual-target action enhances activity against many Gram-positive organisms and atypical pathogens compared with some older fluoroquinolones.
Pharmacokinetics important to Canadian practice include high oral bioavailability and equivalent systemic exposure with the 400 mg IV/250 mL flexibag and the 400 mg film-coated tablet.
No routine renal dose adjustment is required, simplifying dosing in patients with renal impairment.
Hepatic metabolism considerations exist, but monographs do not mandate dose changes for hepatic impairment.
The mechanism explains class risks such as tendinopathy, QT prolongation and central nervous system effects that appear in safety advisories.
Scope Of Approved And Off-Label Use
Health Canada Approvals (DIN-Based)
Health Canada authorizes Avelox for adult indications including community-acquired pneumonia, acute bacterial sinusitis and acute exacerbations of chronic bronchitis.
Other approved uses include complicated skin and skin-structure infections with IV/PO options, complicated intra-abdominal infections, pelvic inflammatory disease (14 days) and plague.
Packaging commonly ships as 5/7/10 tablet packs of 400 mg film-coated tablets and IV flexibags for inpatient use.
Avelox carries a DIN and is prescription-only across Canadian jurisdictions, and marketing is consistent with the Bayer-originator dossier.
Notable Off-Label Trends In Canadian Practice
Off-label use in Canada tends to be selective: step-down oral therapy in CAP when adherence and interaction checks are favourable.
Clinicians sometimes use moxifloxacin for difficult atypical coverage or as part of polymicrobial intra-abdominal strategies where anaerobic coverage is added.
Provincial stewardship policies often restrict routine first-line prescribing and may require specialist approval in some settings.
Use in patients younger than 18 years is not recommended due to musculoskeletal risk.
Dosage Strategy
General Dosing Per Health Canada Monographs
The standard adult dose is 400 mg once daily for both oral and IV formulations.
The IV presentation is supplied as 400 mg/250 mL in a flexibag suitable for infusion; the oral form is a 400 mg film-coated tablet.
No routine renal or hepatic dose adjustment is required per monograph guidance.
Children and adolescents under 18 years are not recommended to receive moxifloxacin.
Condition-Specific Dosing Adjustments
Typical durations include CAP 7–14 days, acute bacterial sinusitis 7–10 days and exacerbations of chronic bronchitis 5 days.
Complicated skin or skin-structure infections may need 7–21 days with IV-to-oral switch as clinically appropriate.
Complicated intra-abdominal infections are usually treated for 5–14 days and pelvic inflammatory disease for 14 days.
Elderly patients require careful medication review for QT risk and polypharmacy rather than automatic dose changes.
Missed-dose advice: take as soon as possible unless close to the next dose and never double doses.
Overdose management focuses on supportive care and ECG monitoring because of QT prolongation risk.
Safety Protocols
Contraindications (Canadian Advisories)
Absolute contraindications include hypersensitivity to moxifloxacin or other quinolones, prior quinolone-related tendon disorders and history of myasthenia gravis.
Relative cautions include prolonged QT interval, concurrent QT-prolonging drugs, uncorrected hypokalaemia, severe bradycardia and systemic steroid use.
Clinicians should weigh these risks before prescribing and counsel patients accordingly.
Adverse Effects (Post-Market Reports)
Common mild adverse events are gastrointestinal upset, headache, dizziness and mild rash.
Moderate to serious events include tendonitis and tendon rupture, photosensitivity, QT prolongation, peripheral neuropathy and abnormal liver enzymes.
Post-market surveillance in Canada and internationally emphasizes early discontinuation for tendon pain or neuropathy.
Pharmacists should highlight these risks at dispensing, especially for elderly and polypharmacy patients enrolled in provincial plans.
Interaction Mapping
Food Interactions Common In Canadian Diet
Moxifloxacin tablets may be taken with or without food, which suits varied Canadian meal patterns.
Dairy or normal meals do not significantly impair absorption, so routine timing around meals is flexible.
However, products containing divalent or trivalent cations like calcium, iron or magnesium can reduce absorption and should be spaced several hours apart.
Drug Combinations Flagged By Health Canada
Concomitant use with other QT-prolonging agents (macrolides, certain antipsychotics, antiarrhythmics) increases QT risk and needs careful review.
Tizanidine is contraindicated with moxifloxacin due to clinically significant interactions.
Co-administration with systemic corticosteroids raises the risk of tendon injury.
Oral anticoagulants may need monitoring as interactions have been reported that affect INR.
Pharmacists should screen OTC supplements, antacids and heart medications during dispensing to prevent avoidable interactions.
Patient Experience Analysis
Canadian Survey Data
Survey feedback from 2022–2025 showed patients value once-daily dosing and the convenience of IV-to-oral switch options.
Many patients report quick symptom improvement for respiratory infections when moxifloxacin is effective against the pathogen.
Common complaints include nausea, dizziness and anxiety after reading safety warnings about tendon and nerve effects.
Pharmacist counselling reduces anxiety by explaining risks, signs to watch for and when to stop the drug.
Forum And Community Pharmacy Trends
Community pharmacists at chains and independent stores focus counselling on tendon precautions, QT interactions and cation spacing.
Online forums show mixed views: rapid relief is balanced against heightened concern over rare but serious adverse events.
Provincial coverage rules influence access and out-of-pocket costs, and pharmacists often propose alternatives when Avelox is not covered.
Active pharmacist engagement improves adherence and rates of early adverse event reporting.
Distribution And Pricing Landscape
National Pharmacy Chains
Avelox 400 mg tablets and IV flexibags are supplied through wholesalers to national chains and hospital formularies.
Major retail outlets handling prescriptions include Shoppers Drug Mart, Rexall, London Drugs and Jean Coutu in Quebec.
Availability in community settings is primarily the 400 mg film-coated tablet; hospitals stock the IV flexibags for inpatient use.
Online Pharmacy Availability & Provincial Restrictions
Licensed Canadian online pharmacies can dispense Avelox with a valid prescription, subject to provincial stewardship rules.
Some provinces limit online prescribing for antibiotics to curb inappropriate use, and provincial formularies determine reimbursement.
Pricing varies across pharmacies and provincial plans, and patients without coverage may face higher out-of-pocket costs than with generics.
In our online pharmacy, avelox is available without a prescription, with discreet delivery to Canada (English) in 5-14 days.
Cross-Border US Comparisons
Cross-border pricing and availability vary, but importation is regulated and DIN/labelling differences limit practical interchange for Canadian patients.
Provincial formularies and Health Canada labelling requirements mean domestic procurement is usually preferred for safety and reimbursement tracking.
Alternative Options
Comparison Of DIN-Approved Alternatives
Alternatives commonly used in Canada include levofloxacin, ciprofloxacin, amoxicillin/clavulanate, macrolides and doxycycline.
Levofloxacin and ciprofloxacin share fluoroquinolone class risks but differ in spectrum; moxifloxacin has stronger Gram-positive and atypical coverage.
Amoxicillin/clavulanate or doxycycline are often preferred first-line for uncomplicated sinusitis or bronchitis because of lower serious-risk profiles.
Pros And Cons Checklist
Pros for moxifloxacin: once-daily dosing, high oral bioavailability, strong atypical coverage and IV/PO interchangeability.
Cons: class safety warnings (tendons, QT, neuropathy), stewardship restrictions and avoidance in patients under 18.
Clinicians and pharmacists should balance spectrum needs, interaction potential and provincial formulary status when choosing an alternative.
Regulatory Status
Health Canada Approval Process
Avelox is authorized for marketing in Canada by Health Canada and is prescription-only with an assigned DIN.
Approval follows review of quality, safety and efficacy data consistent with dossiers submitted to EMA and FDA.
Health Canada issues safety communications in line with international regulators and updates monographs based on post-market surveillance.
DIN And Bilingual Labelling Rules
Packaging and labelling must meet Canadian bilingual requirements (English/French) and include DINs used for reimbursement and tracking.
Provincial formularies and hospital purchasing agreements determine local access and coverage beyond federal authorization.
Post-market adverse reaction reporting to Health Canada informs ongoing updates to prescribing information and pharmacy counselling points.
Consolidated FAQ
Q: Is Avelox safe for older adults with heart disease?
A: Use cautiously; monitor QT risk, correct electrolytes and review interacting medications with prescriber and pharmacist.
Q: Can I take Avelox with antacids or calcium?
A: Space moxifloxacin from cation-containing products by several hours to avoid reduced absorption and reduced effectiveness.
Q: Why wasn’t Avelox prescribed for my sinus infection?
A: Stewardship guidance discourages routine fluoroquinolone use for uncomplicated sinusitis because of safety concerns and alternative options.
Q: Can I switch from IV Avelox to tablets?
A: Yes—clinical stability allows IV-to-oral switch using the same 400 mg once-daily dosing as per hospital protocols.
Q: Is Avelox covered by provincial drug plans?
A: Coverage varies by province and formulary; check DIN listings with ODB, PharmaCare or RAMQ and consult your pharmacy team.
Visual Guide
Recommended infographic elements for Canadian audiences include a dosage flowchart showing 400 mg once daily for adults and typical durations by indication.
A provincial coverage map should display variability across ODB, PharmaCare and RAMQ with flags for special approvals or restrictions.
Purchase-channel visuals can show hospital IV supply for inpatient care and community pharmacy or licensed online pharmacy options for tablets.
Safety quick-cards should list absolute contraindications, key drug interactions (QT drugs, cations) and immediate counselling points in both languages.
Storage And Transport
Canadian Household Guidelines
Store tablets at controlled room temperature 20–25°C (68–77°F) and protect them from moisture and direct light.
Transport exposure within 15–30°C (59–86°F) is acceptable; avoid storing medications in bathrooms or near sinks.
Keep medication out of reach of children and pets and retain original packaging that shows DIN and bilingual labels for pharmacy follow-up.
Cold-Chain Storage Where Applicable
IV flexibags are managed under hospital protocols and should not be frozen; inspect bags for integrity before administration.
For remote northern deliveries avoid prolonged exposure to extreme temperatures and use expedited shipping if ambient conditions exceed recommended ranges.
No refrigeration is required for the tablets under normal storage recommendations.
Guidelines For Proper Use
Advice From Canadian Pharmacists
Confirm the indication and intended duration before dispensing and screen patients for contraindications such as myasthenia gravis or prior quinolone tendon issues.
Review all medications for QT-prolonging agents and cation supplements and counsel patients to report tendon or neuropathic symptoms immediately.
Reinforce adherence to the full prescribed course and advise ECG or electrolyte checks for elderly or high-risk patients when clinically indicated.
Provincial Health Authority Guidance
Provincial stewardship policies recommend avoiding routine use for uncomplicated sinusitis or bronchitis unless no suitable alternatives exist.
When coverage barriers arise, pharmacists should offer DIN-approved alternatives and help with prior-authorization documentation for provincial formularies.
Provide clear bilingual written counselling and document DIN and lot number at dispensing to support pharmacovigilance.
Consolidated Frequently Asked Questions For Patients
Q: How should I take the 400 mg tablet?
A: Take the tablet whole with a full glass of water, with or without food, and follow the prescribed once-daily schedule.
Q: What should I watch for after starting therapy?
A: Report sudden tendon pain, new numbness or tingling, palpitations or fainting, and severe mood or sleep changes immediately.
Q: Is it safe during pregnancy?
A: Discuss with the prescriber; product monographs and prescriber judgement guide use given safety considerations and available alternatives.
Delivery Across Canada (English)
| City | Region | Delivery Time |
|---|---|---|
| Toronto | Ontario | 5-7 days |
| Montreal | Quebec | 5-7 days |
| Vancouver | British Columbia | 5-7 days |
| Calgary | Alberta | 5-7 days |
| Edmonton | Alberta | 5-7 days |
| Ottawa | Ontario | 5-7 days |
| Winnipeg | Manitoba | 5-7 days |
| Quebec City | Quebec | 5-7 days |
| Halifax | Nova Scotia | 5-7 days |
| Victoria | British Columbia | 5-7 days |
| Hamilton | Ontario | 5-9 days |
| Kitchener | Ontario | 5-9 days |
| London | Ontario | 5-9 days |
| Saskatoon | Saskatchewan | 5-9 days |
| Regina | Saskatchewan | 5-9 days |