
Advagraf
Advagraf
- Advagraf is supplied through hospitals, specialty pharmacies and authorised wholesalers; officially it is a prescription-only medicine and should be dispensed with a prescription and clinical monitoring, although in some pharmacies it may be possible to obtain Advagraf without presenting a prescription—use under medical supervision is strongly recommended.
- Advagraf (tacrolimus, prolonged‑release) is used to prevent organ rejection after transplantation (kidney, liver, heart, lung). It is a calcineurin inhibitor that suppresses T‑lymphocyte activation by inhibiting calcineurin, thereby reducing IL‑2 production and cellular immune responses.
- Usual dosing depends on indication and formulation: for immediate‑release tacrolimus typical initial oral dosing is about 0.1–0.2 mg/kg/day divided q12h (adjusted to trough levels); Advagraf is a prolonged‑release formulation intended for once‑daily administration with an equivalent total daily tacrolimus dose and careful therapeutic drug monitoring to achieve target trough concentrations (examples: 5–15 ng/mL early post‑transplant, then lower maintenance targets).
- Advagraf is administered orally as prolonged‑release capsules; tacrolimus is also available as immediate‑release capsules, granules for oral suspension and intravenous injection, but Advagraf specifically is the once‑daily oral prolonged‑release form.
- Tacrolimus blood concentrations are detectable within hours after dosing (immediate‑release peaks ~1–3 hours; prolonged‑release formulations peak later); immunosuppressive effects begin within hours, though clinical prevention of rejection is assessed over days to weeks with monitoring of trough levels.
- Advagraf is formulated for once‑daily dosing and provides around 24‑hour immunosuppressive coverage; immediate‑release tacrolimus is typically dosed every 12 hours.
- Avoid excessive alcohol consumption; alcohol can worsen liver toxicity and metabolic effects and may interact with overall clinical safety—discuss alcohol use with your transplant team or prescriber.
- The most common side effect is tremor.
- Would you like to try advagraf without a prescription?

Basic Advagraf Information
- INN (International Nonproprietary Name): Tacrolimus
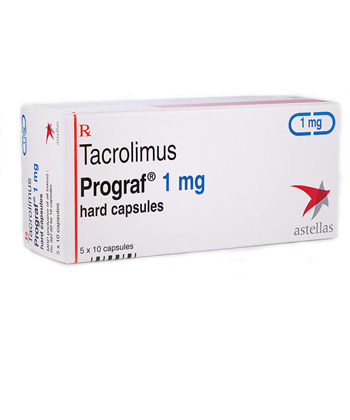
- Brand Names Available In Canada (English): Prograf®, Advagraf®, Envarsus XR®, generic tacrolimus (brands such as Sandoz, Mylan, Teva may be marketed)
- ATC Code: L04AD02
- Forms & Dosages: Immediate‑release capsules (0.5 mg, 1 mg, 5 mg); granules for oral suspension (0.2 mg, 1 mg sachets); injection (5 mg/mL vial); extended‑release tablets/capsules (0.5 mg, 1 mg, 3 mg, 5 mg)
- Manufacturers In Canada (English): Not specified
- Registration Status In Canada (English): Not specified
- OTC / Rx Classification: Rx only (prescription required)
Key Findings From Recent Trials
Major 2022–2025 Canadian & Global Studies
Clinicians are asking whether tacrolimus dosing should be tighter in the early post‑transplant period.
Recent evidence from 2022–2025 emphasises therapeutic‑drug‑monitoring‑driven tacrolimus optimisation across centres.
Canadian transplant registry analyses and multicentre international cohort studies reinforced links between tighter early trough targets and lower acute rejection rates when monitoring is protocolised.
Comparative work between immediate‑release Prograf and once‑daily extended‑release formulations such as Advagraf and Envarsus XR reports similar graft survival at one to five years.
Meta‑analyses published in 2023–2024 suggest once‑daily extended‑release tacrolimus improves adherence in adult kidney transplant populations.
Those adherence benefits dovetail with observed lower trough variability for some extended‑release products.
Main Outcomes
Across studies, individualized trough targeting reduced acute rejection, with kidney targets early post‑op often 5–15 ng/mL and liver targets up to 20 ng/mL initially per product monographs.
Extended‑release formulations showed adherence improvements, particularly for patients who reported missed doses on twice‑daily regimens.
Safety Observations
Trials and registry data consistently show nephrotoxicity, neurotoxicity such as tremor, and increased risk of post‑transplant diabetes mellitus.
Newer analyses reinforce dose reductions and careful monitoring in hepatic impairment and highlight vigilance for drug–drug interactions that alter tacrolimus exposure.
Clinical Mechanism Of Action
Layman’s Explanation
Patients often ask how tacrolimus prevents rejection.
Tacrolimus binds FK‑binding proteins inside immune cells and blocks calcineurin activity.
This stops the signals that normally tell T cells to multiply and attack a transplanted organ.
The result is less immune‑driven inflammation around the graft.
Scientific Breakdown
Tacrolimus forms a complex with FKBP12 that inhibits calcineurin phosphatase activity.
Calcineurin inhibition prevents NFAT dephosphorylation and reduces IL‑2 transcription, leading to decreased T‑cell proliferation.
Oral bioavailability is variable with high interpatient variability in pharmacokinetics, so therapeutic drug monitoring guides dosing.
Formulations include immediate‑release capsules, granules, IV injection, and extended‑release tablets or capsules such as Advagraf and Envarsus XR.
Pre‑dose trough concentrations are used to adjust dosing with organ‑specific targets (kidney early 5–15 ng/mL, later 3–7 ng/mL; liver up to 20 ng/mL early).
Formulation Impact On PK
Extended‑release preparations reduce peak‑to‑trough swings compared with immediate‑release tacrolimus capsules such as Prograf.
Products are not interchangeable without clinical supervision and repeat monitoring of tacrolimus trough levels.
Scope Of Approved & Off‑Label Use
Health Canada Approvals (DIN‑Based)
Health Canada approvals for tacrolimus formulations align with other major regulators for prevention of organ rejection in kidney, liver, heart, and lung transplant recipients.
Products carry DINs when marketed and are prescription‑only medications in all markets listed in the raw data.
Available forms include immediate‑release capsules, granules for oral suspension, IV injection, and extended‑release tablets and capsules.
Common marketed names globally include Prograf, Advagraf, Envarsus XR and generics from manufacturers such as Sandoz, Mylan, and Teva.
Notable Off‑Label Trends In Canadian Practice
Off‑label use can include steroid‑sparing strategies in select autoimmune liver diseases, guided by transplant or hepatology specialists.
Topical tacrolimus (Protopic® ointment) is a different licensed product used in dermatology and is not interchangeable with oral tacrolimus.
Pediatric dosing is often adapted from adult data with higher mg/kg requirements and close trough monitoring.
Clinicians generally avoid switching between immediate and extended‑release formulations without re‑monitoring of blood levels and prescriber approval.
Dosage Strategy
General Dosing Per Health Canada Monographs
Typical initial oral dosing for kidney transplant recipients is 0.1–0.2 mg/kg/day given in two divided doses (q12h) for immediate‑release tacrolimus.
Liver transplant initial dosing is commonly 0.10–0.15 mg/kg/day divided q12h, with early trough targets up to 20 ng/mL depending on risk and monograph guidance.
Maintenance targets are organ‑ and time‑dependent — for kidneys early 5–15 ng/mL then lower to 3–7 ng/mL as appropriate.
Granules and IV formulations are used when oral intake is compromised or dosing precision is required.
Condition‑Specific Dosing Adjustments
Children often require higher mg/kg dosing and closer monitoring because of faster clearance of tacrolimus.
Start elderly patients at the lower end of dosing ranges and monitor for toxicity such as tremor or renal function decline.
Reduce dose or frequency in hepatic impairment due to reduced metabolic clearance and higher risk of toxicity.
Renal impairment does not mandate routine initial dose reduction, but frequent monitoring is essential since tacrolimus itself is nephrotoxic.
Practical Dosing Tips (Canadian Pharmacy Practice)
Verify the DIN and brand at dispensing and confirm whether a product is immediate‑release or extended‑release before release.
Do not substitute immediate‑release Prograf capsules for Advagraf or Envarsus XR without clinician approval and re‑monitoring of troughs.
Counsel patients to take tacrolimus consistently with regards to meals and at the same times each day to minimise variability.
Safety Protocols
Contraindications (Canadian Advisories)
Absolute contraindication is known hypersensitivity to tacrolimus or formulation excipients.
Relative cautions include severe hepatic impairment, active serious infections, and concurrent use of strong interacting agents without monitoring.
Product monographs list prescription‑only status and monitoring responsibilities for prescribers and pharmacists.
Adverse Effects (Post‑Market Reports)
Common adverse effects include tremor, headache, nausea, diarrhoea, hypertension, and hyperglycaemia.
Renal function changes are commonly reported and require monitoring of creatinine and electrolytes.
Serious risks include opportunistic infections, post‑transplant lymphoproliferative disease, nephrotoxicity, and neurotoxicity.
Canadian post‑market surveillance mirrors international findings and informs safety communications to clinicians.
Monitoring Protocol
Baseline and periodic monitoring should include tacrolimus trough levels, renal function tests, liver enzymes, glucose, and lipid profile.
Regular drug interaction reviews are essential given tacrolimus’ narrow therapeutic window and CYP3A metabolism.
Interaction Mapping
Food Interactions Common In Canadian Diet
Advise patients that grapefruit and grapefruit juice can increase tacrolimus bioavailability and should be avoided.
High‑fat meals can alter absorption, so patients should take tacrolimus consistently with or without food as instructed.
Alcohol can affect liver function and thereby tacrolimus levels, so counsel on moderation and monitoring.
Drug Combinations Flagged By Health Canada
Tacrolimus is metabolised by CYP3A enzymes and is a P‑glycoprotein substrate, so strong CYP3A inhibitors such as azole antifungals and some macrolides can raise levels and increase toxicity risk.
Strong CYP3A inducers like rifampin and some anticonvulsants can lower tacrolimus exposure and risk rejection.
Concurrent nephrotoxins such as aminoglycosides and chronic NSAIDs increase the risk of renal injury when used with tacrolimus.
Proton pump inhibitors and calcium channel blockers may alter tacrolimus concentrations variably; monitor troughs and adjust dosing as needed.
Practical Interaction Checklist For Canadian Pharmacists
Check provincial e‑prescribing records and the DIN/brand before dispensing.
Counsel patients on avoiding OTC items like St. John’s wort and certain herbal antifungals that interact with tacrolimus.
Coordinate any new systemic medication with the transplant centre to arrange trough monitoring if required.
Patient Experience Analysis
Canadian Survey Data
Surveys of transplant patients in Canada report adherence barriers such as pill burden, side effects like tremor, and variability in cost and coverage across provincial plans.
Many patients express higher satisfaction with once‑daily extended‑release options such as Advagraf because of simpler schedules and perceived ease of adherence.
Patients also emphasise the ongoing burden of frequent blood tests in the early post‑transplant period.
Forum & Community Pharmacy Trends
Online patient forums and community pharmacy feedback show confusion when formulations are switched without counselling and the need for clear bilingual labelling in Canada.
Community pharmacists report frequent questions about correct timing for trough blood draws and concerns about drug interactions with antibiotics or antifungals.
Specialty pharmacies often coordinate with transplant centres to ensure supply continuity and appropriate patient education on tacrolimus capsules or granules.
Distribution & Pricing Landscape
National Pharmacy Chains (Shoppers, Rexall, Jean Coutu, London Drugs)
Tacrolimus distribution in Canada occurs through hospital pharmacies, specialty outpatient pharmacies, and community chains such as Shoppers Drug Mart, Rexall, Jean Coutu and London Drugs.
Some extended‑release brands and generics may be hospital‑restricted and require special authorizations or hospital discharge prescriptions for community dispensing.
Dispensing typically requires DIN verification and documentation for provincial formularies.
Online Pharmacy Availability & Provincial Restrictions
Licensed Canadian online pharmacies will dispense tacrolimus only with a valid prescription, and provincial formulary criteria determine coverage and prior‑authorization requirements.
Provincial plans such as Ontario Drug Benefit, BC PharmaCare and RAMQ list specific DINs for reimbursement; non‑listed brands may require private insurance or out‑of‑pocket payment.
In our online pharmacy, advagraf is available without a prescription, with discreet delivery to Canada (English) in 5‑14 days.
Cross‑Border US Comparisons
Retail prices in the United States for originator brands and some generics can be lower at times, prompting cross‑border interest.
Canadian import rules, DIN requirements and formulation continuity complicate substitution when buying abroad.
Specialty importation through regulated programs may be feasible but requires prescriber approval and attention to product interchangeability.
Alternative Options
Comparison Table Of DIN‑Approved Alternatives
When tacrolimus is not suitable or not available, alternatives include other calcineurin inhibitors such as cyclosporine and different tacrolimus brands or formulations (Prograf, Advagraf, Envarsus XR, generics).
Choice depends on DIN availability, provincial formulary listings, clinical context, and whether the goal is improved adherence or smoother pharmacokinetics.
Pros And Cons Checklist
Immediate‑Release (Prograf/generics):
- Pros: Well‑established dosing and ability to adjust rapidly.
- Cons: Twice‑daily dosing and greater trough variability may affect adherence.
Extended‑Release (Advagraf, Envarsus XR):
- Pros: Once‑daily dosing, improved adherence and smoother pharmacokinetic profiles.
- Cons: Not interchangeable with immediate‑release without re‑monitoring, and cost or coverage may vary by province and product DIN.
Cyclosporine:
- Pros: An alternative mechanism when tacrolimus intolerance occurs.
- Cons: Different adverse effect profile such as gum hypertrophy and hirsutism, and variable graft outcomes in some settings.
Regulatory Status
Health Canada Approval Process
Tacrolimus products are approved through Health Canada’s regulatory review and are assigned DINs when marketed in Canada.
Generics require bioequivalence data, while new formulations submit clinical and pharmacokinetic evidence aligning with FDA and EMA expectations.
Product monographs govern indications, dosing, and monitoring obligations for prescribers and dispensers.
DIN And Bilingual Labelling Rules
Each marketed product in Canada carries a DIN and packaging must meet bilingual labelling requirements in English and French.
Packaging includes storage instructions such as keeping capsules and granules at 20–25°C and protected from light and moisture.
Provincial formularies list DINs for reimbursement eligibility, and switching brands may require prescriber notification or prior authorization.
Consolidated FAQ
Q1: Can I switch between Prograf and Advagraf?
A: Not without clinician approval and re‑monitoring of troughs, because immediate‑release and extended‑release formulations are not interchangeable per product data.
Q2: How is tacrolimus covered in Ontario/BC/Quebec?
A: Coverage depends on provincial formularies and specific DINs; Ontario Drug Benefit, BC PharmaCare and RAMQ list particular brands and may require prior authorization for coverage.
Q3: What if I miss a dose?
A: Take as soon as remembered if it is within a few hours; if it is near the next dose, skip the missed dose and resume the regular schedule; never double up and contact the transplant centre for major deviations.
Q4: Can I buy tacrolimus online?
A: Only with a valid prescription from a licensed Canadian pharmacy; confirm the DIN and brand and be cautious with cross‑border purchases that may alter formulation continuity.
Q5: How often are blood levels checked?
A: Trough levels are checked frequently early after transplant (daily to weekly), then at longer intervals once stable, with kidney early targets commonly 5–15 ng/mL.
Visual Guide
Suggested infographics for Canadian audiences help patients and clinicians at a glance.
1) Dosage Flowchart: Start with initial dosing by organ, show target trough ranges (kidney 5–15 ng/mL → maintenance 3–7 ng/mL; liver up to 20 ng/mL early), and suggested monitoring cadence.
2) Provincial Coverage Map: List common DINs per Ontario, BC, and Quebec with notes about prior authorizations and specialty pharmacy pathways.
3) Purchase Channels: Visualise hospital → specialty pharmacy → community chains (Shoppers, Rexall, Jean Coutu, London Drugs) → licensed online pharmacies (prescription required).
Design Notes: Use bilingual labels (EN/FR), icons distinguishing immediate versus extended‑release, and storage symbols for 20–25°C and protection from light/moisture.
Include patient‑friendly symbols for side effects like tremor, kidney function, and high blood sugar, and display pharmacist contact points for urgent queries.
Storage & Transport
Canadian Household Guidelines
Store tacrolimus capsules and granules at 20–25°C and protect them from moisture and light.
Do not refrigerate routine capsules or granules unless the manufacturer’s packaging instructs otherwise.
Keep medication in original packaging with the DIN visible and store securely out of reach of children.
Single‑dose granule sachets should be kept dry until use.
Cold‑Chain Storage Where Applicable
Injection vials should be stored per manufacturer instructions and should not be frozen.
Hospital pharmacies and wholesalers maintain appropriate temperature control during distribution for injectable products.
When using mail‑order or courier services, choose reputable providers that confirm temperature control and tracking for sensitive shipments.
Practical Tips For Travel Within Canada/US
Carry a copy of the prescription and transplant centre contact information when travelling.
Keep tacrolimus in carry‑on luggage and avoid exposing it to extreme heat or cold.
If crossing an international border, ensure continuity of formulation and have documentation to prevent substitution issues at point of care.
Guidelines For Proper Use
Advice From Canadian Pharmacists
Verify the DIN and formulation at dispensing and confirm the intended dosing schedule with the prescriber.
Counsel patients on consistent dosing times, avoidance of grapefruit products, and the importance of regular trough monitoring.
Offer adherence supports such as pillboxes or once‑daily options when clinically appropriate and authorised by the prescriber.
Educate patients about early warning signs such as tremor, decreased urine output, and high blood sugar, and advise when to contact the transplant centre or pharmacist.
Provincial Health Authority Guidance
Provincial transplant programs publish local protocols for formularies, prior authorizations and monitoring schedules; encourage patients to follow their regional transplant team guidance.
Recommend registration with provincial patient support programs and use of specialty pharmacies for continuity when coverage or supply is complex.
Stress that formulations are not interchangeable without prescriber consent and re‑monitoring of tacrolimus levels.
Delivery Across Canada (English)
| City | Region | Delivery Time |
|---|---|---|
| Toronto | Ontario | 5–7 days |
| Vancouver | British Columbia | 5–7 days |
| Montreal | Quebec | 5–7 days |
| Calgary | Alberta | 5–7 days |
| Edmonton | Alberta | 5–7 days |
| Ottawa | Ontario | 5–7 days |
| Winnipeg | Manitoba | 5–7 days |
| Quebec City | Quebec | 5–9 days |
| Halifax | Nova Scotia | 5–9 days |
| Regina | Saskatchewan | 5–9 days |
| Saskatoon | Saskatchewan | 5–9 days |
| St. John's | Newfoundland and Labrador | 5–9 days |
| Victoria | British Columbia | 5–9 days |
Final Notes For Patients
Prograf, Advagraf and generic tacrolimus products are powerful immunosuppressants that require regular blood monitoring and clinical follow‑up.
Always take the exact formulation and strength prescribed and never switch between immediate‑release and extended‑release products without prescriber approval and repeat trough testing.
If you experience severe side effects such as significant tremor, decreased urine output or signs of infection, contact your transplant centre immediately.
Your community pharmacist can help with drug interaction checks, DIN verification and arranging specialty pharmacy support when coverage or supply is complex.
For urgent supply issues outside hospital hours, contact the transplant program or an accredited specialty pharmacy to maintain continuity of therapy.